Magnesium Benefits: It Lowers Blood Pressure. It Won’t Fix Night Leg Cramps.

Magnesium is one of the few supplements where something real survives the trials. It is also one where the two things it is most often bought for — sleep and leg cramps — are the weakest claims on the shelf.
| Claim | Evidence | Result |
| Blood pressure | 34 double-blind trials, 2,028 people | −2.0 / −1.8 mmHg |
| Blood pressure, if already normal | 8 trials, 2025 analysis | not significant |
| Fasting glucose, in type 2 diabetes | 9 double-blind trials, 370 people | lower |
| Falling asleep faster | 2 trials, 55 people, both magnesium oxide, low certainty | 17 min |
| Sleeping longer | same 2 trials | not significant |
| Night leg cramps, older adults | Cochrane, 5 trials, 271 people | no effect |
| Leg cramps in pregnancy | Cochrane, 5 trials, 408 women | conflicting |
| Cramps from exercise | no randomised trial found: Cochrane to 2019, our search to September 2026 | no trial found |
What it actually does: blood pressure
This is the finding that holds up when the trials are pooled, though the trials’ results are spread more widely than chance alone would produce.
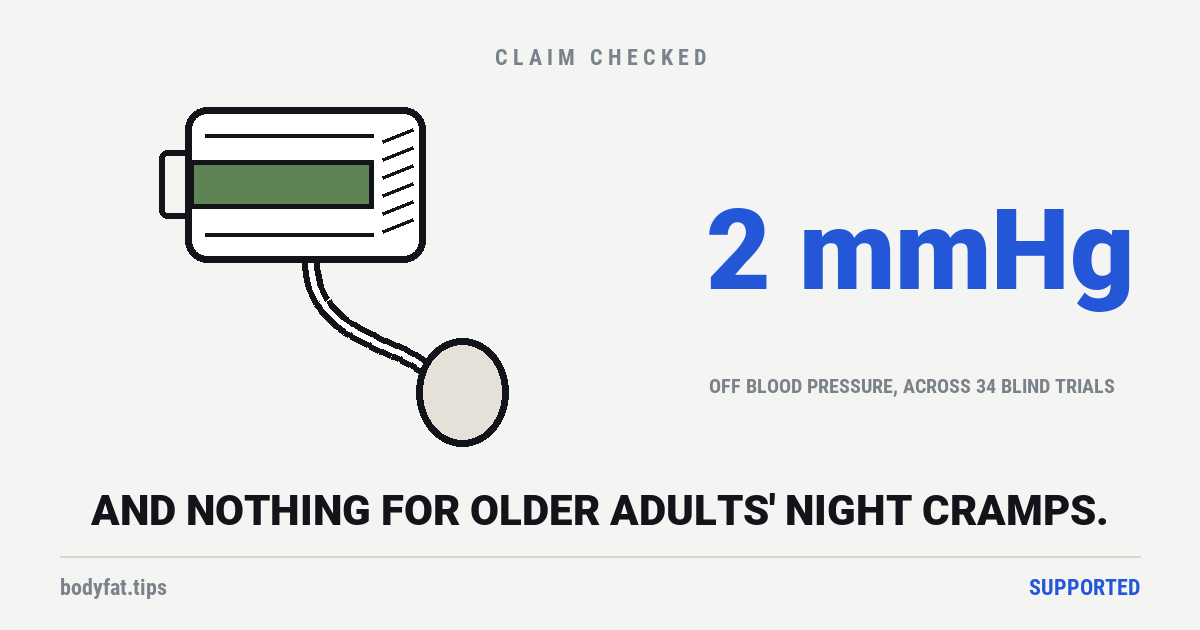
A 2016 meta-analysis pooled 34 randomised, double-blind, placebo-controlled trials in 2,028 adults — both people with high blood pressure and people without. At a median dose of 368 mg a day for a median of three months, magnesium lowered systolic blood pressure by 2.00 mmHg and diastolic by 1.78 mmHg. [1]
Two things make that more convincing than a typical supplement result. The blood-pressure drop was accompanied by an actual rise in blood magnesium — so the thing you swallowed demonstrably got in, and diastolic pressure, the lower number, fell further where blood magnesium rose more; systolic, the top number, did not track it. And the authors were willing to write the sentence most meta-analyses avoid: “Our findings indicate a causal effect of Mg supplementation on lowering BPs in adults.” [1]
They also found that around 300 mg a day, or a single month of taking it, was enough to shift both serum magnesium and blood pressure.
A larger meta-analysis in the same journal in 2025, 38 trials and 2,709 people, found a similar average: systolic down 2.81 mmHg, diastolic down 2.05 [6]. It did not find the rest. There was “no dose-response relationship” — more magnesium did not mean a bigger drop — and in people whose blood pressure was already normal the fall was not statistically significant, meaning it could not be told apart from chance. The benefit sat with people who had high blood pressure, most clearly those already on blood-pressure medication (systolic down 7.68 mmHg), and with people low in magnesium (down 5.97). In high blood pressure that was not being treated, only the diastolic number moved significantly [6].
If you do try it, one number above needs a warning label. The median dose in those 2016 trials, 368 mg a day, is over the US upper limit for magnesium from supplements, which the National Academies set in 1997 at 350 mg a day for adults, just under the 360 mg at which diarrhoea starts to show up; magnesium in food does not count toward it [7]. The risk of magnesium building up to toxic levels rises with kidney disease, and magnesium can cut the absorption of some antibiotics and osteoporosis drugs taken close to it, so anyone with kidney problems or on those drugs should ask a doctor first [8].
Is two points worth anything?
It sounds like nothing. It is small, and it is not nothing.
Two millimetres of mercury will not move you out of a diagnosis or replace a medication. What a couple of points does do is matter at the scale of a population — blood pressure risk is continuous, so shifting a whole distribution down slightly prevents more events than the size of the shift suggests it should.
For one person deciding whether to buy a bottle: if your blood pressure is normal, the 2025 analysis found no significant effect [6]. If it is high, expect a couple of points on average, more if you already take blood-pressure medication, so tell whoever prescribes it. Either way it is not a treatment; for scale against salt, exercise and diet, see how to lower blood pressure naturally. The trials’ results differ from one another by more than chance alone would produce. By the statistic researchers call heterogeneity, or I-squared, about 62% of the spread between the systolic results of the 34 trials in the 2016 analysis was more than chance would produce (zero would mean the trials differed no more than luck allows), and in the 2025 analysis the figure was 78% [1] [6]. The 2016 authors tested fifteen possible reasons, from dose to who was enrolled, and wrote that “residual heterogeneity may still exist” after all of them: some of that extra spread is unexplained. The US Food and Drug Administration, ruling on a label claim in January 2022, went further: foods and supplements may say adequate magnesium “may reduce the risk of high blood pressure” only in wordings that call the evidence inconsistent, such as “the FDA has concluded that the evidence is inconsistent and inconclusive” [9]. That ruling weighed the trials one by one rather than pooled, and it governs what a label may say, but together with that unexplained spread between trials it is why we rate this Supported rather than Established.
Night cramps in older adults: still no, after two more trials
Magnesium has been sold for cramp for decades. Cochrane went and looked, across 11 trials and 735 people [2]. But those were three different groups — older adults with night cramps, pregnant women, and 29 people with liver cirrhosis — and the answer depends on which group you are in.
For idiopathic cramps — the ordinary night-time kind with no obvious cause, in five trials of 271 adults averaging around 62 to 69 years old — nothing moved. Cramps per week differed by 0.18, with a confidence interval running from −0.84 to +0.49. Cramp intensity: no difference. Cramp duration: no difference. The review’s own words for this group: “It is unlikely that magnesium supplementation provides clinically meaningful cramp prophylaxis to older adults experiencing skeletal muscle cramps” — prophylaxis meaning prevention [2].
And one endpoint deserves singling out. The proportion of people who got a 25% or better reduction in their cramp rate came out at a risk ratio of 1.04, confidence interval 0.84 to 1.29 — and Cochrane graded that high-certainty evidence. [2]
High certainty is the strongest grade they issue. It does not mean nobody should ever look again. It means that further trials of this kind are unlikely to change the answer, and the answer is no.
The trials’ results also differed from one another by little more than chance alone would produce. On the measures of how often people cramped, between 0% and 12% of the spread between trials was more than luck would give; that share is the statistic called heterogeneity, and the review calls it minimal here [2]. With three to five trials in each comparison it is an imprecise measure, but on it the null is not an average of trials that differed by more than chance.
Two trials have looked again since. The first ran in Ukraine in 2018 and was published in 2021: 184 adults aged 45 or over took magnesium oxide or a placebo for 60 days. By its summary, cramps fell by 3.4 a week on magnesium and by 2.6 on placebo, a gap the authors call significant [18]. The capsules’ maker paid for it, it was registered only after it had run, and the authors report that one of its seven sites went the other way. The same maker paid for one of the earlier trials that found nothing [2]. The second, from Finland in 2026, put magnesium, a placebo and knee-high compression stockings side by side in 121 people aged 50 to 85. Magnesium did no better than the placebo; the stockings, which could not be disguised as anything else, cut cramps by about one and a half a week [19]. And pooled with three of the adult trials before it, the Ukrainian result still leaves no clear effect: 0.42 fewer cramps a week, in a range running from 1.15 fewer to 0.31 more [12].
Two genuine gaps. First, the five trials in pregnancy-related leg cramps, 408 women, could not be pooled, and all five were judged at high risk of bias; in the review’s words, “the literature is conflicting and further research in this population is needed”. So the pregnancy question is unanswered rather than answered negatively.
What has come since has not settled it. A 2020 trial in Brazil gave 132 women in early pregnancy magnesium citrate or an identical placebo for four weeks and found no difference [21]. A 2021 pooling of four trials, 332 women, found cramps came no less often on magnesium [20]. The 2026 review pooled four trials, about 364 women, and found the opposite: women on magnesium were about a third more likely to halve their cramps, a risk ratio of 1.35 in a range running from 1.05 to 1.74 [12]. It rated most of those trials at low risk of bias, where Cochrane had rated every pregnancy trial it included at high risk. Two poolings, five years apart, two answers.
Second, the cramps a gym-goer means. Cochrane found “no RCTs evaluating magnesium for exercise-associated muscle cramps” when it searched in September 2019 [2]. We found none published or registered since (PubMed, Europe PMC, OpenAlex and two trial registries, searched 30 September 2026), and a 2026 review of 13 trials of electrolytes for cramps, which searched to August 2025, has none either. Its two trials in exercise tested mixed drinks carrying a trace of magnesium, and it puts their effect down to sodium and chloride [12]. The nearest randomised trial gave 20 athletes with low-normal blood magnesium either magnesium oxide or a placebo for three weeks. It saw no change in performance or in muscle symptoms, and Cochrane, which read it in full, left it out because it did not measure cramping [2] [13].
The paper a seller can point to is a 2022 survey. At two half-marathons, runners who chose a magnesium sports drink reported cramps less often than runners who chose water, 21% against 46% [14]. The runners picked their own drink, the drink also carried sodium and potassium, only about half of the runners answered, and the paper says of itself that it was a survey and not a randomised trial. Its one author gives the company behind the drink as their affiliation, that company sponsored both races, and the paper prints no funding or conflict statement. So, as far as we can find, magnesium for exercise cramps has not been put to a randomised trial, which is not the same as tested and failed. Whether those cramps come from lost electrolytes at all is a separate question, and we checked that one too.
Sleep: 17 minutes, from two small trials
Does magnesium help you sleep? Here is the entire evidence base for older adults with insomnia, as a 2021 systematic review counted it: three randomised trials, 151 participants, three countries. [3]
Pooled, people fell asleep 17.4 minutes faster than on placebo, which is a real difference if you are lying there. But that figure comes from only two of the three trials, 55 people in all, and both gave magnesium oxide, the cheap form the common advice says to avoid; one of the two enrolled 12 healthy volunteers rather than people with insomnia [3]. In the same two trials, total sleep time improved by 16 minutes — and that one was not statistically significant.
The reviewers were blunt about what they were working with. Every trial was at moderate-to-high risk of bias, the outcomes were supported by “low to very low quality of evidence”, and their own summary is that “the quality of literature is substandard for physicians to make well-informed recommendations.” [3]
They still ended up mildly in favour, and their reason is worth repeating because it is honest rather than scientific: magnesium is very cheap and widely available, so the evidence “may support” trying it. [3] That is a cost-benefit argument, not a demonstration that it works.
A 2026 review, published after this page first went up, widened the lens to 12 trials in adults of any age. On insomnia severity and overall sleep quality, results “ranged from small benefits to no magnesium-specific effect”, the certainty was low or very low for every sleep outcome, and the conclusion is plain: “Current evidence does not support oral magnesium as a routine treatment for insomnia” [10].
If you are taking magnesium for sleep and it seems to help, nothing here says stop. What it says is that you are ahead of the evidence rather than behind it.
Which form? Less settled than the marketing suggests
Which magnesium should you buy? The honest answer is that the comparison people want has not been done well.
A widely cited 2001 study measured four commercial preparations by how much extra magnesium turned up in urine. Magnesium oxide came out at 4% fractional absorption. Magnesium chloride, lactate and aspartate were all significantly higher, and equivalent to each other. [4]
So the common advice to avoid oxide has something behind it. But notice what that study did not test: glycinate and citrate — the two forms most people are actually choosing between. It cannot rank them, and neither can we. Other studies have tested each of them against oxide, and our magnesium glycinate verdict goes through them: citrate came out ahead of oxide, and the one randomised trial built to set glycinate against oxide, in 12 people missing part of the bowel, found no difference in the amount absorbed, though the labelled magnesium in the blood peaked sooner, and added up to more over the following hours, after glycinate [15]. Two later studies gave healthy adults a single dose of each form while testing a third product, and each came from that product’s maker. In one, of 10 people, glycinate’s figures a day later were ahead of oxide’s in blood and urine, by margins the paper tested and did not mark as significant, and behind in red blood cells, the one gap between the two that it marks as significant [16]. In the other, of 40 people, blood magnesium rose an hour after oxide and did not rise significantly at any of the three points measured over the six hours after glycinate [17]. One dose, a day or less, run by the maker of a rival product: neither study settles it.
The paper’s own conclusion cuts against the usual framing too: “Inorganic magnesium salts, depending on the preparation, may have bioavailability equivalent to organic magnesium salts.” [4] That is the exception rather than the rule: a 2021 review of 14 absorption studies concluded that “inorganic formulations appear to be less bioavailable than organic ones”, meaning less of them gets absorbed [11]. In this study chloride was the inorganic salt that kept up; oxide was not.
On timing — another popular query — the trials on this page did not test it. Anyone telling you there is a correct hour is going beyond the evidence.
One more, briefly
In people with type 2 diabetes, nine double-blind trials covering 370 patients found fasting glucose lower on magnesium and HDL cholesterol slightly higher — but HbA1c, the three-month average of blood sugar, did not significantly change. [5] Blood pressure, a secondary outcome there, did not significantly change either, but that is one 2006 analysis of nine small trials, which is thin ground for any conclusion about blood pressure in diabetes.
The verdict
Magnesium lowers blood pressure. That is Supported — two meta-analyses, of 34 double-blind trials in 2016 and 38 trials in 2025, found a similar small fall of about two to three points, and the first found a matching rise in blood magnesium [1] [6]. It is not for everyone: the 2025 analysis found the benefit in people with high blood pressure or low magnesium, no significant effect in people whose blood pressure was normal, and no sign that more magnesium does more [6]. The effect is small and real.
For the night-time leg cramps of later life it does not work: the two trials since the big review went one each way, and pooled with the rest the answer is still no. In pregnancy the reviews disagree, and for cramps during or after exercise neither Cochrane’s search in 2019 nor ours in September 2026 found a randomised trial. The sleep evidence is thin: the 17-minute result comes from two small trials and 55 people, and a 2026 review of 12 trials rated every sleep outcome low or very low certainty. The forms question has a partial answer: oxide tends to absorb worst, but we cannot rank glycinate against citrate, the two forms you are probably choosing between.
Which makes magnesium an unusual entry in this corpus: a supplement that does something measurable, sold mostly for two things it has not been shown to do.
Related: creatine benefits · fish oil benefits · does lack of sleep cause weight gain · best supplements for muscle growth · do testosterone boosters work
This page was corrected on 18 September 2026 after an independent editorial review. The evidence panel said our sources stated no industry funding; the Cochrane cramp review itself reports that a manufacturer of magnesium tablets funded two of its 11 trials, and the panel now says so and lists who paid for every other source. The sleep result was credited to three trials and 151 people; the 17-minute figure comes from two of those trials, 55 people, both taking magnesium oxide. And the cramp verdict was written for everyone. Cochrane’s finding of no benefit is for the night-time cramps of older adults; its pregnancy trials conflict, and it found no trial at all of cramps from exercise. The title, summary table and verdict now say that.
Also added: a larger 2025 blood-pressure meta-analysis, which confirmed the average fall but found no dose-response and no significant effect in people whose blood pressure was normal; the FDA’s 2022 ruling that the evidence is “inconsistent and inconclusive”; the US upper limit of 350 mg a day for magnesium from supplements, which the trials’ median dose exceeds; and a 2026 review of 12 sleep trials. The forms section no longer says the popular forms were never compared with oxide, and now reports that organic forms generally absorb better; a line suggesting blood pressure does not move in type 2 diabetes is now limited to the 2006 analysis it came from. We have also removed two monthly search figures we could not trace to a saved source. The rating is unchanged.
One count on this page was wrong and one gap was stated more firmly than we had checked; both were found on 30 September 2026, when we audited our own “nobody has tested it” sentences. The page spoke of “the one trial of glycinate against oxide”. It is the one trial built to compare the two. Two later studies, each from the maker of a third product, also gave people both forms, and the page now reports them: mixed in one, against glycinate in the other, both a single dose followed for a day or less. And the page called magnesium for exercise cramps “untested” on the strength of a Cochrane search that ended in September 2019. We have now searched past that date and found no randomised trial. The page gives the date of our search, describes the one trial in athletes that came near, and names the survey a seller could cite, which comes from the company behind a magnesium sports drink.
Two sections were older than they looked. The page called night cramps in older adults “finished” on the strength of a search that ended in 2019. Two trials have reported since: one, paid for by a capsule maker, found fewer cramps on magnesium; the other, from Finland, found magnesium no better than a placebo, and a 2026 pooling that includes the first still finds no clear effect. The heading and the verdict now say so. The section on pregnancy now reports a 2020 trial and two later poolings, which reached opposite answers.
Also changed: four sentences described the spread between trials’ results as the trials agreeing or disagreeing with each other. The statistic behind those sentences, heterogeneity, is the share of the spread between trials’ results that is more than chance would produce, and the page now says that and gives the figures: 0% to 12% for the night-cramp trials, 62% and 78% for the two blood-pressure analyses. The evidence panel carries the same changes, says who paid for the studies added today, and gives the Cochrane review’s own funding statement, which it had said could not be reached. The rating is unchanged.
Corrected again on 7 October 2026, after our magnesium glycinate verdict was corrected the same day. We wrote that the 1994 trial built to set glycinate against oxide found no difference overall. It found no difference in the amount absorbed, but across all twelve patients blood levels of the labelled magnesium peaked about three hours sooner after glycinate, and their total over the hours that followed was larger. We had read that trial only as its abstract; we have now read it in full, and the evidence panel says what it shows about its funding: public grants, and a chelate made by the company that sells it. We also wrote that a 2018 study did not test the gaps between glycinate and oxide in blood and urine; it tested them and did not mark them significant. And we wrote that blood magnesium did not rise measurably after glycinate in a 2024 study; the rise its authors report was not significant at any of the three points measured, which is a different thing. Nothing here changes this page’s rating or its findings on blood pressure, cramps or sleep.