Do You Need Electrolytes? Nine Studies, and Still No Clear Cramp Link.

One reason you have been told to drink electrolytes is cramp. Sweat out your salts, the story goes, and the muscle seizes.
When a 2009 review graded the evidence for that, it found mainly anecdotes, eighteen cases and one study of ten people. [1]
Four prospective studies — the kind that follow athletes forward and see who actually cramps — did not support it. [1]
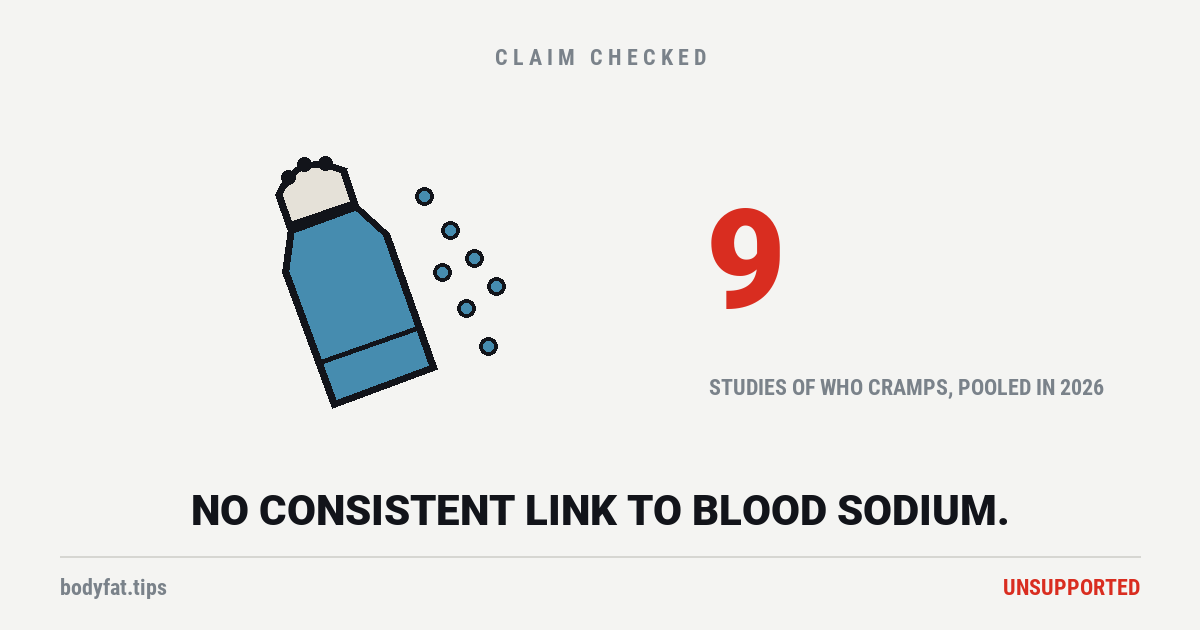
That was 2009. In September 2026 a meta-analysis, a study that pools other studies, put nine together, comparing athletes who cramped with athletes who did not. It found no consistent link between cramp and either fluid lost or sodium in the blood. [4] More on that below, including where most of its athletes came from and how cautiously its own authors rate it.
| Supporting it | Against it |
| Anecdotal observations | 4 prospective cohort studies |
| Case series totalling 18 cases | |
| 1 study of 10 people |
A review that graded its own sources, on purpose
The 2009 review this comes from says openly why it applied evidence-based medicine criteria: because “the quality of experimental methodology varies considerably among studies that are commonly cited”. [1] Somebody had noticed that the citations were being counted rather than read.
What survived the grading, in the author’s words, was “anecdotal clinical observations, case series totalling 18 cases, and one small (n = 10) case-control study”. [1]
A case series is a handful of patients written up after the fact, with nobody to compare them to. Eighteen cases collected that way are not eighteen times the evidence. They are eighteen stories.
What has been published since 2009
That tally is seventeen years old, and this page first presented it as the whole of the evidence. It is not. Here is what has come since, in both directions, with who paid.
A 2019 review quoted the tally and answered it: “There may however be more evidence than these authors admit.” [5] Its case is old and large: studies of miners, ship’s stokers and steelworkers from the 1920s and 1930s. In one, reported in 1936, salt was added to the drinking water of 12,000 men at an Ohio steel mill and cramp cases almost stopped. [5] Those were men doing hard physical work in extreme heat, day after day. We have read the review’s account of those studies and not the studies themselves. The review ran in a journal supplement supported by the Gatorade Sports Science Institute, a division of PepsiCo, and says so. [5]
Then there are the trials that put a drink up against cramp directly. We found five, of nine to twenty people each, and there may be more. Three set the cramp off with electrical pulses and measured how fast the pulses had to come: faster after an electrolyte drink than after water or a placebo, meaning the muscle was a little harder to cramp. [7][8][9] In one of those the drink did not prevent cramping in a single participant. [7] A fourth had thirteen cramp-prone men do a calf-tiring drill in 99°F heat (37°C): nine cramped with a salted sports drink and seven with no fluid at all, though in the seven who cramped both times the drink more than doubled the time before it arrived. [6] The fifth had twenty adults rate their own cramp after a 3.1-mile treadmill run (5 km): fewer reported it after the sponsoring company’s drink than after a standard sports drink, and the gap against plain water was small enough to be chance. [10] Small studies, mostly of cramp made in a lab, showing drinks nudging a threshold rather than abolishing cramp. Four of the five were paid for by a company that sells drinks, and in three of those it made the drink being tested. [7][8][9][10]
A 2026 systematic review went looking for randomised trials of electrolytes against cramp and muscle pain of every kind. It was written with jaw-muscle pain in mind, which is why it appeared in a dental journal. Outside liver disease it found two trials of sodium drinks, both described above, nineteen people between them, and summed them up as reducing “cramp susceptibility”. [20] That is the electrical threshold again, not fewer cramps. The review rates both trials as raising some concerns about bias, and reports no funding. [20]
The biggest piece is the newest. A meta-analysis first published on 3 September 2026 pooled nine studies of triathletes, distance runners and rugby players, mostly men aged 18 to 45: 3,085 who cramped and 8,189 who did not. [4] The two groups did not differ in how much body weight they lost during the event, which is the usual stand-in for dehydration. Blood sodium afterwards leaned slightly lower in those who cramped, by a margin the analysis could not tell apart from no difference at all. Potassium and magnesium after the race were, if anything, slightly higher in the athletes who cramped. The one thing that did predict a cramp was having cramped before: those athletes had more than four times the odds of cramping again. [4]
Know where those athletes come from, because the total flatters the result. One of the nine studies is a review of 10,533 medical-tent records from the Ironman World Championship between 1989 and 2019, 2,863 of them with cramp. [21] Set beside the meta-analysis’s totals, that one study supplies more than nine in every ten of the athletes (our arithmetic). These were athletes who ended up in a medical tent, compared with one another, and the meta-analysis rates the study at high risk of bias. [4] It also does not say quite what the pooled result says. By its own summary the athletes with cramp had lost more weight than the rest and did not differ in blood sodium or potassium, and its authors write that their finding on dehydration “contradicts current literature”. [21] So on sodium the largest study and the pooled result agree: no link. On fluid loss they do not.
Read that the way its authors do. They rated five of the nine studies at high risk of bias, meaning the way a study was run could have skewed its answer. They graded the body-weight and blood-sodium results as moderate evidence, the second of four steps on the scale they used, with the studies disagreeing a good deal among themselves. They say most of their findings of no link rest on too little evidence to rule a factor out, and that they pooled studies of who cramps, not trials of a drink. On supplements they are still plain, citing the 2019 review above: the evidence “does not support a consistent benefit of electrolyte supplementation for preventing” exercise cramp. [4]
And the author of the 2009 review? Writing with four colleagues in 2022, that author describes cramp as the product of several factors, chiefly changes in how nerves drive a tired muscle, with dehydration and electrolyte loss contributing “to a much lesser extent”. [11] Less than the sales pitch says. Not nothing.
There is a competing explanation, and it fits better
If cramp is not salt, what is it? The leading alternative is altered neuromuscular control — the nerve signals controlling a fatigued muscle going haywire, rather than anything in the blood running low.
The evidence there comes from lab models where cramp is induced deliberately, from studies following athletes who cramp, and from animal work. [1] The review also notes that this hypothesis needs more evidence too. It is also an explanation this author helped to build: a 2022 review the same author co-wrote says the theory was proposed in 1997 and updated in this 2009 paper. [11] So we are not going to oversell a replacement its own author hedges.
What tipped the review against the salt explanation was not just the thin evidence for it. It was that the hypotheses “do not offer plausible pathophysiological mechanisms with supporting scientific evidence that could adequately explain the clinical presentation and management” of cramp. [1] In plainer terms: even if you accepted the studies, the story still would not account for how cramp actually behaves.
Now the part that is actually true
We are not going to pretend electrolytes do nothing, because one thing they do is measured and real.
Put enough sodium in a drink and you pass less of it as urine over the next few hours. There is a measure for this, the beverage hydration index, and it is simpler than it sounds. Drink about a quart of water (one litre) and collect the urine. Another day, drink the same amount of something else and collect again. Divide the first amount by the second. Water scores 1.00 by definition, and a higher score means less urine. In a randomised crossover trial, where each person tries every drink in random order, the highest-sodium drink scored 1.24 in twelve young adults. [2]
That is not a quarter more fluid kept, which is how this page first put it. The researchers weighed the urine. Over four hours the twelve passed about 3.2 lb after the water (1,443 g) and about 2.7 lb after the salty drink (1,229 g), having drunk about 2.2 lb (one litre). [2] About half a pound less, and in both cases more than they drank. They were already hydrated: fasted overnight, at rest in a lab, with about a pint of water (500 mL) taken an hour before.
The paper’s summary says the score rose as the sodium rose, “independent of glucose or AA content” (AA is amino acids). [2] Its own chart is less tidy. In the young adults the three lower-sodium drinks, two sugar-based and one not, sit close together just above water, and only the saltiest stands clear of them. [2] That is one drink in one age group. A cleaner test was published the same year: twelve young men were given drinks that differed only in their sodium, and the two saltier ones cut urine output against the two weaker ones. [14]
The twelve older adults in the trial, aged 60 to 85, did not show that pattern. Every sodium drink beat water for them too, but the saltiest was not the best: a drink with half its sodium scored highest, at 1.20. [2]
Nor is this a lone trial. The index was introduced in 2016, in a trial of 72 men: an oral rehydration solution, the salt-and-sugar drink sold for dehydration, cut urine output against water, and a sports drink with less than half its sodium did not. [12] A 2018 trial of 40 adults found the same split. [13] PubMed lists about a dozen more trials that use the index; we have not read those in full.
Look at who paid, because here it matters. The trial behind the 1.24 was part-funded by an unrestricted gift from Entrinsic Health Solutions, the company behind two of its four test drinks, including the one that scored 1.24, which the paper notes was not on sale. The other part was a US National Institutes of Health training grant, and the authors report no conflicts of interest. [2] The 2018 trial was supported by the same company, which donated its drink, and one of that paper’s authors was the company’s chief science officer. [13] The 2016 and 2019 trials from the index’s originators were funded, the second in part, by the European Hydration Institute, which a 2012 paper it funded describes as having The Coca-Cola Company as a funding partner; the sports drink that failed to beat water in 2016 was a Coca-Cola brand. [12][14]
Two things to hold onto, though. The 1.24 comes from twelve people, and every trial above tested people who were already hydrated and at rest. And retaining more fluid is only worth something if you are short of fluid — which is a question about your afternoon, not about the sachet.
The real sodium emergency is the opposite of the sales pitch
Here is where the marketing and the medicine actually diverge.
There is a documented, dangerous, well-studied sodium condition in sport. It is called exercise-associated hyponatremia, and it is blood sodium falling too low. A 2025 review screened 1,516 papers, read 345 in full, and pulled 220 cases out of 56 field studies. [3]
The review’s summary gives those events as lasting 5 to 29.5 hours, but its own table runs wider: marathons finished in about four hours at one end, hikes and races lasting days at the other. [3] By our count of that table the largest single group was ordinary marathon runners, 82 cases, finishing in 3 to 5.6 hours where a time is given. [3] Running and hiking, mostly. It is real, it puts people in hospital, and the way you get it is taking on a lot of fluid over a very long day.
Not always a long one. An international consensus statement lists cases among slower finishers of a half marathon and of a sprint triathlon, events of two to three hours, and one after a hot-yoga class. [16]
Which is worth sitting with, because the protection is not more sodium. Both the Wilderness Medical Society’s guideline and the consensus statement put the cause in drinking more than you lose. [15][16] The guideline’s most firmly graded advice on prevention is to avoid overdrinking, and for most people it recommends drinking to thirst. [15] Extra sodium, it says, will not prevent the condition if the overdrinking continues. [15] Nor will a sports drink, which is far less salty than blood. [16] The guideline does want salty snacks or drinks on hand at long, hot events, and says in the same breath that they will not prevent the condition in someone who overdrinks. [15]
Severe cases are a medical emergency. They are treated by medical staff, with a concentrated salt solution given into a vein, and both documents warn that giving more water or sports drink to someone in that state can make it worse. [15][16] That is hospital treatment, not a job for a packet. The consensus statement’s message to athletes, coaches and parents is that a suspected case needs immediate medical attention. [16]
And the cramp belief has cost lives. The consensus statement records three deaths from this condition among US high-school football players between 2008 and 2014; the players had been encouraged to drink large volumes of fluid and sports drinks to prevent or relieve cramp. [16]
The 2025 review also lists the milder symptoms: nausea, dizziness, headache, feeling weak. [3] Three of those, headache, dizziness and weakness, are on the list of “potential symptoms of mild to moderate dehydration” on the science page of one stick-pack seller, Liquid I.V., as we read it on 30 September 2026. So complaints a seller files under too little water are also early signs of too much.
The verdict
Unsupported, for the claim that electrolyte drinks prevent muscle cramp.
Be clear about which part that covers. The cramp story, one of the things these packets are sold on, rested in 2009 on anecdotes, eighteen cases and a study of ten, with four prospective studies pointing the other way. Seventeen years on, a pooling of nine studies still finds no consistent link between cramp and blood sodium. In the one trial of the five that worked a muscle until it cramped, no fewer men cramped with the drink than with no fluid at all. The other trials of drinks are small, mostly paid for by companies that sell drinks, and mostly about cramp made in a lab.
None of that proves salt plays no part. The authors of the pooled analysis say their evidence is too thin to rule a factor out, [4] its largest study found that the athletes who cramped had lost more weight, [21] and the 1936 mill report had salt working for men labouring in extreme heat. [5] But the claim as sold is that the drink prevents the cramp, and that has not been shown. That claim does not stand up.
The hydration claim does, in a narrow form. In four trials on this page, drinks with more sodium cut urine output against water or against less salty drinks, and in two of them a sports drink did not beat water. [2][12][13][14] The best-known number, 1.24, is twelve hydrated young adults passing about half a pound less urine over four hours (214 g). What that does not establish is that a person who is not losing much sweat needs help holding onto fluid at all.
So the honest version is not “electrolytes are a scam”. It is that they solve a problem sized by how much you sweat — and they are sold to everyone, at a price, on a cramp claim that a 2009 review found thinly supported and that the seventeen years since have not rescued.
Then there is the sodium itself. The drink behind the 1.24 carried 60 millimoles of sodium per litre, the unit the paper uses, which works out to about 1,380 mg in the litre the volunteers drank (our arithmetic). [2] One seller, LMNT, puts 1,000 mg in each stick pack by its own ingredients page, and its home page carries the slogan “More Salt, Not Less.” (both read on 30 September 2026). The FDA’s Daily Value for sodium, the amount to stay under in a day, is less than 2,300 mg, and the FDA puts the average American at about 3,400 mg already. [18] We have not tested the more-salt claim on this page. Our blood-pressure verdict reports what happened in trials where people cut sodium: pressure came down.
Who this verdict covers: healthy adults who are not sweating hard for hours. For people who are, the athletic trainers’ position statement says exercise lasting under an hour should need nothing but water, that longer or harder sessions may benefit from electrolytes, carbohydrate or both, especially in extreme conditions, and that the evidence does not show athletes being helped by sodium beyond what they actually lose in sweat. [17] It recommends measuring a person’s sweat losses before supplementing, which is not what a stick pack does.
It does not cover three other groups. Older adults got a different result in the hydration trial above. [2] Fluid lost through vomiting or diarrhoea is a separate medical question, and this page does not rate it. And people starting a low-carbohydrate diet, a market one electrolyte brand’s own page title names, have not been tested, which is not the same as a test that failed: a 2025 scoping review found a physiological rationale for electrolytes there and a lack of clinical studies of their effect, and our own search of PubMed and ClinicalTrials.gov on 30 September 2026 found none either. [19]
If you have high blood pressure, kidney disease or heart disease, or take medicines that affect fluid or salt balance, the sodium in these products is a question for your own clinician, not for a web page. This is journalism, not medical advice.
Related: how much water should I drink a day · does sweating burn fat · magnesium benefits · colostrum benefits · every claim we’ve checked
This page was corrected on 30 September 2026 after an independent editorial review, and the most important change is about safety. We said that low blood sodium in sport “genuinely calls for sodium” and is “a condition of ultramarathons”. Neither is what the guidelines say. The cause is drinking more than you lose; the firmest advice is to avoid overdrinking and, for most people, to drink to thirst; extra sodium does not prevent it while the overdrinking continues; and severe cases are an emergency treated by medical staff. In the review we cited, the largest group of cases was marathon runners, not ultramarathon runners. We also misreported the hydration trial. Its 1.24 is a ratio of urine volumes in twelve young adults, about half a pound less urine over four hours (214 g), not “a quarter more fluid retained” in twenty-four people; the older half of the trial did not show the rise with sodium; and it is not a lone trial.
The evidence panel said industry funding was not stated in our sources. It was: the trial behind the 1.24 was part-funded by the company behind the drink that produced it, and an author of the hyponatremia review declares ties to sports-drink and electrolyte companies. We called that review systematic; it calls itself a narrative review. We called the hydration trial paywalled; it is free to read, and we had worked from its abstract. The headline counted “18 case reports”; the 2009 review says case series totalling 18 cases, and that the evidence comes mainly from them. And we presented that 2009 tally as the present state of the evidence. The page now reports what has been published since, in both directions and with who paid, including five small trials of drinks and a meta-analysis of nine studies first published on 3 September 2026, most of whose athletes come from one race’s medical-tent records. The title, the summary, the evidence panel and the account of how the claim travelled were rewritten to match, the sodium in these drinks is now set against the daily limit, and the verdict now says who it does and does not cover. The claim this page reported to search engines as the one it had rated, that you are chronically dehydrated and water alone is not enough, was one it never tested; that label now names the cramp claim. The rating is unchanged: Unsupported, for the claim that electrolyte drinks prevent cramp. The verdict now also says what that rating does not mean: it does not say salt has been shown to play no part.