Does Prednisone Raise Blood Pressure? Sometimes a Little, at Higher Doses

“Will prednisone raise blood pressure?” is typed into Google about 6,600 times a month in the United States (from a paid keyword database, pulled 20 October 2026) [1]. People ask it on the day a course starts, and three practical questions sit behind it: how much, how fast, and will it last?
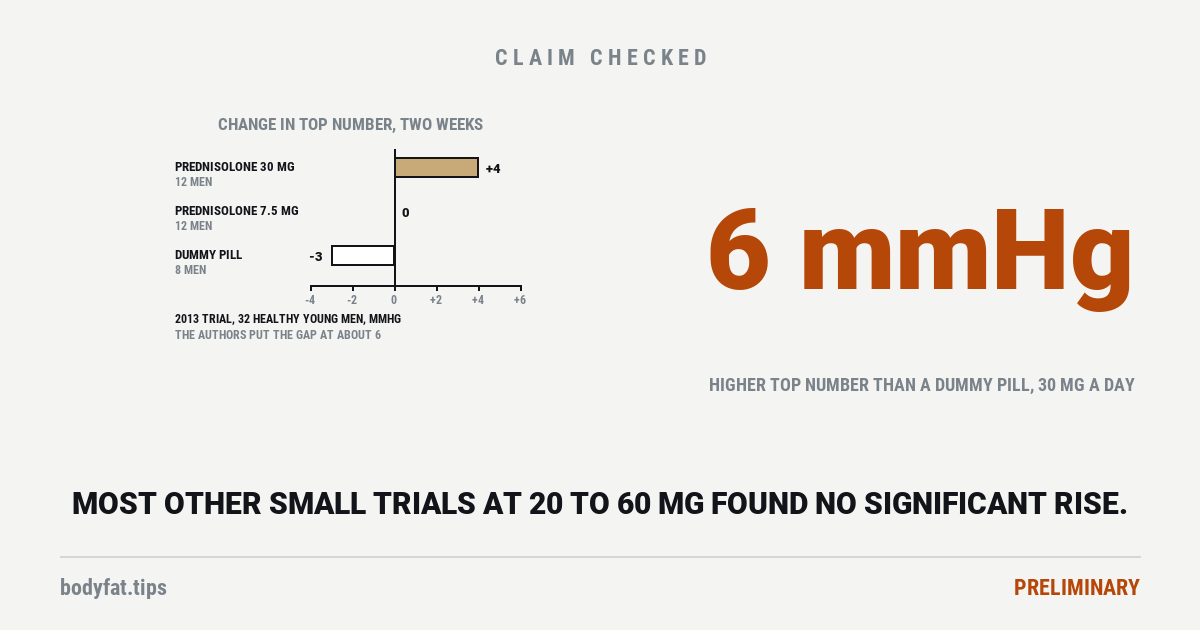
Sometimes, at higher doses, by a few points on average, and the small trials disagree. At 7.5 mg a day or less, the trials found no significant rise. In a placebo-controlled trial that compared two doses, two weeks of 30 mg a day of prednisolone, prednisone’s close relative, left the top number about 6 points higher than a dummy pill did, in 12 healthy young men against 8 on the dummy pill, while 7.5 mg a day did not raise it [2]. Most other placebo-controlled studies in healthy volunteers found no significant rise, at doses up to 60 mg a day [3] [4] [5], though three found blood pressure higher, at 25 to 50 mg a day [6] [7] [8]. These counts are of the synthetic steroids; studies that gave volunteers hydrocortisone, the natural hormone, are a separate set, not counted here. Pooled over five trials of two years each, low doses left the average pressure 0.4 points lower than a dummy pill or no steroid, a difference within chance [9].
Blood pressure comes as two numbers. The top one, systolic, is the pressure while your heart pushes; the bottom one, diastolic, is the pressure between beats. Both are in mmHg, millimetres of mercury, the unit on every monitor. Prednisone is a glucocorticoid, a steroid medicine made to act like your own cortisol. Prednisolone, methylprednisolone and dexamethasone are its relatives, and the studies here use all four. It is not the muscle-building kind of steroid, which has its own blood-pressure verdict.
This is journalism, not medical advice. If you take prednisone, do not stop it suddenly or change the dose on your own. Its label warns patients not to stop abruptly, because a course can switch off your own cortisol and stopping too fast can leave you short of it [10], as our cortisol detox verdict explains. A high reading on steroids is a reason to call the prescriber, not a reason to stop.
Will prednisone raise my blood pressure?
A clean test of the question is a 2013 Dutch trial. Thirty-two healthy young men, average age 21, took prednisolone 30 mg a day (12 men), 7.5 mg a day (12) or a dummy pill (8) for two weeks, and neither the men nor the people measuring them knew who was taking what [2]. On 30 mg the top number went from 120 to 124. On the dummy pill it went from 126 to 123. The authors put the difference at about 6 points, unlikely to be chance; the group averages moved 7 points apart, by our arithmetic [2]. On 7.5 mg the top number started at 124 and ended at 124. The bottom number did not rise significantly on either dose [2].
Read that once more, because part of the gap is the dummy-pill group’s number falling. Single readings wander, which is why a trial needs a comparison group and why one reading on your own arm can mislead you. Our guide to measuring blood pressure at home covers how to take a reading worth acting on, and our white-coat verdict explains why readings in a clinic run high.
Other small studies of healthy volunteers split, and the split is worth seeing whole. Some found blood pressure higher. In 1989, six volunteers on prednisolone 40 mg a day saw the top number rise 13 points, and methylprednisolone, triamcinolone and dexamethasone raised it 6 to 10 [11]; that study had no dummy-pill group. A 2005 trial gave 25 men dexamethasone 3 mg twice a day, as strong as about 40 mg of prednisolone by the dexamethasone label’s own table [12], or a dummy pill for five days; its summary reports a rise in the top number and gives no figure [7]. A 2026 trial gave ten men prednisolone 12.5 mg twice a day and a dummy pill, five days each, in random order. At night the top number averaged 123 on prednisolone and 116 on the dummy pill, with a P value of 0.05, right at the line researchers use for “probably not chance” [6]. A 2023 Danish trial gave 24 men with overweight or obesity, otherwise in good health and averaging 44, prednisolone 50 mg a day or a dummy pill for ten days, eight to each, beside a third arm testing a turmeric extract. Measured lying down at the end, the bottom number came out 6 points higher on prednisolone than on the dummy pill, unlikely to be chance, and the top number 6 points higher, a difference that could be chance; as in the 2013 trial, part of the gap is the dummy-pill group’s readings falling [8]. Three more found a rise against the same people’s readings without the drug, with no dummy pill standing in for the steroid: a week of dexamethasone 3 mg a day took six men’s mean pressure, an average across the heartbeat, from 82 to 91 [13]; four days of prednisolone raised 11 men’s pressure over 24 hours, though not significantly while they were awake [14]; and three days of dexamethasone 8 mg a day raised the top number on a monitor worn through the day in 18 adults [15].
Others found no significant rise. In 1988, eight men took prednisone 50 mg a day, a salt-retaining steroid called fludrocortisone and a dummy pill, nine days each, in random order; blood pressure rose significantly on the fludrocortisone and not on the prednisone [4]. In 1995, 13 volunteers took prednisone 20 mg a day and a dummy pill for a week each, in random order, and the authors report blood pressure “unaffected” [3]. Six men given dexamethasone and a dummy pill for two days each, wearing 24-hour monitors, showed no significant difference [16], and neither did 24 men given a low and a high dose of dexamethasone and a dummy pill for four and a half days each [17]. Fifty men flown to about 11,300 feet (3,450 m) on prednisolone at 10 to 40 mg, low-dose dexamethasone or a dummy pill saw their blood pressure rise there by a similar amount whatever they took [18]. Healthy men on dexamethasone 3 mg a day for five days had higher readings than at the start, but not higher than on a dummy pill [19]. Twelve active men on prednisone 60 mg a day and a dummy pill, a week each, showed no increase in the top number, the authors report [5]. A drug company’s 2016 study gave 37 healthy adults prednisone at 2.5 to 60 mg a day or a dummy pill for a week at a time and reports “no clinically significant changes in vital signs”, a judgement rather than a statistical test [20]. Two more are harder to file, because every man in them took the steroid. A 2023 trial gave 32 men prednisolone 20 mg a day for a week, half of them with a test drug, and found no significant change in their 24-hour readings within either group. Its authors still read it as a rise on prednisolone alone: at night the bottom number went up 4.6 points on average in the men given a dummy pill in place of the test drug and 0.7 in those on the test drug, a gap unlikely to be chance [21]. And a 2025 Swiss trial gave 18 lean young men prednisone 30 mg a day for a week twice, once with a diabetes drug and once with a dummy pill; with the dummy pill the top number rose 0.8 points on average and the bottom number 4.2, changes the paper does not test [22].
Read together, two things stand out, by our reading. Studies that measured people against their own earlier readings mostly found a rise; studies with a dummy pill mostly did not; and the 2006 dexamethasone study saw both at once, a rise from the starting readings that was not there against the dummy pill [19]. And dose does not sort them. The dexamethasone label puts 0.75 mg of dexamethasone level with 5 mg of prednisolone [12], so by our arithmetic the rises came at about 20 to 53 mg a day of prednisolone’s strength, and the studies with no significant rise used 2.5 to 60 mg where their summaries give a dose. All of them are small.
| Study | Who, what dose, how long | What blood pressure did |
|---|---|---|
| Dose trial, 2013 [2] | 32 healthy men, average age 21: prednisolone 30 mg (12 men), 7.5 mg (12) or a dummy pill (8); two weeks | 30 mg: 120 to 124. 7.5 mg: 124 to 124. Dummy pill: 126 to 123. The authors put 30 mg about 6 higher than the dummy pill |
| Volunteers, 1989 [11] | 6 healthy volunteers: prednisolone 40 mg, then three other steroids; five days each; no dummy pill | Up 13 on prednisolone; up 6 to 10 on the other three |
| Volunteers, 1992 [13] | 6 healthy men: dexamethasone 3 mg a day, about 20 mg of prednisolone’s strength, for a week; no dummy pill | Mean pressure from 82 before to 91 on day 7 |
| Volunteers, 1995 [14] | 11 healthy men: prednisolone for four days, dose not given in the summary; 24-hour monitor before and after; no dummy pill | Higher over 24 hours and during sleep; not significantly higher while awake |
| Volunteers, 2005 [7] | 25 healthy men: dexamethasone 3 mg twice a day or a dummy pill; five days | Rose on dexamethasone; the summary gives no figure |
| Volunteers, 2006 [15] | 18 healthy adults: dexamethasone 8 mg a day, about 53 mg of prednisolone’s strength, for three days; compared with the same people without it | Top number up on a monitor worn through the day; the summary gives no figure |
| Volunteers, 2026 [6] | 10 healthy men: prednisolone 12.5 mg twice a day and a dummy pill, five days each, in random order | At night, 123 on prednisolone against 116 on the dummy pill; P of 0.05 |
| Overweight volunteers, 2023 [8] | 24 men with overweight or obesity, average age 44: prednisolone 50 mg or a dummy pill, ten days, eight to each, and a third arm adding a turmeric extract; readings lying down | Bottom number 6 higher than on the dummy pill, unlikely to be chance; top number 6 higher, which could be chance |
| Volunteers, 1988 [4] | 8 healthy men: prednisone 50 mg, a salt-retaining steroid and a dummy pill, nine days each, in random order | No significant rise on prednisone; a significant rise on the salt-retaining steroid |
| Volunteers, 1995 [3] | 13 healthy volunteers: prednisone 20 mg and a dummy pill, a week each, in random order | “Unaffected”, the authors write |
| Volunteers, 1997 [16] | 6 healthy men: dexamethasone and a dummy pill, two days each, in random order, with 24-hour monitors; dose not given in the summary | No significant difference: 128 on dexamethasone against 135 on the dummy pill, averaged over 24 hours |
| Volunteers, 1999 [17] | 24 healthy men: a low and a high dose of dexamethasone and a dummy pill, four and a half days each, in random order | No significant difference, at rest or in exercise |
| Volunteers at altitude, 2002 [18] | 50 healthy men flown to about 11,300 feet (3,450 m): prednisolone 10, 20 or 40 mg, dexamethasone 0.5 mg or a dummy pill; five days | Rose at altitude by a similar amount whatever they took |
| Volunteers, 2006 [19] | Healthy men: dexamethasone 3 mg a day, about 20 mg of prednisolone’s strength, or a dummy pill; five days; the summary gives no count | Up from the starting readings, but not compared with the dummy pill |
| Volunteers, 2015 [5] | 12 physically active men: prednisone 60 mg and a dummy pill, a week each, in random order | No increase in the top number, the authors report |
| Volunteers, 2016 [20] | 37 healthy adults, 7 of them women: prednisone 2.5 to 60 mg or a dummy pill, a week at a time | “No clinically significant changes” in seated readings: a judgement, with no statistical test reported |
| Volunteers, 2023 [21] | 32 healthy men, every one on prednisolone 20 mg for a week, half also on a test drug; 24-hour monitor before and on day six | Night-time bottom number up 4.6 with a dummy pill and 0.7 with the test drug, a gap unlikely to be chance; no significant change within either group; no group went without prednisolone |
| Volunteers, 2025 [22] | 18 lean young men, every one on prednisone 30 mg for a week twice, once with a diabetes drug and once with a dummy pill | On prednisone with the dummy pill, top number up 0.8 and bottom number up 4.2 on average; the paper tests neither change |
| General practice records, 2015 [23] | 6,914 adults not on blood-pressure pills, first three months of a course; started at 29 mg a day on average | 133 before; 135, 133 and 133 in months one to three; the adjusted rise under 1 point |
| Five trials pooled, 2023 [9] | 1,112 people with rheumatoid arthritis: 7.5 mg a day or less, or a dummy or no steroid; two years | The average pressure rose about 2 in both groups; 0.4 lower on steroids, a difference within chance |
Beyond healthy volunteers, a 1994 pooling of 93 placebo-controlled steroid trials, 6,602 patients, 3,335 of them given a steroid or ACTH, a hormone that makes the body release its own cortisol, at any dose for any length of time, and 3,267 a dummy, found high blood pressure reported more often on the steroid [24]. A 2015 paper reads its figure as roughly double the odds [23]. We read the pooling’s summary, which two printings give with different P values [24]. A 2022 pooling of nine placebo-controlled trials, 1,975 people, searched to January 2020, leaned the same way, at 1.68 times the odds of high blood pressure on the steroid, but with a range from 0.96 to 2.95 that includes no difference at all [25]. Its own summary calls the link significant, which that range does not support. No single trial dominates it: on its chart the two biggest carry about a fifth of the weight each, one of them the 1999 lung-disease trial below, and three of the nine are also in the 2023 low-dose pooling further down, by our reading of the two reference lists [25] [9].
How much does prednisone raise blood pressure in patients, and how fast?
Trials in healthy volunteers show what the drug can do. A 2015 study of British general practice records shows what happened to patients. Of 77,058 adults prescribed a steroid tablet for at least three months between 2004 and 2012, 6,914 who were not on blood-pressure pills had a reading in the year before the course and another in its first three months [23]. Most were on prednisone or prednisolone, starting at 29 mg a day on average. Their average went from 133/78 before to 135/79 in the first month and 133/78 in the second and third. Allowing for age, weight, dose and illness, the rise in the top number was under one point [23]. In 16,351 people already on blood-pressure pills, the average was 140/78 before and 139/77 in each of the first three months [23].
That average hides people at both ends. In 4% of the 6,914, the top number rose by 30 points or more; in 3.5%, it fell by as much [23]. The authors suspect the illness being treated, and the habit of an unusual reading being followed by an ordinary one, explain much of both, and conclude that the early rise “seems clinically nonsignificant” [23]. The changes did not depend on the starting dose [23].
A trial in patients puts a number on longer courses. In 1999, 271 American veterans in hospital with a flare of chronic lung disease were given a two-week or an eight-week steroid course, or a dummy pill [26]. High blood sugar needing treatment was the commonest complication, 15% against 4% [26]. High blood pressure, as the 2015 paper reports the trial, developed in 5% of the 80 on the eight-week course and 4% of the 111 on the dummy pill [23]. A 2023 French trial compared a two-day course with another drug rather than a dummy pill: 111 hospital patients aged 65 or over, median age 88, with a painful crystal arthritis took prednisone 30 mg a day for two days or colchicine, knowing which they had, and high blood pressure was recorded as a side effect in 6 of 54 on prednisone and 1 of 55 on colchicine [27]. The trial reports no statistical test of that gap. By our arithmetic, a standard test for counts this small gives a P value of about 0.06, just the wrong side of the line researchers use for “probably not chance”; and these were very old patients, in hospital and in acute pain. A 2014 Dutch trial looked at men with the metabolic syndrome, a cluster of a large waist, high blood pressure, high blood sugar and unhealthy blood fats: median age 58, half of them already on blood-pressure pills. Twenty-six took prednisolone 30 mg a day for two weeks, 14 of them with a diabetes drug, and 12 took dummy pills; at two weeks neither prednisolone group’s blood pressure differed significantly from the dummy-pill group’s, and the authors note that the blood-pressure pills may have masked a rise [28].
What is considered a high dose of prednisone, and do low doses raise blood pressure?
The rheumatology studies on this page treat 7.5 mg a day of prednisone, or the same strength of another steroid, as the top of a low dose, and 7.5 to 30 mg as medium [29] [9]. The prednisone label notes that the dosage range is the same for prednisone and prednisolone [10]. The record studies’ top band starts at 7.5 mg a day [30] or 15 mg [29], and most of the volunteer studies that found a rise used 25 to 40 mg a day of prednisolone or its equivalent [2] [11] [6], though at 50 mg one placebo-controlled study found no significant rise [4] and another found the bottom number higher [8], and one at 60 mg found no increase in the top number [5].
At the low end, the strongest evidence on this page is a 2023 pooling that went back to the individual patients’ data from five trials of two years each: 1,112 people with rheumatoid arthritis, given 7.5 mg a day or less, or a dummy pill or no steroid [9]. It measured mean arterial pressure, an average of the pressure across a whole heartbeat that sits closer to the bottom number than the top. It rose about 2 points in both groups. The difference between them was 0.4 points lower on steroids, with a confidence interval, the range the true average probably sits in, from 3.0 lower to 2.2 higher [9]. The authors concluded that low doses “do not increase blood pressure”; what the trials measured is no significant difference, with a small rise still inside the range. Weight did move: about 2.4 lb (1.1 kg) more on the steroid over two years [9].
Before printing a pooled figure we look for the biggest study inside it. Here it is the GLORIA trial, 451 of the 1,112 people, about 41% by our arithmetic from the pooling’s own reference list [9] [31]. GLORIA gave people aged 65 and over 5 mg of prednisolone or a dummy pill for two years, and, of the 449 who took the capsules, recorded new high blood pressure 5 times in the 224 on prednisolone and 7 times in the 225 on the dummy pill [31]. One of the smaller trials in the pooling went the other way on that count: in a German trial that randomised 192 people between 5 mg and a dummy pill, high blood pressure was listed as a side effect in 6 people on prednisolone and 2 on the dummy pill [32]. Counts that small swing easily, which is why the pooled measurement carries more weight than either.
The large record studies draw the line in the same place. In 17,760 British people with rheumatoid arthritis, followed from diagnosis, recent steroid use went with new high blood pressure about 17% more often: a hazard ratio, how often it happened over time compared with people not on steroids, of 1.17, with a range of 1.10 to 1.24 [29]. Split by dose, below 5 mg a day it was 1.10 and at 5 to 7.4 mg 1.07, neither significant; at 7.5 to 14.9 mg it was 1.18 (1.08 to 1.29) and at 15 mg or more 1.36 (1.18 to 1.56) [29]. People on steroids in that study had their blood pressure measured no more often than people off them, so the extra cases were not just extra checking [29]. A German survey of 1,066 people with rheumatoid arthritis found more self-reported rises in blood pressure only above 7.5 mg a day [33].
Does long-term prednisone cause high blood pressure?
It goes with more of it. The largest cohort on this page to count new cases of high blood pressure followed 71,642 adults in England with one of six inflammatory diseases, none with high blood pressure at the start, for a median of six and a half years [30]. About a third, 24,896 people, developed it. The more steroid people had taken in total, the more often: about 14% more often at the lowest total, 20% at the middle and 30% at the highest, against time off steroids [30]. By the day’s dose, only 7.5 mg or more stood out, at 8% more often (1.01 to 1.14) [30].
Not every group pointed up. In people with polymyalgia rheumatica, a muscle-pain condition of older adults, daily doses of 7.5 mg or more went with less high blood pressure (0.83, from 0.75 to 0.92), and the paper notes an earlier study of people with asthma, from the same records, that found no increase in risk [30]. These are records, not trials: people on more steroid are usually sicker, and illness and other drugs move blood pressure too. The authors also write that they could not look at whether the effect reverses [30].
How do glucocorticoids affect blood pressure?
The label puts blood pressure and salt in the same sentence. “Average and large doses of hydrocortisone or cortisone can cause elevation of blood pressure, salt and water retention,” it says, adding that these effects “are less likely to occur with the synthetic derivatives except when used in large doses,” and that cutting salt may be necessary [10]. Prednisone is one of those synthetic derivatives. Dexamethasone, its own label says, “almost completely lacks” the salt-retaining property of hydrocortisone [12].
So why did dexamethasone raise blood pressure in two of the volunteer studies [11] [7]? In the 1989 study, all four synthetic steroids raised it while the volunteers passed more salt, not less, gained no weight, and their plasma, the liquid part of the blood, did not expand; the authors concluded that salt retention is not essential for steroids to raise blood pressure [11]. The 2013 trial points at the small blood vessels instead: the more prednisolone blunted their response to insulin, the more the top number rose [2]. That is a correlation in one small trial, a lead rather than a proof.
Does cutting salt help, then? A French trial tested it directly. Forty-nine patients starting steroids at around 55 mg of prednisone a day ate under 3 g of salt a day for three weeks and over 6 g for three weeks, in random order. Their blood-pressure changes were not significantly linked to how much salt they ate [34]. An Iranian trial of 60 people on steroids found blood pressure different after ten weeks on the DASH diet, rich in fruit, vegetables and low-fat dairy, than on a control diet; its summary gives no figures [35]. Cutting salt helps blood pressure in general, as our verdict on lowering blood pressure naturally sets out. Whether it blunts the steroid’s rise in particular, these two small trials do not settle.
Does blood pressure go back down after you stop?
The randomised evidence on stopping comes from kidney transplants, where steroids are part of the anti-rejection mix. A 2010 pooling of 34 trials and 5,637 transplant patients found, in the trials that counted it, that avoiding or withdrawing steroids made high blood pressure about 10% less common, a relative risk, how often it happened in one group divided by how often in the other, of 0.90 (0.85 to 0.94), at the price of more rejection episodes [36]. Those patients were also on other drugs that raise blood pressure. The NHS tells patients that appetite and the way the body holds water should return to normal after stopping [37], which is a statement about weight and water, not a blood-pressure measurement. In what we read of the studies of ordinary courses on this page, one set out to measure blood pressure after the pills stopped: the 2014 trial in men with the metabolic syndrome measured again two weeks after prednisolone ended, to see whether its effects reversed. Its text says only that the men who had taken prednisolone with a diabetes drug, and were still taking the diabetes drug, then had a lower top number than the dummy-pill group, not significantly, as did the men on the diabetes drug alone; the figures for prednisolone alone are in a supplementary table we could not read [28]. The volunteer studies’ last readings come no later than the day after the last dose, which measures the course rather than the recovery [20] [8].
What about inhalers and eye drops?
The evidence on this page is about tablets. For inhalers, one record study is worth knowing. In 4,593 pregnancies of women with asthma in Quebec, inhaled steroids were not linked to high blood pressure in pregnancy, an odds ratio of 1.02 (0.77 to 1.34), where 1.00 would mean no difference in the odds, while steroid tablets were, at 1.57 (1.02 to 2.41) [38]. That is pregnancy only, and records rather than a trial.
For eye drops, the US eye doctors’ professional academy answers that most drops are not absorbed into the bloodstream enough to cause significant side effects, while a mild rise in blood sugar or blood pressure is possible [39]. One word confuses people here. Steroid drops, and long steroid courses, can raise the pressure inside the eye, called ocular hypertension. That is a glaucoma risk, checked by an eye doctor, not your blood pressure; the prednisone label asks for eye-pressure checks when a course runs past six weeks [10].
Does prednisone interact with other medications?
Its label lists many. Two matter to people watching their blood pressure. With water pills (diuretics), both drugs can lower potassium, and the label asks for close watching [10]. With aspirin or other anti-inflammatory painkillers, the risk of stomach side effects rises [10]. A pharmacist can check your own list against it.
What are prednisolone tablets used for, and is prednisone a steroid?
Yes, prednisone is a steroid, a glucocorticoid, as above, and the NHS stresses that corticosteroids are not the same as anabolic steroids [37]. The prednisone label lists uses across hormone, joint, skin, allergy, eye, lung, blood, bowel and kidney conditions, from asthma flares to rheumatoid arthritis [10]. The NHS describes prednisolone tablets the same way: a wide range of problems, including allergies, blood disorders, skin diseases, inflammation and certain cancers, and preventing rejection after a transplant [37].
What are the common side effects of 20 mg of prednisone, and when do they start?
Twenty milligrams a day sits in the medium band [29]. The NHS lists as common, in more than 1 in 100 people, weight gain, indigestion, trouble sleeping, restlessness, sweating a lot and mild mood changes, and lists high blood pressure among the side effects of taking it for a long time [37]. Some start straight away and others, such as a rounder face, after weeks or months, it says [37]; our cortisol face verdict covers that change. For blood pressure at 20 mg a day, or dexamethasone’s equivalent, placebo-controlled volunteer studies found no significant rise after up to a week [3] [19], one at altitude found the rise there similar whatever people took [18], and a 2023 study with 24-hour monitors in which every man took it found no significant change within its groups, though its authors report night-time pressure rising more without a test drug than with it [21]; a 1992 study found a rise at dexamethasone’s equivalent of 20 mg, against the men’s own starting readings [13]. The studies that saw rises within five days to two weeks mostly used 25 to 40 mg a day of prednisolone or its equivalent [11] [6] [2].
If your blood pressure goes up on prednisone
The label, which is written for prescribers, says that cutting salt and adding potassium may be necessary, and it asks for caution in people who already have high blood pressure [10]; the NHS asks people to tell their doctor or pharmacist before starting if they do [37]. Whether you need less salt or more potassium is your prescriber’s call; do not begin potassium supplements on your own. A headache is a poor guide to your reading except at 180/120 or above, where it becomes an emergency, as our headaches verdict found. A properly taken reading is the thing to bring to your prescriber, who can weigh it against the illness the steroid is treating.
Who these studies were done on
Of the four volunteer trials that set a steroid against a dummy pill and found a rise, three were in healthy young men, aged 18 to 39 [2] [7] [6], and one in men with overweight or obesity, otherwise in good health, average age 44 [8]. The placebo-controlled volunteer studies that found no significant rise were small too, and mostly in men; one included 7 women among 37 adults [20]. The two-week trial in men with the metabolic syndrome had a median age of 58 [28]. The low-dose trials were in people with rheumatoid arthritis, average age 61 in the pooling, 68% of them women, and 72 in GLORIA [9] [31]. The records studies were British adults, mostly women: average age 60 in the 2015 study’s 6,914 not on blood-pressure pills and 72 in those on them, and about 56 and 51 in the two cohorts [23] [29] [30]. In children, a 2016 review of courses of up to 14 days counted 144 of 186 children with a rise in four studies that measured blood pressure and no rise in 183 in two others; the studies defined a rise differently, and these are counts, not comparisons with a dummy pill [40].
So read yourself against them. If you are an older adult on a low dose for arthritis, the two-year trials were about people like you. If you are starting a week or two of 20 to 40 mg for a flare, the closest evidence is the volunteer studies, the general practice records, one small open trial in older patients and one small trial in men with the metabolic syndrome. The volunteer studies split, from a 13-point rise in one with no dummy pill to no significant rise in most of those with one; the records found under a point on average in patients’ first months; the open trial recorded high blood pressure more often on prednisone than on another drug, in hospital patients with a median age of 88, a gap it did not test [27]; and in the men with the metabolic syndrome two weeks of 30 mg a day did not raise it significantly against a dummy pill [28].
If the trials find a few points, why do some people see a big jump?
This section is the desk’s own reasoning, and it is labelled as such. The trials that found a rise put it at a few points, and many found none that was significant; forums are full of people whose readings shot up. Here are three ways those fit together, each rated.
Answer one: the swings run both ways. In the British records, 269 people’s top number rose by 30 points or more in the first three months, from 123 to 161 on average, and 234 people’s fell by as much, from 154 to 116 [23]. A jump is easy to notice and pin on a new pill; a fall rarely gets a forum post. The swings are measured. That a rise gets remembered and blamed on the pill while a fall does not is the authors’ suggestion about doctors, and our surmise about patients [23].
Answer two: the illness moves the reading too. In the low-dose trials, the average pressure rose about 2 points on the dummy pill as well as the steroid [9]. In polymyalgia rheumatica, higher doses went with less high blood pressure [30], and in people treated for cancer the average fell after starting steroids [23]. Each of those is measured. That the illness, its pain or its other drugs explain a particular jump is a surmise.
Answer three: the drug and the dose. The people whose top number rose 30 points were more often on prednisone or prednisolone than those whose number fell 30, 93% against 78%, odds about five times higher [23]. That is measured, in records rather than a trial. The authors note that prednisolone holds on to more salt than the other synthetic steroids [23]; that this explains it is unproven, since the 1989 study raised blood pressure without salt [11].
Put the three together and here is what we think is true, stated plainly so you can disagree with it: at higher doses prednisone may lift the average blood pressure by a few points, and it leaves most readings near where they were, so a jump of 20 or 30 points is not something the average explains, and your own reading, taken properly, is the number to bring to your prescriber.
What we could not find, and would like to: a placebo-controlled trial in patients, not healthy volunteers, that measured blood pressure with a 24-hour monitor before, during and after an ordinary one- or two-week course [41]. Of the studies we found that put 24-hour or all-day monitors on healthy volunteers, two found pressure higher, after four days of prednisolone [14] and three days of dexamethasone [15]; one found no significant difference from a dummy pill over two days of dexamethasone [16]; and in one, in which every man took prednisolone 20 mg for a week, night-time pressure rose more with a dummy pill than with a test drug, though not significantly within either group [21]. The 2026 trial reports night-time readings, higher on prednisolone, without saying in its summary how they were taken [6]. If you know of the trial we describe, the corrections line on this site is open.
Where “prednisone raises your blood pressure” came from
We could not trace who first said it. The label’s warning is written about cortisone and hydrocortisone, the natural hormones, and carried over to prednisone with a caveat about the synthetic ones [10]. The volunteer studies we read have pointed both ways for decades: in 1988 a placebo-controlled study of prednisone at 50 mg a day found no significant rise [4], and in 1989 a study with no dummy pill found prednisolone raised the top number 13 points in five days [11].
The number that travels with it is 30%. A drug-discount page that Google’s answer cites says that in a “large review” more than 30% of people on long-term steroid tablets had high blood pressure [1]. That 2017 review was paid for by a drug company, two of its five authors were the company’s employees, and it took its table’s figures from a 2011 review; it ends by suggesting that ways to reduce reliance on corticosteroids may be worth exploring [42]. The 2011 review lists high blood pressure among side effects reported in more than 30% [43]. A share of long-term users with high blood pressure is not the share that steroids caused: in the English records, a third of people developed it over six and a half years, and steroids added a modest share on top [30].
Then it spread as a flat yes. Google’s AI answer opens “Yes, prednisone can raise blood pressure” and gives fluid and salt retention as the first reason, citing a drug-information site, two drug-discount sites, a consumer health site, a hospital’s health blog and the NHS [1]. A social-media group post on the first page of results is titled “If you take Prednisone it WILL raise your blood pressure.” [1] Much of what those pages say is sound: the dose matters, check your readings, do not stop suddenly. They go past the evidence in two places: salt comes first in the explanation although the volunteer study raised blood pressure without it [11], and “will” is not what the low-dose trials found [9], or what most of the placebo-controlled volunteer studies found [4] [3] [5].
And the answer sits beside a sale. The drug-discount page that quotes the 30% carries discount offers for prednisone on the same page [1]. Cheaper medicine is no bad thing; the point is that the page answering your question is also a shop.
None of this is aimed at anyone checking their blood pressure on prednisone. Wanting to know what a pill does to your numbers is the right instinct, and at higher doses some studies did find a rise. It is the certainty in the selling, and the borrowed 30%, that the evidence does not carry.
What this is rated, and what the rating covers
Preliminary — for the claim that prednisone raises blood pressure.
It is rated Preliminary because the evidence conflicts for the courses most people take. Among small studies of healthy volunteers, four placebo-controlled trials of synthetic steroids at 25 to 50 mg a day of prednisolone or its equivalent found blood pressure higher after five days to two weeks, three of them the top number and one the bottom number [2] [7] [6] [8], and four studies without a dummy pill found rises [11] [13] [14] [15]; eight placebo-controlled studies, at doses up to 60 mg a day, did not find a rise: six found no significant one, one judged the changes not clinically significant without a statistical test, and one, at altitude, found the rise there similar whatever people took [4] [3] [16] [17] [18] [19] [5] [20]. In two more, every man took the steroid; one reports night-time pressure rising more without a test drug than with it, the other small changes it did not test [21] [22]. In men with the metabolic syndrome, half on blood-pressure pills, two weeks of 30 mg a day did not raise it significantly against a dummy pill [28]. Two poolings of placebo-controlled trials lean toward more high blood pressure on steroids, the 1994 one significantly and the 2022 one with a range that includes no difference [24] [25]. In patients’ first months of a course the average rise was under a point [23], and at 7.5 mg a day or less the trials found no significant rise [9]. The steadiest signal comes from records: two large British studies found new high blood pressure more common at 7.5 mg a day and above [29] [30], and records show what happened alongside the drug, not that the drug caused it. It is not Unsupported, because the controlled studies that found a rise are real and the poolings and records lean the same way; it is not Supported, because for the claim as it circulates, at any dose and for any course, the evidence is not consistent.
Each part, rated alone, in words. That a short course raises it: Preliminary. In healthy volunteers over two days to two weeks the studies split as set out above, and dose does not sort them [2] [4] [5]. In patients, the average in the first months rose under a point [23], and an open trial of a two-day course in older patients recorded high blood pressure as a side effect more often on prednisone than on another drug, 6 of 54 against 1 of 55, a gap the trial did not test and that counts this small could produce by chance [27]; and in men with the metabolic syndrome two weeks of 30 mg a day did not raise it significantly against a dummy pill [28]. Small and conflicting.
That taking 7.5 mg a day or more goes with more new high blood pressure: Supported, as a link in records. Two large British record studies compared people’s time on that dose with their time off steroids, counting in one the three months after each prescription as well, and in their main analyses both found more new high blood pressure at 7.5 mg a day and above: more again at 15 mg or more in one [29], and more with higher total amounts in the other [30]. The limits are known. In the first, among the 5,860 people whose records could be linked to hospital clinic visits, a stand-in for how active the arthritis was, 7.5 to 14.9 mg fell just short of significance whether or not that was allowed for, and counting only diagnoses backed by repeat blood-pressure prescriptions left neither band at 7.5 mg and above significant, though both stayed on the side of more [29]. In the second, 7.5 mg and above was the only daily dose to stand out, at 8% more, and the authors found a steady climb with more drug only for the total amount taken; in people with polymyalgia rheumatica the link ran the other way [30]. Records cannot show that the steroid is the cause.
That low doses raise it, 7.5 mg a day or less: Unsupported, of the tested kind. Five two-year trials pooled found no significant difference from a dummy pill or no steroid, the two-week trial found no rise at 7.5 mg, and the record studies found no significant increase below 7.5 mg a day in their main analyses [9] [2] [29] [30]. The pooled range rules out a rise in mean pressure of more than about 2 points; it does not rule out a smaller one [9]. Other analyses of the same records moved both ways at low doses. In the English records, below 5 mg a day went with 11% less high blood pressure when new prescriptions for blood-pressure pills were counted as cases, and with 51% more, and 5 to 7.4 mg with 70% more, when everyone prescribed those pills was left out [30]; in the arthritis records, a shorter time window made the lowest band 16% more, just significant [29]. And in the English records the total amount of steroid taken over time went with more high blood pressure even at the lowest totals [30].
That blood pressure returns to normal after stopping: Preliminary. The randomised evidence comes from transplant patients, in whom stopping or avoiding steroids made high blood pressure about a tenth less common [36]; of the studies of ordinary courses on this page, one set out to measure blood pressure after the pills stopped, two weeks on, and its figures for prednisolone alone are in a table we could not read [28].
What is not rated here: inhalers, creams and eye drops, which the evidence on this page barely touches; why steroids raise blood pressure, where the label’s salt explanation and the volunteer study pull in different directions; and the frame in the section above, which is this desk’s reasoning from the evidence rather than a result the evidence delivered. It is marked as ours so that you can weigh it as ours.
This is journalism, not medical advice. Whether a reading on prednisone needs action, and what action, belongs with the prescriber who knows why you are taking it. How we read a study, and what each tier means, is set out here.