Is Saturated Fat Bad for You? Cutting It Probably Reduced Cardiovascular Events. Deaths Barely Moved.

Three large bodies of evidence exist on saturated fat. They appear to contradict each other. Our reading, set out below and labelled as ours, is that they mostly do not, and why is the most useful thing on this page.
Start with the randomised trials, because they are the only ones on this page where somebody changed what people ate and then waited, two years or more, to count heart attacks, strokes and deaths.
Fifteen trials, 56,675 people, at least two years each
| Outcome | Result | Quality |
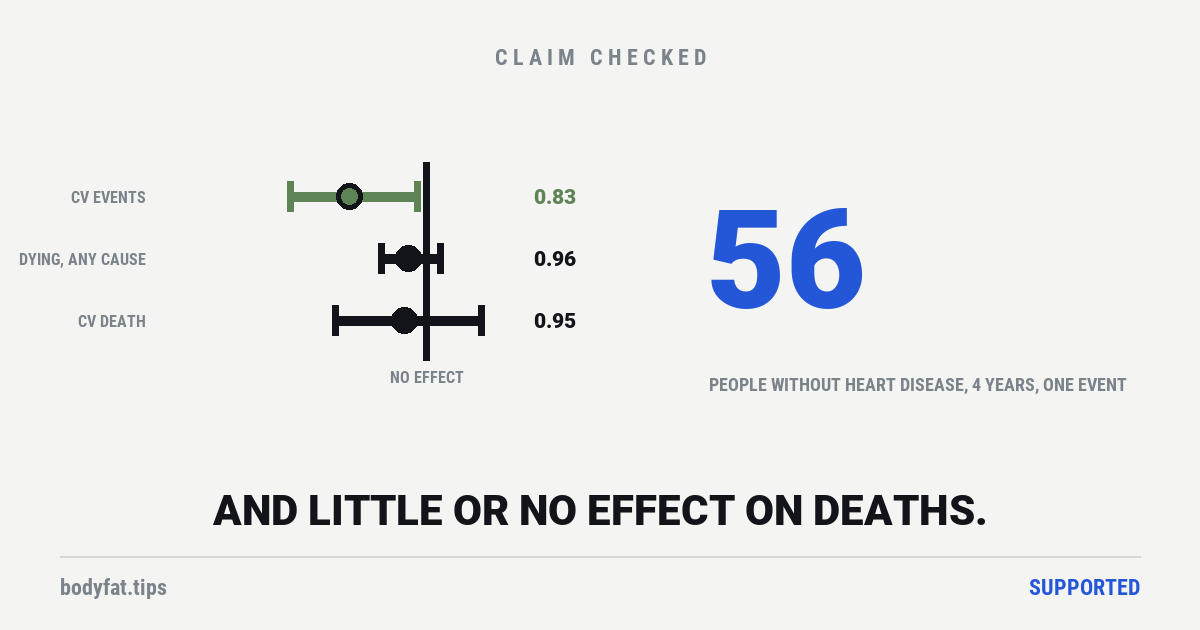
| Cardiovascular events | 17% fewer · 0.83 (0.70–0.98) | Moderate |
| Dying of any cause | Little or no effect · 0.96 (0.90–1.03) | Moderate |
| Dying of cardiovascular disease | Little or no effect · 0.95 (0.80–1.12) | Moderate |
| Non-fatal heart attack | Little or no effect · 0.97 (0.87–1.07) | Low |
| Stroke, total heart attacks | Unclear | Very low |
| Harm from cutting it | None found | — |
Cutting saturated fat reduced cardiovascular events by 17%. [1] The reviewers grade that moderate quality, which on their scale means further research is likely to change how confident anyone can be in it, and may change the figure itself. They marked it down one grade, for two reasons taken together: possible bias in how some of the trials were run, and signs that small trials with less flattering results may be missing. The trials at low risk of bias, taken alone, found a smaller effect, 0.96 with a range of 0.76 to 1.20, which the reviewers read as little or no effect. Their verdict is that cutting saturated fat probably reduces cardiovascular events.
One caution about that headcount. Of the 56,675 people, 48,835 were in a single trial, of a low-fat diet with more fruit, vegetables and grains for postmenopausal American women. It lowered their saturated fat by only 2.9% of calories, and on its own found no clear difference in cardiovascular disease: 0.98, where 1 means no difference, with a range of 0.92 to 1.05 [4]. Seven of the other fourteen trials, published between 1965 and 2006, enrolled only men. The reviewers report that the protective effect held when the big trial was left out, and that the share of events avoided did not differ between men and women or by people’s starting risk [1].
And it made little or no difference to how long people lived. Dying of any cause: a risk ratio of 0.96, where 1 means no difference, with a range of plausible answers from 10% fewer deaths to 3% more. Dying of cardiovascular disease: 0.95, from 20% fewer to 12% more. Both also graded moderate quality. So the trials rule out a large effect on deaths in either direction; they do not rule out a small one. [1]
Anyone quoting one of those two rows without the other is handing you half a result.
What 17% actually buys, in people
The reviewers put a number on it, and it is the most honest sentence in the whole review. In the trials of people who did not already have cardiovascular disease, 56 people needed to reduce their saturated fat intake for about four years for one of them to avoid a cardiovascular event. [1]
In people who already had heart disease, that number was 53. [1]
That is a real benefit and a modest one. It is worth having. It is not the difference between health and catastrophe that forty years of packaging implied.
How much of that reaches you depends on where you start. A cut of the same proportion avoids fewer events in people who were unlikely to have one anyway, and a newer review measured that. Published in 2026, it pooled 17 trials and 66,337 people, searched to July 2025, and worked out the effects separately for people at low and high starting risk. It found non-fatal heart attacks and strokes lower by amounts similar to the 17% (0.86, with a range of 0.70 to 1.06, and 0.83, with a range of 0.58 to 1.19), each range still including no effect, and rated its evidence low to moderate in certainty. Its conclusion: for people at low risk, cutting saturated fat brings little or no benefit over five years; for people at high risk the reductions may be important, particularly in heart attacks when polyunsaturated fat does the replacing [5]. If you already have heart disease or are at high risk, the right amount for you is a question for your doctor; the feeding-trial authors say the same of anyone’s diet [3].
So how much should you eat?
Here is where we are going to disappoint the search box. None of these trials established a daily gram target, and we are not going to invent one.
What the trials did show is a dose-response, where a bigger change brings a bigger effect, but it runs through cholesterol. A meta-regression, which checks whether the trials that changed something more saw bigger results, found that trials that lowered blood cholesterol more cut cardiovascular events more, and that this explained almost all of the disagreement between them. The review’s summary says the same of bigger cuts in saturated fat, but in its own table that link, tested in the eight trials that reported it, was too weak to tell apart from chance. [1]
So is there a line? The reviewers tested the one guidelines use. Trials whose intervention groups got under 10% of their calories from saturated fat, against comparison groups above it, suggested bigger reductions, though the review calls those data hard to interpret and the ranges wide. Whether each further step down helps, it says the trials are “too limited” to tell [1].
The line itself is a guideline, not a trial result. The World Health Organization says no more than 10% of calories from saturated fat [6]. So do the 2025–2030 Dietary Guidelines for Americans, which in the same list name butter and beef tallow as cooking options, after oils such as olive oil [7]. On a US food label, 100% of the Daily Value for saturated fat is 20 grams, set for a 2,000-calorie diet [8]; at 9 calories a gram, that is 9% of calories. Those are rules for whole populations, not thresholds a trial found.
Now the study the other side quotes
Twenty-one prospective studies followed 347,747 people for between five and twenty-three years, during which 11,006 of them developed heart disease or had a stroke. [2]
Comparing the people who ate the most saturated fat with those who ate the least, the pooled figures showed no significant link with heart disease, stroke or cardiovascular disease. The relative risks were 1.07, 0.81 and 1.00, where 1 means no difference, with ranges of 0.96 to 1.19, 0.62 to 1.05 and 0.89 to 1.11. Every range includes 1, so no link at all is still on the table; so, for heart disease, is up to 19% more risk. The authors’ own words were “no significant evidence”. [2]
By 2014 it was being cited beside a newer analysis of 72 studies, and it was the newer one that a March 2014 newspaper column headlined “Butter Is Back” rested on; a June 2014 news-magazine story, “Ending the War on Fat”, cited both. Who paid for it is worth knowing: a national dairy body, which describes itself as founded by dairy farmers and funded through the national dairy checkoff, supported its first and senior authors, alongside US National Institutes of Health grants, and the co-first author, who ran its statistics, held a postdoctoral fellowship from a consumer-goods company’s research arm [2]. In a published reply later in 2010, the senior author disclosed research support from that dairy body, a beef producers’ association and a private family foundation that funds nutrition research, and the authors wrote that the dairy body had no part in designing, preparing or evaluating the paper [11] [12].
It is also the paper whose own authors identified the hole in it, in their concluding sentence: more data are needed on “whether CVD risks are likely to be influenced by the specific nutrients used to replace saturated fat”. [2] They had tried. In six of their studies, and separately in five, the statistics allowed a swap to be read off, saturated fat in place of carbohydrate or in place of polyunsaturated fat, and neither swap showed a link either way; they wrote that they lacked the statistical power to settle it [2].
Within months the same journal printed two letters disputing the paper. One pointed out that 10 of its 21 studies, holding 4,641 of the 11,006 cases, had adjusted for blood cholesterol, which saturated fat raises; adjusting for a step on the way from diet to disease pulls a real link toward zero [9]. The other, co-signed by two of the four authors of the feeding-trial analysis this page cites, argued that about half the studies had measured diet on a single day or by an unvalidated method, which blurs a real link in the same direction [10]. The authors replied that the studies which had not adjusted for cholesterol gave much the same answer: 1.13 for heart disease, with a range of 0.96 to 1.33 [11].
What the second group ate instead
A study that compares people eating more saturated fat with people eating less has not told you what the second group ate instead. If they replaced it with white bread and sugar, you would not expect their hearts to be better off — and the comparison quietly becomes meaningless.
Sixty controlled feeding trials looked directly at that swap. Replacing saturated fat with unsaturated fat improved the cholesterol ratio. Replacing it with carbohydrate did not change the ratio at all. Carbohydrate did lower LDL, the cholesterol most tied to heart disease, but it also lowered HDL, the kind usually counted as protective, and total cholesterol and HDL fell to a similar extent, so the ratio stayed put; triglycerides, another blood fat, rose. The analysis did not separate refined carbohydrate from any other kind [3].
Here is our reading, and it is ours, not any one paper’s finding. The three bodies of evidence contradict each other less once you ask what took saturated fat’s place, though the cohorts that modelled the swap do not all agree. The trials that cut it saw fewer cardiovascular events. The 2010 cohort analysis saw nothing, including in its handful of swap analyses, but a pooled analysis of 11 cohorts and 344,696 people that modelled the swap directly found 13% fewer coronary events when 5% of calories moved from saturated to polyunsaturated fat, and 7% more when they moved to carbohydrate [13]. Two of its American cohorts, the nurses’ and health professionals’ studies, followed for longer, pointed the same way for polyunsaturated fat in 2016, 8% fewer coronary events for each 1% of calories moved to it from saturated fat, and found 6% fewer when the calories moved to whole grains rather than to carbohydrate in general [14]. European cohorts point elsewhere. In 2021 an analysis of 10,529 people who developed coronary heart disease, drawn from 385,747 in nine European countries, found no link either way when polyunsaturated fat, monounsaturated fat or carbohydrate took saturated fat’s place, and its authors note that the finding of fewer events comes from studies in the United States and northern Europe [15]. One of its national arms, a Dutch cohort of 35,597, had reported in 2016 a higher risk of heart disease with every swap it modelled, polyunsaturated fat included; its authors offer leftover confounding, or too little spread in what people ate, as possible explanations [16]. So on the swap, the cohorts’ answer depends on where they were done. The feeding trials suggest a reason: unsaturated fat improved the cholesterol ratio and carbohydrate did not. That is one explanation for the cohort null, not a proven one, and the two letters above offer others: the adjustment for cholesterol, and diets measured on a single day.
Where the sources genuinely disagree, and we are not hiding it
The feeding-trial analysis found the improvement in the cholesterol ratio only when unsaturated fat did the replacing. The review of trials looked for the same pattern in actual cardiovascular events and did not find a significant difference between replacing saturated fat with polyunsaturated fat and replacing it with carbohydrate. [1]
A blood marker and a heart attack are different outcomes and here they did not line up. The authors of the feeding-trial analysis warn against assuming they would, writing that effects on risk markers “should not in themselves be considered to reflect changes in risk”. [3] This is why we grade evidence rather than count studies.
One more detail worth having. Saturated fats are not one substance. In the feeding trials, lauric acid, a major part of coconut and palm kernel fat, raised total cholesterol more than any other fatty acid, but so much of the rise was HDL that it improved the ratio more than any other fatty acid, saturated or unsaturated; stearic acid improved it slightly. The authors add that this does not rule out coconut fat raising the risk of heart disease by other routes, and call the effect of lauric-rich fats on heart disease uncertain. [3] “Saturated fat” on a label is a category, not an ingredient.
What to actually do with this
— Cutting saturated fat probably means fewer cardiovascular events, and how many depends on your risk. In trials of people without cardiovascular disease, 56 cut it for about four years for one to avoid an event [1]; the 2026 review found the gain too small to matter over five years for people at low risk, and possibly important for people at high risk [5].
— What replaces it may matter, but the trials could not show it. Swaps to polyunsaturated fat cut events by about 21% and swaps to carbohydrate by about 16%, a gap the review could not tell apart from chance [1]. The case for polyunsaturated fat rests on the American and pooled cohorts [13] [14] (a large European analysis found no link either way [15]), the cholesterol ratio [3] and one heart-attack subgroup in the 2026 review [5].
— These trials did not show that it makes you live longer. Pooled, they found little or no effect on deaths, in a range that still includes a small benefit. [1]
— The reviewers found no evidence that cutting it did harm. Some ranges were wide, though: cancer deaths came out at 1.00, with a range from 39% fewer to 64% more. [1]
And the reason this argument never ends is that both camps have a real paper to wave. One side has 15 randomised trials showing fewer cardiovascular events. The other has 347,747 people showing no association. Neither is lying. They are answering different questions, and only one of them changed anybody’s diet on purpose.
The rest of this shelf: seed oils, vegetable oil, olive oil, beef tallow, red meat and whether eggs raise your cholesterol. Blood pressure has a clearer answer than any of them.
Our headline said cutting saturated fat prevented heart attacks in 15 trials, and one sentence said the trials showed fewer heart attacks. The review behind that figure found 17% fewer cardiovascular events of all kinds combined, and little or no effect on non-fatal heart attacks on their own (0.97), as the table on this page shows. The headline, that sentence, two other phrases and our search description now say cardiovascular events. We found the sentence on 18 September 2026 while correcting our verdict on seed oils, which cites the same review, and the headline later the same day, during a review of our red-meat verdict. The rating is unchanged: Supported.
This page said cutting saturated fat “did nothing whatsoever” to how long people lived, and its headline ended “Nobody Lived Longer”. The review says less than that. Its words are “little or no effect”: a risk ratio of 0.96 for death from any cause, with a range of plausible answers from 10% fewer deaths to 3% more. That rules out a large effect on deaths and leaves a small one open, and we had written that “those nulls are not a data shortage”. The headline, the table, two paragraphs, our search description and the share image now say little or no effect. The row we labelled “dying of heart disease” carries the review’s figure for death from cardiovascular disease and is now labelled that way. We found this on 30 September 2026 while correcting our three cooking-oil verdicts, which cite the same review.
Our evidence panel said funding was “not stated in the sources read”. All three sources state it. The review of trials was funded by the World Health Organization. The meta-analysis of cohort studies, the paper this page says the other side quotes, was supported by the National Dairy Council alongside NIH grants, and one of its authors held a Unilever fellowship. The analysis of feeding trials was paid for by two Dutch universities and a food-science centre. The panel, the source list and the text now say so. The rating is unchanged: Supported.
An independent editorial review of this page, on 7 October 2026, found that we had misdescribed the cohort study we present as the other side’s case, and had stated the trial evidence more confidently than its own authors do. The 2010 cohort meta-analysis did model what replaced saturated fat, in six and in five of its studies; it found nothing either way and said it lacked the statistical power to settle the question. We had written that it never modelled the swap. Its pooled figures came with ranges that leave room for up to 19% more risk of heart disease, so “not weakly” was wrong, and the page now reports the two letters the journal printed disputing the paper and the authors’ replies. In the trial review, the dose-response ran through blood cholesterol: its link with the size of the saturated-fat cut was too weak to tell from chance, and on whether each further step down helps, the review says the trials are too limited to tell, so “no cliff edge, no magic threshold” and “steadily better” are gone. Its “moderate” grade means further research may change the estimate, not that it would “probably not reverse it”, and its trials at low risk of bias, taken alone, found little or no effect (0.96), which we had not reported. The headline said cutting saturated fat prevented cardiovascular events; it now says probably reduced, the review’s own verdict.
Also corrected: the action list said the replacement “decides most of the effect”, but in the trials, swaps to polyunsaturated fat and to carbohydrate cut events by about 21% and 16%, a gap that could be chance, and the feeding-trial analysis did not separate refined carbohydrate from any other kind. “Cutting it did no harm” now says the reviewers found no evidence of harm. Lauric acid improved the cholesterol ratio more than any other fatty acid, where the page implied stearic acid did better. The 56 is the figure for people without cardiovascular disease, and 48,835 of the 56,675 people were in one trial, whose own result was 0.98. We added a 2026 review of 17 trials and 66,337 people, which finds the benefit too small to matter over five years for people at low risk; the guideline figures, 10% of calories and 20 grams on a US label; the senior author’s published disclosures and the authors’ statement that the dairy body had no part in the cohort paper; and what the feeding-trial analysis’s food research centre said it was. The provenance chain now names the coverage it describes, and funders and companies are described by their role. We rated the page again against the 2026 review: the rating stays Supported, for what the page now says, that in pooled trials cutting saturated fat probably reduced cardiovascular events modestly, with little or no effect on deaths.
Corrected on 17 October 2026. In our reading of how the evidence fits together, we wrote that the three kinds of evidence mostly stop contradicting each other once you ask what replaced saturated fat, and we leaned the cohort half on one 2009 pooled analysis. Later cohorts that modelled the same swap do not all agree. Two of its American cohorts, followed for longer, pointed the same way; a 2021 analysis across nine European countries found no link either way; and a Dutch cohort within it found a higher risk with every swap. The paragraph, the line on polyunsaturated fat and the evidence panel now say so. The rating, which rests on the randomised trials, is unchanged.