Should You Take Calcium Supplements? The Trial That Cut Hip Fractures Was in French Care Homes. At Home, the Best Trials Found No Clear Drop.

“From bone health to cardiovascular concerns, this episode covers everything you need to know about calcium supplementation.” That is the description under a ten-minute video called “Should You Take A Calcium Supplement? The Answer May Surprise You”, posted on 15 March 2024 by a physicians’ explainer channel run by two orthopaedic surgeons, with guest specialists. A one-minute short ten days later asked “Calcium supplements are bad for you?” under the same description. Between them they had 175,253 views when we read their numbers on 10 October 2026 [1].
We read the descriptions, not the videos, so what is said on camera is not what this page checks. The description sets out the weights: calcium’s “crucial role in maintaining strong bones” on one side; “kidney stone formation” and “cardiovascular concerns” on the other; and “natural dietary sources” as the alternative [1]. It is a question a lot of people bring to a search box: “calcium supplements” is searched about 165,000 times a month in the United States, and “should i take calcium supplements” about 1,000 times a month (from a paid keyword database, pulled 10 October 2026) [2].
For adults who live at home, the best trials did not find that calcium pills clearly prevent broken bones. In the largest, 36,282 American women took 1,000 mg of calcium with vitamin D, or a dummy pill, for seven years; hip fractures were not clearly fewer [3]. The pills do raise bone density, by 1 to 2%, once [4]. The trial that made calcium famous for hips was done in French care homes, on women of 84 who were short of both calcium and vitamin D [5].
The worries in the description are real questions with uneven answers. The kidney-stone risk is measured: in that same 36,282-woman trial, 17% more women on the pills reported a stone [6]. The heart-attack risk is genuinely contested, and this page gives both sides their best evidence. And calcium from food goes with fewer kidney stones, not more [7].
Do calcium supplements prevent fractures?
Start with the trial that tested it at the largest scale. The Women’s Health Initiative enrolled 36,282 American women past the menopause, aged 50 to 79, and gave half of them 1,000 mg of calcium a day, as calcium carbonate, with 400 IU of vitamin D; the other half took a dummy pill. They were followed for an average of seven years [3].
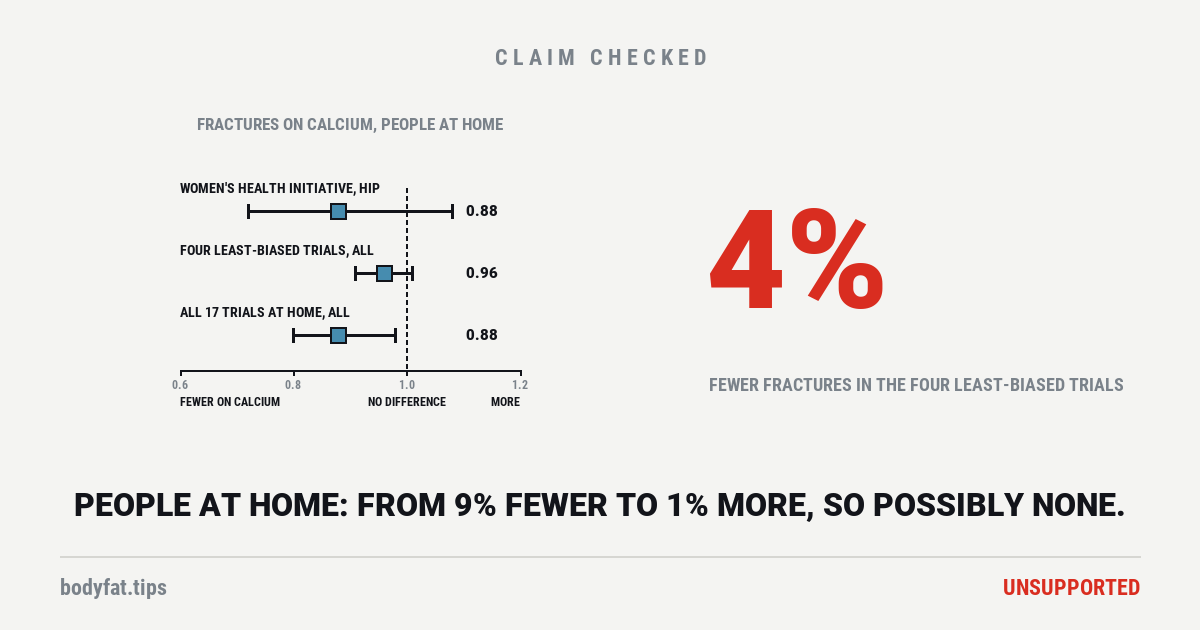
Hip fractures came out at a hazard ratio of 0.88 [3]. A hazard ratio compares how often something happens over time in two groups: 1.00 means no difference, 0.88 means 12% fewer. The confidence interval, the range the true answer probably sits in, ran from 0.72 to 1.08 [3]. Because that range reaches past 1.00, no difference at all is still on the table. For all fractures together the figure was 0.96, from 0.91 to 1.02 [3]. The trial’s own summary: calcium with vitamin D “did not significantly reduce hip fracture, and increased the risk of kidney stones” [3].
Then pool the trials. A 2015 review gathered 26 randomised trials of calcium supplements, with or without vitamin D, in people over 50 [8]. Across 20 trials and 58,573 people, total fractures came out 11% lower: a risk ratio, which reads the same way, of 0.89, from 0.81 to 0.96 [8]. Hip fractures were not clearly fewer: 0.95, from 0.76 to 1.18 [8]. Two things pull that 11% down. The smaller trials leaned towards calcium more than chance would explain, the pattern a review sees when trials that found nothing were less likely to be published [8]. And the four trials the reviewers judged least likely to be biased, 44,505 people, found 4% fewer fractures, with a range from 9% fewer to 1% more [8].
Before printing that 4% we looked for the biggest trial in it. The review’s risk-of-bias appendix names the four, all trials of people living at home, and their sizes add up exactly to 44,505; the biggest is the Women’s Health Initiative: 36,282 of the 44,505 people, about four in five, by our arithmetic [8] [3]. So the least-biased answer is mostly one trial’s answer, and that trial had a weakness the sections below come back to: the women were allowed to take calcium of their own as well. For hip fractures the reviewers left that trial out, rating its hip result at high risk of bias: on calcium with vitamin D, its women who were also taking hormone therapy had fewer hip fractures, and those who were not had no clear difference. The other three trials, about 8,200 people by our arithmetic, found no clear difference at the hip either (1.68, from 0.84 to 3.36) [8]. Pool the 17 trials of people at home in the review’s main analyses, the smaller and more biased ones included, and total fractures came out 12% lower, from 2% to 20% lower, while hip fractures were not clearly lower (1.10, from 0.83 to 1.46) [8].
| Study, who was in it | All fractures | Hip fractures |
|---|---|---|
| Women’s Health Initiative, 2006: 36,282 women aged 50 to 79 at home, calcium with vitamin D, seven years [3] | 0.96 (0.91 to 1.02) [3] | 0.88 (0.72 to 1.08) [3] |
| 2015 pooling, the four least-biased trials: 44,505 people at home, 36,282 of them from the trial above [8] | 0.96 (0.91 to 1.01) [8] | 1.68 (0.84 to 3.36), from the other three trials only, about 8,200 people by our arithmetic: the reviewers rated the trial above at high risk of bias for hips [8] |
| 2017 pooling, people at home over 50: calcium alone, 7 trials for all fractures and 6 for hips [9] | 0.88 (0.75 to 1.03) [9] | 1.53 (0.97 to 2.42) [9] |
| 2017 pooling, people at home over 50: calcium with vitamin D, 8 trials for all fractures, without the Women’s Health Initiative, and 7 for hips, with it counted only for its 7,972 women not also given hormone therapy [9] | 0.90 (0.78 to 1.04) [9] | 1.09 (0.85 to 1.39) [9] |
| 2026 pooling, 60 of its 69 trials only of people at home: calcium alone, 11 trials [10] | 0.91 (0.81 to 1.01) [10] | 1.63 (0.86 to 3.03), 6 trials [10] |
| 2026 pooling: calcium with vitamin D, 15 trials; and without the 1992 care-home trial [10] | 0.91 (0.84 to 0.99); without it 0.96 (0.91 to 1.01) [10] | 0.84 (0.74 to 0.96); without it 0.88 (0.75 to 1.05) [10] |
Two later poolings looked at people living at home. A 2017 review of 33 trials in adults over 50 found that calcium alone did not clearly lower total fractures and leaned the other way at the hip, a lean its authors say did not reach statistical significance and may reflect too few trials to tell [9]. Calcium with vitamin D did not clearly lower hip or total fractures either [9].
The newest, published in May 2026, pooled 69 trials and 153,902 people; in 60 of the trials, 87%, everyone lived at home [10]. Calcium alone: 9% fewer fractures, with a range from 19% fewer to 1% more, in 11 trials and 9,067 people; at the hip, a lean towards more fractures so imprecise that the authors rate its certainty “very low” and call it “biologically implausible” [10]. Calcium with vitamin D: 9% fewer fractures, from 16% to 1% fewer, in 15 trials and 51,126 people, and 16% fewer at the hip [10]. In absolute terms that is about one fracture prevented for every 100 people taking the pills, which the authors judged too small to count as a real benefit [10].
One trial carries much of that combined result, and it is not a trial of people at home. Take out the French care-home trial and the figure for all fractures moves to 4% fewer, from 9% fewer to 1% more, and the hip figure to 12% fewer, from 25% fewer to 5% more [10]. The largest of the 15 trials is again the Women’s Health Initiative [10]. Vitamin D on its own, and who is short of it, has its own verdict.
Why did one trial find 43% fewer hip fractures?
In 1992 a French team gave 3,270 women 1.2 g of calcium and 800 IU of vitamin D a day, or two dummy pills, for 18 months. Among the women who completed the 18 months, hip fractures were 43% lower and all fractures outside the spine 32% lower [5]. It is the trial that put calcium with vitamin D on the map for hips.
Look at who was in it. The women averaged 84 years old [5]. They lived in care, ate about 513 mg of calcium a day, had very little vitamin D in their blood, and 16% of them died within 18 months [8]. The 2026 pooling says many of them “may have had unrecognised osteomalacia”, soft bones from a long shortage of vitamin D, and that the trial’s findings “were not replicated in subsequent trials” [10]. Of the large trials in the 2015 review’s main analyses, it was the only one to show a clear fall in fractures [8]. The review kept one more large trial out of those analyses. In a Danish town, 9,605 people aged 66 and over living at home were offered calcium with vitamin D, a programme to make their homes safer, both or neither, and those offered the pills had 16% fewer fractures from minor falls, counted from hospital records (0.84, from 0.72 to 0.98), while hip fractures were not clearly fewer (0.82, from 0.65 to 1.04) [11]. But the town was split into four blocks, one for each programme, so where people lived decided what they got, and the pills came with a nurse’s review of each person’s medicines that the comparison block did not get [11] [8]. The 2015 reviewers rated it at high risk of bias for those two reasons, the allocation by area and the nurse’s review [8]. About half of those offered the pills took part [11]. Its own authors asked for trials randomised person by person to check it, and the maker of its tablets helped pay for it and supplied them [11]. A 2019 pooling found the benefit of calcium with vitamin D was larger in trials of people over 80 living in institutions [12].
The case for pills at home rests on poolings that include that trial, on chosen parts of the others, or on the Danish programme. A 2016 pooling for the National Osteoporosis Foundation, of eight trials and 30,970 people, found 15% fewer fractures and 30% fewer hip fractures with calcium and vitamin D [13]. For the Women’s Health Initiative it used only the women who kept taking their pills and took no calcium of their own; it later published a correction to its main table, after a letter from the Auckland researchers behind the 2015 review and a colleague, with revised figures of 14% and 39% fewer; and it was paid for by unrestricted grants from three trade groups of the supplement and over-the-counter medicine industry [13]. A 2019 pooling without that funding found 6% fewer fractures and 16% fewer hip fractures with the combination, the care-home trial included [12]. And a 2025 pooling of 23 trials and 70,837 people over 50, of calcium with or without vitamin D, found 7% fewer fractures overall (0.93, from 0.88 to 0.99) and, at the hip, 10% fewer with a range from 27% fewer to 12% more; its author concludes that calcium “can significantly affect the risk of fracture” [14]. Its largest trial is the Women’s Health Initiative, about half its people by our arithmetic, and it includes both French care-home trials; it does not split people at home from people in care, and it found the lopsided pattern among smaller trials that can mean unpublished null ones, which its author says did not change the result [14]. A review of reviews published on 14 October 2026, which drew 69 studies out of 22 earlier meta-analyses, found calcium supplements linked to fewer fractures overall, at the spine and outside the spine, but not at the hip or wrist, and calls the benefit modest; it rates its certainty moderate at best, its summary reports subgroups by type of supplement, sex and age but not by where people lived, and two of its ten authors list as their employer a consumer-health company that sells calcium supplements [15].
The Women’s Health Initiative has a favourable reading of its own, and it should be reported as the trial reported it. When the analysis counted women only while they were still taking at least 80% of their pills, hip fractures were 29% fewer: a hazard ratio of 0.71, from 0.52 to 0.97 [3]. That is weaker evidence than the main result, because women who keep taking pills differ from those who stop, and between 59 and 63% were taking that many at the points the trial measured [3]. And 54% of the women were already taking calcium of their own when the trial began [16]; their average intake was about 1,150 mg a day [3]. Among women who took no calcium of their own during the trial, hip fractures were 30% fewer on the pills (0.70, from 0.51 to 0.98); among those taking 500 mg or more of their own, the estimate leaned the other way (1.22, from 0.83 to 1.79), and the trial’s test of whether those groups truly differed was not statistically significant [3].
What does a 1 to 2% rise in bone density mean?
Bone density is how much mineral is packed into an area of bone, read by a low-dose X-ray scan. It is the number osteoporosis is diagnosed from, and it is the thing calcium pills reliably move. A 2015 review of 51 randomised trials of calcium supplements in people over 50, 12,257 people in all, found bone density 0.7 to 1.8% higher than in the comparison groups at all five sites measured [4]. The rise was there at one year and grew no further after that [4]. No single trial dominates that pooling: the largest measured density in 2,431 people, about a fifth of the total, by our arithmetic [4]. Calcium from food, in 15 trials, did about the same as the pills [4].
What is 1 to 2% worth? The reviewers put it plainly: women after the menopause lose about 1% of bone density a year, so the pills buy back roughly one to two years of normal loss, once, and then the loss carries on [4]. By their arithmetic, from how bone density predicts fractures, that should mean about 5 to 10% fewer fractures [4], which is about what the poolings above found. For scale, the osteoporosis drugs that do cut fractures raise spine density by 6 to 9% over three years [4]. In the 36,282-woman trial, hip density was 1.06% higher on the pills [3].
Why don’t doctors recommend calcium supplements?
Many do, for some people. For most people living at home, the advice changed. The US Preventive Services Task Force, an independent panel that grades preventive care, recommended in 2018 against taking 1,000 mg of calcium or less a day with 400 IU of vitamin D or less to prevent fractures in women past the menopause who live at home; for higher doses, and for men, it called the evidence insufficient [17]. Its December 2024 draft goes further. It recommends against vitamin D, with or without calcium, to prevent fractures in women past the menopause and men aged 60 and over who live at home, concluding “with moderate certainty” that there is “no net benefit” [18]. When we checked on 17 October 2026, the 2018 statement was still the final one and the 2024 text still a draft [17] [18].
The draft carries a fence worth reading. It is about people without osteoporosis, without a past fracture from a minor fall and without a known shortage of vitamin D [18]. And the draft adds that getting enough calcium and vitamin D “is important for bone and overall health”, counting food, drinks and supplements together [18]. The British osteoporosis guideline says “dietary sources of calcium are the preferred option” and that supplements should go to people who do not get enough from their diet and are at risk of fracture [19]. The same guideline judges that the supplements may raise the risk of kidney stones but not of heart disease [19]. Whether they raise heart risk is where the argument is.
Do calcium supplements cause heart attacks?
The worry began in 2008, in a five-year Auckland trial of 1,471 healthy women with an average age of 74 [20]. More heart attacks were reported on calcium than on the dummy pill; after doctors checked the reports, the risk ratio was 2.12, from 1.01 to 4.47 [20]. When hospital records of heart attacks the women had not reported were added, it was 1.49, from 0.86 to 2.57 [20]. The authors called these “upward trends” [20]. A 2023 pooling describes it as the trial that first reported the excess [21].
The same Auckland group then pooled the trials. In 2010, across trials of calcium without vitamin D, heart attacks were 31% more common on calcium in five trials with each patient’s data (1.31, from 1.02 to 1.67), and 27% more common in eleven trials pooled as whole-trial totals [22]. In 2011 they re-analysed the Women’s Health Initiative: among the 16,718 women who took no calcium of their own at the start, cardiovascular events came out 13 to 22% more common on the pills, depending on which events were counted [16]. Pooled with the other trials, heart attacks were 24% more common, from 7% to 45% more [16]. A 2021 pooling of 13 double-blind trials, by a separate team in Korea, put the rise in cardiovascular disease at 15%, from 6% to 25%, in trials whose people were 93% women past the menopause; take out the 2011 subgroup and, by its authors’ own check, the rise in cardiovascular disease became marginal and the rise in coronary heart disease could be chance [23].
The case against the worry is as serious. Heart events were recorded on the side in these trials, often from what patients reported; in the four trials a 2016 review pooled, heart outcomes were secondary in every one [22] [24], and in the 11 trials a 2023 Oxford pooling gathered, none had heart disease as its main outcome [21]. A 2015 pooling of 18 trials in 63,563 older women, counting only heart events verified from records, found heart attacks 8% more common on calcium, from 8% fewer to 26% more, and coronary heart disease 2% more, from 4% fewer to 9% more [25]. A 2023 pooling from Oxford, of 11 placebo-controlled trials, found heart attacks 15% more common on calcium alone and 9% more on calcium with vitamin D, neither clearly so, and said its data ruled out an excess heart or stroke risk above 0.3 to 0.5% a year [21]. Another 2023 pooling, of 12 trials, found no clear link [26]. Two 2026 poolings split the same way. One, a review of 35 earlier meta-analyses by authors at hospitals in Beijing and Chengdu, found cardiovascular disease more common on calcium alone (1.323, from 1.116 to 1.569, in 6,040 people) and not clearly different on calcium with vitamin D (0.999, from 0.942 to 1.060, in 47,312), and rated several of its heart results low in certainty [27]. The other, from Brazil, pooled three trials, four later analyses of the biggest of them and seven observational studies, and found no clear rise in heart attacks, strokes or heart deaths; coronary disease was 8% more common only in the observational studies, and it rated all of its evidence low or very low [28].
And the long view of the biggest trial points both ways. Followed for a median of 22 years, the women who had been assigned calcium and vitamin D had 6% more deaths from cardiovascular disease (1.06, from 1.01 to 1.12) and 7% fewer deaths from cancer (0.93, from 0.87 to 0.99), with a hazard ratio for death from any cause of 1.00 [29]. The authors call it a post hoc analysis, one not planned before the data came in, and say heart outcomes were available for only part of the women [29].
Money sits on both sides. The Auckland analyses were funded by New Zealand’s public research council, and one of their authors declares research support from and consulting for a dairy company [22] [16]. The main pooling on the other side, published in 2016 beside a position statement from the National Osteoporosis Foundation and a preventive-cardiology society, was paid for by an unrestricted grant from the foundation through the consumer-health arm of a drug maker; its authors say they did not know the funder until they had submitted it, and the authors of the Auckland analyses, in a published comment, called it “a review funded by a major producer of calcium supplements” [24]. The 2016 statement concluded that calcium from food or supplements, up to 2,000 to 2,500 mg a day, “should be considered safe from a cardiovascular standpoint” [30].
Our reading, marked as ours: most of the estimates we read sit above 1.00, and where the events were checked against records, the excess came out smaller and less certain [20] [25] [21]. That is a signal worth taking seriously, not a settled risk. It is rated on its own at the foot of this page.
Do calcium supplements cause kidney stones?
This one is measured in a trial. In the Women’s Health Initiative, 449 of 18,176 women on calcium and vitamin D reported a kidney stone over the seven years, against 381 of 18,106 on the dummy pill: 17% more, from 2% to 34% more [6]. In absolute terms that is about 2.5% against 2.1%, roughly four more women with a stone for every 1,000 over seven years, by our arithmetic [6]. Fewer than one in ten of those stones put the woman in hospital [6]. The Task Force’s draft pooled ten trials of vitamin D with or without calcium, 99,036 people, and found 11% more stones [18]. For calcium alone it found two trials with 969 people and an estimate of 1.07, with a range from 0.17 to 6.77: too few stones to tell [18]. The same Task Force’s review of vitamins found kidney stones with vitamin C and calcium, as our multivitamin verdict reports.
Food calcium points the other way. In 45,619 American men followed for four years, those eating the most calcium had 44% fewer stones than those eating the least, and 34% fewer after allowing for other parts of the diet [31]. In 91,731 nurses followed for twelve years, the most calcium from food went with 35% fewer stones, while taking a calcium supplement went with 20% more (1.20, from 1.02 to 1.41) [7].
Why would the same mineral do opposite things? The leading explanation is oxalate, the compound most kidney stones are built from alongside calcium. Calcium eaten with a meal binds oxalate in the gut, so less of it is absorbed and less reaches the urine [7]. In the nurses’ study, 67% of the women taking supplements took them without a meal or with a meal probably low in oxalate [7]. The trial evidence comes from 120 Italian men with recurring calcium oxalate stones and high calcium in their urine, assigned either a normal-calcium diet (about 1,200 mg a day, our conversion) with less salt and animal protein, or the old low-calcium diet (about 400 mg) [32]. Over five years, 12 of 60 had another stone on the first diet and 23 of 60 on the second; oxalate in the urine fell on the first and rose on the second [32]. The first diet changed three things at once, so the trial cannot credit calcium alone. Citrate and stones are covered on our lemon water page.
A word on what the food studies can show. A cohort follows people as they live and records what they eat; nobody is assigned anything. It can show that people who eat more calcium have fewer stones. It cannot rule out that something else about them, or about dairy foods, does the work, and the nurses’ study authors say so themselves [7].
Is calcium from food better than calcium pills?
It depends on what “better” is measured by, and some of it has not been measured. Absorption first. By the US government’s fact sheet, about 30% of the calcium in dairy and fortified foods is absorbed; from spinach, whose oxalate binds it, about 5% against 27% from milk [33]. From supplements, the share absorbed falls as the dose rises: about 36% of a 300 mg dose and 28% of a 1,000 mg dose [33]. So a glass of milk and a modest pill land in the same range, by those figures; a large single pill and a plate of spinach do not.
Bone density: about the same rise from food as from pills, in the trials that compared each with nothing and in the few that compared them directly [4]. Fractures: in the 2015 review’s 44 cohort studies, most found no link between how much calcium people ate and how often they broke a bone [8]. So food calcium is not shown to prevent fractures in people at home either.
One large trial did test food against fractures, in care homes. Sixty Australian homes with 7,195 residents, average age 86, were split by lot, with whole homes rather than single residents assigned; in 30 of them the residents were given extra milk, yoghurt and cheese, adding about 562 mg of calcium and 12 g of protein a day [34]. Over two years they had 33% fewer fractures and 46% fewer hip fractures [34]. The residents had low intakes of both calcium and protein to begin with, the food changed both, and the trial was paid for by dairy-industry bodies [34]. A smaller trial, of milk powder against nothing in 200 Chinese women past the menopause, counted one fracture against three, far too few to tell [8]. A 2025 review by the senior author of the Auckland heart analyses reads the result as a broad improvement in nutrition rather than the work of any single nutrient [35].
Heart: in a US heart study of 5,448 adults, among the 1,567 with no calcium deposits in the heart’s arteries at the start and a second scan about ten years later, those taking calcium supplements were 22% more likely to develop them, after allowing for how much calcium they took in overall, while those with the highest total intake were 27% less likely [36]. That too is a cohort, and it measured a scan, not heart attacks. The calcium in a heart scan is the hardened part of plaque; our plaque verdict explains what it does and does not mean. Kidney stones: food calcium goes with fewer, pills with more, as above [7].
What nobody has done, as far as we could find, is the obvious trial: calcium-rich food against calcium pills, with fractures counted. The trials that compared the two directly measured bone density; the searches behind that sentence are in the sources [4] [37]. The video’s description also mentions “nutrient absorption issues” [1]: one small trial found a calcium supplement taken with a tomato meal cut the lycopene response by 83%, as our lycopene page reports. And the finding that daily cola went with lower hip density in women is on our diet soda page.
What are the signs of a lack of calcium?
Often none. By the US government’s fact sheet, a low calcium intake over years can lead to osteoporosis, thin bones that, in our words, are found with a scan or a fracture rather than felt [33]. Low calcium in the blood is a different thing. It is usually caused by a shortage of vitamin D or magnesium, a problem with the parathyroid glands, serious illness or some medicines, rather than by diet, and its common signs are numbness around the mouth, tingling in the hands and feet, and muscle spasms [33]. Those are reasons to see a clinician, not to buy a supplement.
What is the best form of calcium supplement to take?
The two common forms, by the US government’s fact sheet: calcium carbonate is 40% calcium by weight and is absorbed best with a meal, especially in people with little stomach acid; calcium citrate is 21% calcium and can be taken without food [33]. Either is absorbed better with food, and the share absorbed is highest in doses of 500 mg or less [33]. Gas, bloating and constipation are the common side effects, more so with carbonate [33]. The label lists the elemental calcium, so there is no arithmetic to do [33].
Calcium supplements also interfere with some medicines; the fact sheet names an HIV drug, dolutegravir, the thyroid hormone levothyroxine, lithium and a class of antibiotics [33]. People also search for whether calcium can be taken with diltiazem [2]. If you take any regular medicine, that one included, whether and when to take calcium is a question for your pharmacist or clinician, and this page does not answer it.
Who should take a calcium supplement?
Start with how much calcium the official bodies say adults need, counting food and supplements together. In the US: 1,000 mg a day for adults up to 50 and men up to 70; 1,200 mg for women over 50 and everyone over 70; with upper limits of 2,500 mg a day to age 50 and 2,000 mg after [33]. In the UK, 700 mg for adults [19]. American men average about 1,083 mg a day from food and drink, and women about 842 mg [33].
The fact sheet’s rule is food first: needs “should be met primarily through the diet”, with supplements useful “in cases where it is not possible to meet the needs for specific nutrients through food alone” [33]. It names the groups most likely to fall short: women after the menopause, and people who avoid dairy, through lactose intolerance, a milk allergy or a vegan diet [33]. The British guideline targets supplements, with vitamin D, at people who do not get enough calcium from their diet and are at risk of fracture, such as older adults who are housebound or living in residential or nursing care, and people who absorb food poorly [19].
If you are being treated for osteoporosis, the guidelines treat calcium differently. The British guideline makes it a strong recommendation to offer calcium, vitamin D or both alongside the drugs when dietary calcium is low or vitamin D is likely to be short [19], and a 2017 European consensus calls the supplements “generally appropriate” for people on osteoporosis treatment [38]. The reason is partly history: most of the trials that proved the drugs gave calcium and vitamin D alongside them; in the zoledronate trial everyone was given 1,000 mg or more of calcium a day, and in the alendronate trial 82% were given calcium [19] [38]. Whether the drugs need the calcium is less settled than the habit: the European group calls it “largely undocumented” [38], while the 2015 density review notes that some drug trials cut fractures without it [4]. A 2025 review of 37 drug trials in women treated for osteoporosis found that the calcium dose given alongside was not associated with fractures, bone density or side effects, comparing one trial with another rather than people within a trial [39]. That is a conversation for the prescriber.
Exercise for bone is a separate question that this page does not rate; lifting and impact training are covered on our pages on exercise for osteoporosis, resistance training for older adults, squats and weighted vests.
Who these studies were done on
The biggest trial was women: 36,282 of them past the menopause, aged 50 to 79, averaging 62, 16% of them not white, and already eating or taking about 1,150 mg of calcium a day [3]. Of the 26 fracture trials pooled in 2015, 24 were mostly women [8], and in 2018 the Task Force found the evidence for men too thin to judge [17]; its 2024 draft, still a draft, includes men aged 60 and over in its recommendation against [18]. The trials that found a clear benefit were in women of 84 in French care [5], residents of Australian care homes averaging 86 [34] and, at high risk of bias, the over-66s of one Danish town [11]. The heart signal began in Auckland women averaging 74 [20]. The stone studies were American men aged 40 to 75 [31], nurses aged 34 to 59 at the start [7], and Italian men who already formed stones and had high calcium in their urine [32].
So read yourself against them. If you live at home, eat a varied diet and have no osteoporosis, the big trials were about people like you, and they found little protection. If you live in care, eat little and are short of vitamin D, the trials that found a benefit were about people like you. If you are a man, they were mostly not about you.
If calcium is what bone is made of, why don’t calcium pills prevent fractures?
This section is the desk’s own reasoning, and it is labelled as such. Bone is built from calcium. Calcium pills raise bone density. The best trials in people at home still found no clear fall in fractures. Those three can all be true. Here are three ways to fit them together, each rated.
Answer one: the pill fills a gap most of the people in the trials did not have. The women in the biggest trial were already taking in about 1,150 mg a day [3], and more than half took calcium of their own [16]; among those who took none of their own, hip fractures were 30% fewer on the pills, a subgroup result [3]. The one large randomised trial with a clear benefit in the 2015 review’s main analyses was in women eating about 513 mg and short of vitamin D [8], and the Danish programme that reported a benefit at home was run, its authors write, in a region “known to be deficient in vitamin D, especially during winter periods” [11]. The intakes are measured; that a shortage is the condition for any benefit is a surmise. And one finding cuts against it: in the 2015 density review, trials in people eating under 800 mg a day found a similar rise in bone density to trials in people eating more [4].
Answer two: bone density is a small lever on fractures. One to two percent, once [4], against the 6 to 9% from drugs that do prevent fractures [4]. The 2015 reviewers worked out that a rise that size should mean 5 to 10% fewer fractures, which is about what the poolings find [4]. That is arithmetic from the reviewers, not a measurement of fractures.
Answer three: people stop taking them. In the biggest trial between 59 and 63% were taking at least 80% of their pills [3]; across trials, the 2015 review puts persistence at about 40 to 60% [8], and the common side effects are gas, bloating and constipation [33]. That many stop is measured. That stopping explains the result is a hypothesis, and the trial’s own counting of adherent women cannot settle it, because the people who keep taking pills differ from the people who do not.
Put the three together and here is what we think is true, stated plainly so you can disagree with it: calcium is a building material, not a repair kit; a pill can fill a shortage, and most of the people in the big trials did not have one.
What we could not find, and would like to: a trial in adults living at home, large and long enough to count both fractures and verified heart attacks, in which the people were not allowed calcium supplements of their own. In 2017 a European expert group wrote that a large trial of calcium supplements “powered to detect validated fractures and cardiovascular events”, big enough to count confirmed fractures and heart events, is needed to settle the question, and suggested one built like the Women’s Health Initiative but with no calcium supplements of the participants’ own allowed [38]; our searches found no trial of that kind since [37]. And a trial of calcium-rich food against calcium pills with fractures counted [37]. If you know of either, the corrections line on this site is open.
Where “calcium for strong bones” came from
The research was real. In 1992 a French trial in women of 84 in care found 43% fewer hip fractures with calcium and vitamin D [5]. The framing is written into US food law. A federal rule, in its current wording since 2008, lets a food or supplement label say “Adequate calcium throughout life, as part of a well-balanced diet, may reduce the risk of osteoporosis” [40]. That sentence is about a lifetime of enough calcium as part of a diet. On a supplement bottle it reads as something else.
Then it spread, and it is still spreading. Ask Google about calcium supplements and its AI answer opens “Calcium supplements help build and maintain strong bones and prevent osteoporosis”, citing a US government medical encyclopedia and a video [2]. The channel’s ten-minute video is among the first 20 results for the same search, weighing the bone benefit against the heart and the kidneys [2] [1].
And it sells. For “calcium supplements”, Google’s top ten includes an online marketplace’s listing of calcium supplements for women and a supplement maker’s “bone health” page, with a supplement-testing subscription site’s “top picks” further down [2].
None of this is aimed at anyone who takes calcium. Plenty of people need more of it, and the guidelines say who. It is the promise that a pill protects the bones of anyone who swallows it that the trials did not keep.
What this is rated, and what the rating covers
Unsupported, of the tested kind — for the claim that calcium supplements, with or without vitamin D, protect the bones of adults who live at home from breaking.
What was tested: calcium, alone or with vitamin D, against a dummy pill or nothing, in randomised trials of tens of thousands of adults over 50 living at home, most of them women, for up to seven years [3] [8] [9] [10]. What it found: no clear fall in hip fractures, in the least-biased trials or in any pooling limited to people at home, and at most a small fall in fractures overall: 4% in the least-biased trials, with a range that includes no difference at all [8] [9]. The 2026 pooling, most of whose trials were only of people at home, judged the fall from calcium with vitamin D too small to count as a benefit, with high certainty [10], and the Task Force’s draft concluded with moderate certainty that there is no net benefit [18]. Unsupported here does not mean proven useless: the trials cannot rule out a benefit of a few percent across all fractures. It means the protection the claim promises did not show up when it was tested in the people it is sold to. The favourable results are on this page: a care-home trial; a Danish town’s programme rated at high risk of bias; the 2015 review’s pooling of its 17 trials of people at home, 12% fewer fractures, which its least-biased trials did not bear out; an industry-funded pooling of chosen trial data; a 2025 pooling whose author reads its 7% as a real benefit; a 2026 review of reviews that calls the benefit modest; and one trial’s count of women who kept taking their pills [5] [11] [8] [13] [14] [15] [3]. Rated on its own, the narrower claim that calcium pills cut fractures overall by a few percent in adults at home would be Preliminary: the 17 trials of people at home in the 2015 review’s main analyses, pooled together, found 12% fewer; its four least-biased trials found 4% fewer, with a range that includes no difference; and the size of the fall follows the trials’ risk of bias [8].
Each of the other claims on this page, rated alone, in words. That calcium supplements raise bone density: Established, by 1 to 2%, once, in 51 trials [4].
That calcium with vitamin D prevents fractures in frail older people in care who are short of both: Preliminary, on a short and conflicting record: one large French trial from 1992 that, by the 2026 pooling’s account, later trials did not replicate; two smaller care-home trials in the 2015 review that did not show a clear fall on their own; and a care-home food trial that changed protein too [5] [10] [8] [34].
That calcium supplements raise the risk of heart attack: Preliminary. The trials were built for bones; the poolings that found 15 to 32% more heart attacks or cardiovascular disease, the largest rise on calcium alone, are matched by poolings of checked events that found smaller rises that could be chance, and by poolings of calcium with vitamin D that found no clear rise; and we found no trial against a dummy pill built to settle it [22] [27] [25] [21] [28] [37].
That calcium supplements taken with vitamin D raise the risk of kidney stones: Supported, on one large trial; the Task Force draft’s judgement that the harm is real and small, from a pooling of ten trials of vitamin D with or without calcium (of the eleven trials it found that reported stones, seven gave vitamin D alone); and a large cohort of women [6] [18] [7]. For calcium alone the trials are too few to say.
That calcium from food is better than pills: for kidney stones, Supported, on cohorts, a mechanism and a diet trial in men who form stones and have high calcium in their urine [31] [7] [32]; for bone density, the two did about the same [4]; for fractures and the heart, Preliminary, with cohort evidence and one care-home trial that changed protein too [36] [34].
What is not rated here: calcium alongside osteoporosis drugs, which the guidelines treat as part of the treatment; calcium for blood pressure, weight or cancer; vitamin D on its own, which has its own page; exercise for bone; stress fractures in young adults in hard physical training, a different break in people the fracture trials on this page did not study; and the frame above, which is this desk’s reasoning from the evidence rather than a result the evidence delivered. It is marked as ours so that you can weigh it as ours.
This is journalism, not medical advice. Whether to take a calcium supplement, especially alongside osteoporosis treatment, or if you have had kidney stones or heart disease, belongs with a clinician who knows your diet, your medicines and your bones. How we read a study, and what each tier means, is set out here.
- Do You Need a B12 Supplement? If You Eat No Animal Foods, Yes. Energy at Normal Levels: Not Shown.
established - Glycine Benefits: Three Sleep Trials, 37 People, the Maker’s Staff on Every Paper. GlyNAC: a Trial of 24, and a Bigger One That Missed.
preliminary - Turmeric Benefits: Capsules May Take the Edge Off Knee Arthritis Pain. The Biggest Numbers Came From the Smallest Trials.
preliminary