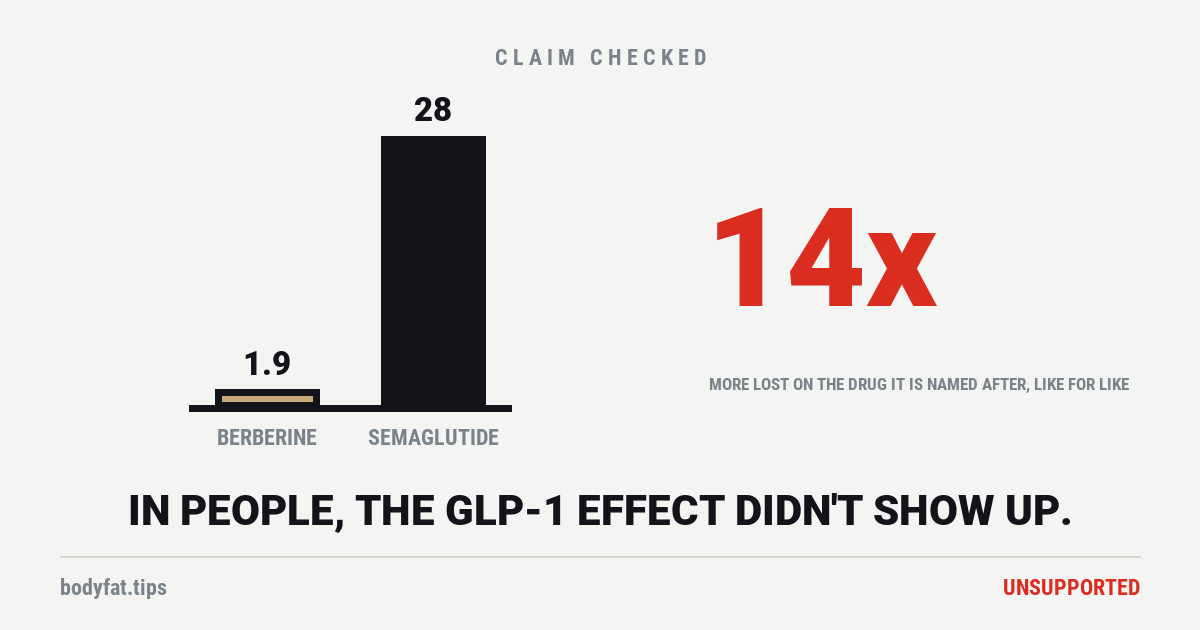
Berberine Benefits: “Nature’s Ozempic” Is 1.9 Pounds. Semaglutide Is 28.

One point nine pounds.
That is how much more weight people lost on berberine than without it, when fifteen randomised trials were pooled together last year. [1] Not per week. Total.
Semaglutide — the drug in Ozempic, at the weight-loss dose sold as Wegovy — beat a dummy injection by 28 pounds in the trial that made it famous. [2]
So let us put those next to each other, because nobody selling you the first one ever does.
“Nature’s Ozempic” against the drug in Ozempic
Both bars come from the strongest evidence that exists for each compound. The berberine figure is a mean difference of −1.9 lb (−0.88 kg) from the 15 randomised controlled trials that reported weight, out of 23 in a review published in the International Journal of Obesity in 2026. Five of the 15 tested barberry, one of the plants berberine comes from, as a dried fruit or an extract, and one tested a drug that pairs berberine with a bile acid; the trials the review classed as berberine give the same 1.9 lb on their own. The trials were mostly in adults who already had a health problem: type 2 diabetes or high blood fats (five trials), fatty liver (three), polycystic ovary syndrome (two) and others, including one in people with schizophrenia-spectrum disorders. [1] Those two, a 2012 trial in China and a 2023 trial in Pakistan, are among four trials of berberine in that condition that a 2026 integrity reappraisal, a review that checks trials for the marks of trustworthy research, rated at high risk of compromised integrity [35]. Does the figure lean on them? No: our own re-run of the review’s pooling without them, from the per-trial numbers in its supplementary chart and by the method that reproduces its published result, gives the same 1.9 lb (0.87 kg), with a slightly wider range of plausible answers, about 0.6 to 3.2 lb (0.28 to 1.46 kg). That is our arithmetic, not a figure the review reports. [1] The semaglutide figure is STEP 1 — 1,961 adults without diabetes, 68 weeks, double-blind, placebo-controlled, in the New England Journal of Medicine. The 1,306 given semaglutide 2.4 mg lost 33.7 lb (15.3 kg) and the 655 given a placebo lost 5.7 lb (2.6 kg): a difference of 28.0 lb (12.7 kg). [2]
A mean difference is just the average gap between the treated group and the control group, in the units of the thing being measured. Here that is pounds on a scale.
About fourteen times, measured the same way: both bars are the gap between people given the treatment and people who were not. Is it unfair to berberine that its trials mostly lasted about three months and semaglutide’s ran 68 weeks? A trial that gave berberine for six months to 337 adults with obesity and fatty liver, double-blind — neither the patients nor the researchers knew who was getting what — ended with the berberine group no lighter than the placebo group. [15]
In STEP 1, half the people on semaglutide lost 15% or more of their body weight. [2] Nothing in the trials behind the berberine figure comes close: the biggest gap any one of them found between berberine and its comparison group was 5.3 lb (2.4 kg). [1]
The name is borrowed from a mechanism that has not shown up in people
“Natural GLP-1” is the whole pitch. GLP-1 is a gut hormone released after you eat; it tells your pancreas to release insulin and tells your brain you have had enough. Semaglutide is a manufactured molecule that mimics it and stays in your system for days.
So does berberine raise GLP-1?
In rats, yes. In 2009, researchers gave streptozotocin-diabetic rats berberine for five weeks and measured more GLP-1 in plasma and intestine, more proglucagon messenger RNA, and more of the intestinal L cells that make the hormone. [12] A follow-up in 2010 repeated it in normal rats and in NCI-H716, a cell line grown in a dish. [13]
That is where the idea comes from. It is genuine science and it is interesting.
In people, it has not shown up. In a double-blind trial published in 2021, 300 adults in China with newly raised blood sugar were split four ways for 16 weeks: berberine (500 mg twice a day), a probiotic (a bacteria supplement), both, or a placebo. GLP-1 in their blood was measured at the start and at the end. Berberine moved it no more than the placebo did; in the authors’ words, the changes “were similar among the groups”. [16] The authors add a caution worth keeping: GLP-1 does its work in the vein that carries blood from the gut to the liver, and is broken down within about 90 seconds, so a blood test could miss an effect there. Their conclusion is that evidence that berberine regulates GLP-1 in people “is still absent”. [16] A smaller trial in 16 healthy men, registered to measure the same hormone after a single 1 g dose, finished in April 2023 and has posted no results; we found no paper from it. [17]
A 2025 review in European Journal of Medical Research subtitled “from pharmacological mechanisms to clinical evidence” tabulates berberine’s obesity mechanisms in detail. [14] Every GLP-1 entry in it is an animal: obese mice, overweight mice with induced polycystic ovary syndrome. Not one is a person, and the 2021 trial is not among its references.
Read that back against the marketing. The category is named after a hormone effect demonstrated in rodents and cell culture, not found when it was measured in people, and sold to humans as an alternative to a drug whose own effect on humans was measured in 1,961 of them over 68 weeks.
This does not mean berberine does nothing: in that trial it lowered fasting blood sugar more than the placebo did. [16] It means the specific story being told about how it works — the story the nickname depends on — was looked for in the species buying it, and did not turn up. That makes this verdict stronger than when we first wrote it. The mechanism is no longer untested in people. It was tested, and it did not show up.
The awkward part: the berberine studies disagree with each other
Here is where most coverage picks the number it likes and moves on. We are going to show you five of them.
| Analysis | Trials with weight data | Weight change |
| Xiong 2020 | 5 of 10 | −0.2 lb — not significant |
| Amini 2020 | 9 of 12* | −0.2 lb — not significant |
| Asbaghi 2020 | 5 of 12 | −4.6 lb |
| Zamani 2022 | 21 of 49 | −1.9 lb |
| Elahi Vahed 2026 | 15 of 23 | −1.9 lb |
Five pooled analyses of substantially the same literature. [1][3][4][18][19] One of them — Xiong 2020, pooling the five of its ten trials that reported weight — found no significant effect on body weight at all: −0.11 kg, with a confidence interval running from −0.99 to +0.76 and a p-value of 0.79. [3] A confidence interval is the range the true answer probably sits inside. When it crosses zero the way that one does, “does nothing” is still very much on the table.
Another from the same year, which also counted trials of barberry, found the same −0.2 lb (−0.11 kg), not significant either. [18] A third, also from 2020, found −4.6 lb (−2.07 kg). [4] A 2022 analysis found −1.9 lb (−0.84 kg) [19], and the newest lands at −1.9 lb (−0.88 kg). [1]
When five teams pool overlapping sets of the same trials and get answers ranging from nothing to 4.6 lb, that is not a signal being refined. That is a small effect being pushed around by which studies you let in.
Why the effect is so small: almost none of it gets into you
Berberine has a pharmacokinetic problem that is not a matter of opinion. Its oral bioavailability — the fraction of a swallowed dose that actually reaches the bloodstream — is less than 1% [7], a figure that comes from studies in rodents. [14]
If people absorb it the same way, a gram swallowed puts under ten milligrams where it could do anything systemic. The amount measured in people’s blood after a 500 mg dose is counted in billionths of a gram per millilitre [14], and a 2022 review of what the body does with berberine puts the share that passes out in the feces at 11% to 23%. [7] The same review names its poor solubility and absorption as what restricts its clinical use [7], and that is a plausible mechanical reason a compound with genuinely interesting activity in a petri dish keeps producing modest results in people.
So what does it actually do?
Something. Mostly to blood sugar and blood lipids, and mostly in people who already have a metabolic problem.
The claim that berberine “works like metformin” rests on small trials like a 2008 study in Metabolism that its own authors call a pilot study. [6] Thirty-six adults with newly diagnosed type 2 diabetes were randomised to berberine or metformin for three months. The result, in the authors’ words: “The hypoglycemic effect of berberine was similar to that of metformin.” HbA1c — a rough three-month average of blood sugar — fell from 9.5% to 7.5%.
That is a real result and it is worth taking seriously. It is also thirty-six people, for three months, in one trial, in 2008. In the same paper, 20 of the 58 people who took berberine across its two studies (34.5%) had gastrointestinal side effects.
The finding that should decide this for you
In 2025 a team did something more useful than another meta-analysis: they assessed the quality of fifty-four systematic reviews of berberine, using the standard tools for the job. [5]
AMSTAR-2 rates how well a review was actually conducted. Of the 54, one came out high quality. Eight were low. Forty-five were rated very low. Separately, GRADE — which rates how much confidence the evidence itself deserves — rated 312 of the 452 outcome results it graded as very low, its lowest band, and another 110 as low.
And then the part that ought to be printed on the bottle. The review sorted outcomes by disease. Gastrointestinal conditions: 95% of outcomes improved. Type 2 diabetes: 93%. Dyslipidaemia: 100%. Metabolic syndrome: 91%.
Obesity: 57%. Four outcomes out of seven. The worst of all nine categories.
Berberine improved the smallest share of outcomes in precisely the area it is marketed for hardest, although its body-mass-index result was one of only eight in the whole overview rated high certainty. The reviewers also noted that the obesity reviews heavily overlap — they are re-pooling the same handful of trials, which makes a stack of papers look like a stack of evidence.
Berberine versus metformin, since that is the other comparison
Metformin is a prescription drug with sixty years of use, a known dose response, and outcome data running to cardiovascular events and death. Berberine has a handful of small, short trials against it. A 2012 review found seven that compared berberine with metformin or other diabetes pills — 15 to 51 people each, 8 to 13 weeks, all in China — and found no significant difference in blood sugar, while judging the trials’ methods generally low in quality. [20] The 2008 pilot is one of the seven. [6]
“Similar in a pilot” and “equivalent” are not the same statement. A trial of 36 people is large enough to detect a big difference and far too small to rule out a meaningful one. No regulator anywhere would licence a diabetes drug on it, and the authors themselves called it a pilot study in the abstract.
There is also a practical problem that has nothing to do with efficacy. Metformin arrives at a known dose of a known compound, and berberine arrives at whatever the manufacturer put in the capsule. The 2026 meta-analysis said this plainly when listing what future trials need to fix: purity, potency and gram amounts are not being reported. [1] If the trials cannot tell you what they tested, a bottle cannot tell you what you are taking.
Dose, timing, and how long before anything happens
These are the questions people actually type, so here is what the evidence supports and where it runs out.
Dose. The trials cluster around 500 mg taken two or three times a day — the 2008 study used 0.5 g three times daily. [6] That is the tested range. It is not a recommendation. Two bottles both saying 500 mg are not necessarily delivering the same thing, because of the purity problem above, and, as the safety section below explains, Europe’s food-safety authority has not found any intake it can call safe.
Timing. Split doses with meals is what the trials did, and there is a mechanical reason it makes sense rather than a mystical one: berberine is poorly absorbed and hard on the stomach. In the 2008 study, 20 of the 58 people who took it had gastrointestinal side effects, short-lived and in most cases confined to the first four weeks; most of those whose dose had to be cut were also taking metformin or acarbose, and nobody taking berberine on its own had severe ones. [6] Spreading it out and taking it with food is about tolerating it. The popular claim that a particular hour of day unlocks the effect is not something these trials tested.
How long. Most of the fifteen trials pooled for weight ran about three months (the range was 7 to 20 weeks), and the pooled effect at the end of them is the 1.9 lb above. [1] If you are asking how long until it works, the honest answer is that the studies measuring the thing you are hoping for ran about three months and found about two pounds. The six-month trial found no difference: people on berberine lost 4.0 lb (1.8 kg), people on the placebo 4.2 lb (1.9 kg). [15]
Does berberine lower cholesterol?
Yes, a little. This is the claim about berberine that its trials back most consistently, and it is worth seeing exactly how little, because the numbers that travel online are bigger than the ones from trials of berberine on its own.
Three numbers on a cholesterol test matter here. LDL is the cholesterol carried in the particles that build up in artery walls, the kind called bad. HDL is the kind called good. Triglycerides are the main fat in the blood. A US lab report gives all three in milligrams per decilitre, mg/dL, and so do we below, with the papers’ own millimoles per litre in brackets where they used them; those conversions are ours.
Where the cholesterol claim comes from
In 2004 a paper in Nature Medicine introduced berberine as “a new cholesterol-lowering drug”. Its headline result: in 32 people with high cholesterol who took it for three months, total cholesterol fell 29%, triglycerides 35% and LDL 25% [28]. Those are before-and-after changes in the people who took berberine, not gaps against a comparison group. The comparison is in the paper’s supplementary tables. Across everyone in the study, 63 people on berberine and 28 on a placebo, a dummy pill, average LDL went from about 135 to 108 mg/dL (3.5 to 2.8 mmol/L) on berberine and from about 143 to 139 mg/dL (3.7 to 3.6) on the placebo [28]. The same paper traced a mechanism in hamsters and in human liver-cancer cells grown in a dish: berberine raised the number of LDL receptors, the docking points the liver uses to pull LDL out of the blood [28]. The main text is behind the journal’s paywall; we read the abstract and those tables.
How much does berberine lower LDL?
The best evidence comes from trials that gave berberine on its own against a placebo, and there are now enough of them to pool, which means combining their results. A 2023 review pooled 18 such trials, 1,788 people, lasting 4 to 24 weeks, 15 of them run in mainland China and Hong Kong. Against the placebo, LDL fell about 18 mg/dL (0.46 mmol/L) more on berberine, total cholesterol about 19 mg/dL (0.48) more and triglycerides about 30 mg/dL (0.34) more. HDL rose about 2 mg/dL (0.06), with a range of plausible answers that starts at no change at all, a figure we come back to below [24]. Its authors call the falls in LDL and triglycerides “small reductions”. In the earlier version of the review that we could read in full, the trials were mostly in people with type 2 diabetes, polycystic ovary syndrome (a hormonal condition in women), raised cholesterol or schizophrenia, and none enrolled people with a history of coronary heart disease or stroke [24].
Does a stricter pooling agree? A 2025 pooling that took only purified berberine against a placebo landed in the same place: LDL about 19 mg/dL (0.495 mmol/L) lower than on the placebo across 8 trials and 750 people, total cholesterol about 17 mg/dL (0.451) lower, triglycerides about 33 mg/dL (0.367) lower, and HDL not significantly changed [25]. The eight trials’ LDL results also differed from each other far more than chance would explain: the pooling’s measure of that, the share of the spread between the trials’ results that is more than chance would produce, was 89% [25]. It came with its own fence. Across its trials, the LDL gap shrank the longer a trial ran, and in the one trial that lasted 16 weeks, its longest to measure LDL, the LDL gap was not statistically significant [25].
Before trusting a pooled figure, find the biggest trial inside it. In the 2023 pooling, as far as the reference list of its earlier version shows, that is a 2020 trial of 409 adults in China newly diagnosed with type 2 diabetes; 98 were given berberine alone, 1.2 grams a day, 103 a placebo and the rest a probiotic, with or without berberine, for 12 weeks, after a week of an antibiotic that everyone took. LDL fell about 17 mg/dL (0.45 mmol/L) on berberine and about 5 mg/dL (0.14) on the placebo [26]. In the 2025 pooling the biggest, by its own count, is the 16-week trial on this page that measured GLP-1 [25]. By that trial’s own figures, total cholesterol fell about 12 mg/dL (0.31 mmol/L) more on berberine alone than on the placebo, but LDL did not fall significantly more [16]; the 2025 pooling, recalculating the same trial, put the total-cholesterol gap at about 6 mg/dL (0.150 mmol/L), too small to tell apart from chance [25].
The newest big trial is on this page already, for weight: 337 adults in China with obesity and fatty liver but no diabetes, given 1 gram a day or a placebo for six months. LDL fell 7.7 mg/dL more on berberine, from a starting average of about 115, with a range of plausible answers from 1.9 to 13.1 mg/dL. Its other blood-fat results, total cholesterol, triglycerides and HDL among them, were not significantly different from the placebo’s. The authors add that these were secondary results, not tested with the extra strictness that checking many outcomes at once calls for [15].
Two more fences. In the 2022 version of the 2023 review, with 16 trials, its authors found signs of publication bias in total cholesterol and triglycerides, the pattern left when small trials that disappoint go unpublished. Allowing for it cut the total cholesterol estimate from about 18 to about 9 mg/dL (0.47 to 0.23 mmol/L) and the triglyceride estimate from about 28 to about 18 mg/dL (0.32 to 0.20). They found less sign of it for LDL [24]. And the graders disagree on how far to trust all of this. Those authors rated their LDL evidence moderate in certainty; the 2025 overview of 54 reviews above graded the cholesterol results it looked at low or very low [24][5].
Who were these people? Mostly Chinese adults with a metabolic problem, and sex may matter. In 2026 a team in Hong Kong gave 100 women with raised cholesterol berberine or a placebo for 12 weeks and set the results beside their earlier trial of 84 men on the same dose: LDL fell more than on the placebo in the women, but not significantly more in the men [27].
What about HDL, the good kind? The 2023 pooling reported a split by sex: HDL up about 4 mg/dL (0.11 mmol/L) in women and down about 3 mg/dL (0.07) in men, a fall too small to tell apart from chance [24]. Look at where those figures come from, though. In the earlier version of that review, which we could read in full, the women’s figure came from two trials, both in women with polycystic ovary syndrome, and the men’s from the Hong Kong team’s trial in 84 men; the published version gives the same figures. In the same earlier version, the ten trials that enrolled both men and women put HDL up about 2 mg/dL (0.06 mmol/L), with a range of plausible answers that starts just below zero, and they did not agree: three found clear rises of their own, the largest about 10 mg/dL (0.26 mmol/L), one, the 16-week trial, found a clear fall, and in the other six the gap was too small to tell apart from chance [24]. In October 2026 an integrity reappraisal, a review that checks whether trials show the marks of trustworthy research, such as registration before they start, looked at berberine trials in that condition and rated both of those two at high risk of compromised integrity: by its summary table neither was registered, though the 2012 trial’s paper prints a registration number without naming a registry, and it flagged an implausible timeline in one and an implausible sample size and possible duplicated data in the other [35]. And in the Hong Kong trial in women recruited from a university’s staff and their families, not for that condition, HDL came out a little lower than on the placebo, a gap too small to tell apart from chance, while apolipoprotein A1, the main protein in HDL particles, fell [27].
Where the bigger numbers online come from
Ask Google the question and its AI answer, in the results we saved on 20 October 2026, says berberine cuts LDL by “roughly 15% to 25% (or 20 to 50 mg/dL)”. The 20-to-50 range matches the wording of a 2017 review that answer cites, and the review’s range rests mostly on pills that were not berberine alone. Of the eight trials it cites for that range, two gave berberine alone against a placebo (one of them the 2012 trial in China that the integrity reappraisal rated at high risk [35]), one gave berberine alone with no placebo to compare against, and five tested combination pills, all five pairing berberine with red yeast rice, whose main active ingredient, the review notes, “is currently marketed as lovastatin”, a statin [29]. The review says it plainly: “most trials provided berberine in formulations that included other herbal products” [29].
A 2024 pooling that kept the two apart shows why that matters. It took in 41 trials of products containing berberine, and across the 33 comparisons among them that reported LDL, LDL fell about 15 mg/dL more than in the comparison groups. For the 11 comparisons of berberine alone the figure was about 9 mg/dL, with a range of plausible answers from a 20 mg/dL fall to a 2 mg/dL rise, which leaves no change on the table; four of those 11 set berberine against something other than a placebo alone: another treatment in two, no treatment in one, and a placebo and another treatment together in one [30]. Two of those 11, and so of the 33, are trials the integrity reappraisal rated at high risk: the 2012 trial in China and, by its year, size, dose and comparison treatments, the 2022 trial in India, both in women with polycystic ovary syndrome; the same two are among its 11 for HDL [30][35]. They pull in opposite directions. In the trial from India, LDL fell on berberine too, but by less than on the two treatments it was set against, metformin, a diabetes drug, and myo-inositol, another treatment used for the condition, so the pooling counts it as about 31 mg/dL in their favour; the 2012 trial counts about 13 mg/dL in berberine’s favour [30]. Leave both out and our own re-run of the pooling’s figures, by the method that reproduces its published result, puts berberine alone at about 13 mg/dL, with a range of plausible answers from about 5 to 21 mg/dL that no longer includes no change; the shift comes from the trial from India. That is our arithmetic, not a figure the review reports, and it makes berberine look a little better on LDL, not worse. We read that pooling as its abstract and the forest plots in its supplementary file; the article itself would not open for us.
Is berberine as good as a statin?
A statin is the standard cholesterol tablet. Has berberine been tried against one? Yes. A 2019 review by a team at a university of Chinese medicine, searching Chinese and English databases, pooled 11 trials, 1,386 patients, some of them comparing berberine with simvastatin, a statin. On LDL and HDL it found no statistically significant gap between the two, with berberine ahead on triglycerides, and its authors called the quality and quantity of the trials “dissatisfactory” [31]. A gap too small for trials like those to detect is not the same as no gap. We read that review as its abstract.
Set side by side through a placebo, the picture changes. A 2024 analysis from a US school of pharmacy re-pooled placebo-controlled trials of single ingredients: seven berberine trials came to an LDL fall of about 15 mg/dL more than on placebo, against about 41 mg/dL for the statin pravastatin at 10 mg and about 58 mg/dL at 40 mg [32]. At 40 mg that is nearly four times as much (our arithmetic). Two of its authors also wrote the 2024 pooling above, and by its methods its berberine figure re-runs that pooling’s trials, keeping only those of a single ingredient against a placebo: its seven berberine trials are the seven placebo-controlled ones among that pooling’s 11 comparisons of berberine alone, by the pooling’s supplementary figures [32][30]. These are different trials in different people, 8 to 12 weeks long for berberine and 12 weeks to three years for pravastatin, so the comparison is rough. Nor is it clean: three of the seven berberine trials, when we looked them up, tested barberry, a shrub whose fruit contains berberine among much else, as a dried fruit in one and as extracts in the other two, not purified berberine [32]. Our verdict on foods that lower cholesterol makes the same kind of comparison for a diet said to match a statin.
And the blood test is not why statins are prescribed. That 2024 analysis cites two long trials of pravastatin against a placebo [32]. In the first, 4,159 people who had had a heart attack took it or a placebo for five years: heart attacks and deaths from heart disease, counted together, were 24% less common on the drug, though deaths from any cause were not significantly fewer [37]. In the second, 9,014 people who had had a heart attack or a hospital stay for unstable angina, chest pain from narrowed heart arteries that comes on suddenly or at rest, took it or a placebo for six years on average: that same count was again 24% lower, heart attacks alone were 29% lower, and deaths from any cause 22% lower [38]. None of the berberine cholesterol trials in these poolings counted heart attacks, strokes or deaths; they measured blood tests [24][25][32].
Two trials registered on ClinicalTrials.gov are set up to count them. One has enrolled 2,024 adults in China with prediabetes, blood sugar raised but below the diabetes line, who are also overweight and have heart disease or at least two other heart risks, to take berberine or a placebo for a year. Its main question is blood sugar; heart attacks, strokes and cardiovascular deaths are among its secondary outcomes, counted over up to four years. Its registry entry gives December 2026 for completion and shows no results yet [34]. The other was designed around heart events: 5,200 adults with metabolic syndrome, three or more of a large waist, high blood sugar, high blood pressure, high triglycerides and low HDL, to take berberine or a placebo for three years, with cardiac death, heart attack, stroke and new diabetes as its main outcome. It was registered in November 2021, still lists itself as not yet recruiting, and its record has not been updated since [36].
How long does it take for berberine to lower cholesterol?
Within the length of a short trial. In the Hong Kong trial in women, the fall was already there at the first check, at eight weeks, and within the margins of error similar at twelve [27], and the earlier version of the 2023 review found no clear difference between trials shorter and longer than 12 weeks [24]. What the trials do not show is the gap growing with time: in the 2025 pooling it shrank as trials got longer, and in the six-month trial it was smaller than in either pooling [25][15]. The pooled trials ran 4 to 24 weeks, so they say nothing about years [24].
How much berberine should I take to lower cholesterol?
We cannot give you a dose; we can tell you what was tested. The commonest dose in the trials was 500 mg twice a day, 1 gram in all, and the 2025 pooling’s ranged from 300 to 1,500 mg a day [25]. More did not reliably do more: the 2025 pooling found no significant link between dose and the LDL change, and the earlier version of the 2023 review no clear difference between trials below and above 1,000 mg a day [25][24]. The dose section above explains why two bottles labelled 500 mg may not hold the same thing, and the safety section below why France’s food-safety agency set a provisional limit of 0.1 mg a day [23].
What is the downside to berberine?
In the cholesterol trials, mostly the gut. The 2023 pooling found stomach and bowel complaints tended to be more common on berberine: 2% to 23% of people across the trials that reported them, against 2% to 15% on placebo [24]. In the 2020 diabetes trial, 14 of 98 people on berberine had them, against 4 of 103 on the placebo [26]. In the Hong Kong trial, 8 of 50 women on berberine dropped out against 2 of 50 on the placebo, 5 of the 8 because of side effects [27]. The six-month trial found side effects about as common on either, but everyone in it had first taken berberine for a month, and anyone who could not tolerate it was left out before the trial began [15].
HDL can move the wrong way. In the 2020 diabetes trial it slipped slightly on berberine while it held steady on the placebo, a gap the trial reports as significant [26]; in the 16-week trial it ended lower on berberine than on the placebo, by the trial’s own table and by the 2025 pooling’s recalculation [16][25]; and in the Hong Kong trials it came out a little lower in women and in men alike, gaps too small to tell apart from chance [27]. Whether a change of a few points in HDL matters for the heart is doubtful: raising it with drugs did not clearly cut heart events in most of the big trials, as our HDL verdict sets out.
Berberine also changes how much of some drugs reaches the blood, as the safety section below sets out. For statins specifically, one 2019 study gave 60 healthy adults in China, in groups of 12, simvastatin alone or with berberine (300 mg every eight hours) for a week, and found no obvious change in how much simvastatin reached their blood [33]. That is a small, short study in healthy volunteers, not a clearance.
This is journalism, not medical advice. If you take a statin or any other cholesterol medicine, or any prescription drug, ask the clinician who prescribes it before adding berberine, and do not start or stop a drug because of this page.
Rated in words. That berberine lowers LDL cholesterol a little more than a placebo does, over trials of one to six months, in adults with raised cholesterol or a metabolic condition: Supported. The placebo-controlled poolings agree on the direction, and so do most of the trials we opened. The known limits: the trials are short, mostly from China and uneven in quality; the gap was smaller in the six-month trial and not significant in the 16-week trial or in men; a 2024 pooling of 11 comparisons of berberine alone, four of them not against a placebo alone, put it at about 9 mg/dL, with a range that leaves no change on the table, though by our own re-run that doubt comes from one of two trials in it rated at high risk in 2026, the one from India that set berberine against two other treatments, and without the two it comes to about 13 mg/dL, with a range that no longer includes no change; and two trials inside the 2023 pooling, one of them also in the 2025 pooling, were rated in 2026 at high risk of compromised integrity, though in the earlier version of the 2023 review the trials that enrolled both sexes, which leave those two out, still gave LDL a fall of about 18 mg/dL (0.47 mmol/L) [24][25][26][15][16][27][30][35]. That it raises HDL: Unsupported, of the tested kind: it was tested and did not hold up. The rise in women came from two trials whose integrity has since been questioned. The ten trials in both sexes in the earlier version of the 2023 review point both ways, three clear rises and one clear fall, and pooled they put the rise at about 2 mg/dL, too small to tell apart from chance. The 2025 pooling found HDL not significantly changed, and the 2024 pooling put berberine alone at about 1 mg/dL, also too small to tell apart from chance, though each of those two has one of the questioned trials inside it, and the 2024 pooling a second trial the reappraisal rated at high risk, the one from India; leaving both of the 2024 pooling’s flagged trials out, by our own re-run, gives about 2 mg/dL, still too small to tell apart from chance. And the biggest trial in the 2023 pooling and the biggest in the 2025 pooling, and both Hong Kong trials, had HDL ending a little lower on berberine, gaps the first two trials report as significant [24][35][25][30][26][16][27]. That it lowers LDL as much as a statin: Preliminary. The direct comparisons found no significant gap, in trials their own reviewers rated poorly; the indirect estimate puts 40 mg of pravastatin at nearly four times berberine’s effect, with 10 mg ahead too, though three of its seven berberine trials were of barberry [31][32]. Whether berberine prevents heart attacks the way statins were shown to is not rated: of the two registered trials above, the one designed around heart events still lists itself as not yet recruiting, and the other counts them only as a secondary question [34][36]. None of these ratings changes this page’s, which is about weight.
The safety conversation nobody has
“Natural” is doing a lot of work in this category, so here is what has actually been measured.
It changes how much of other drugs gets into you. In 52 kidney-transplant recipients taking cyclosporin A — the drug that stops the body rejecting the new organ — adding berberine left trough blood levels 29.3% higher than in 52 patients randomly assigned to go without it, and raised total drug exposure by 34.5% in a separate study of six patients that measured how much of the drug reached the blood over time. [8] That is a real interaction in real patients with a drug where the dose window is narrow.
How does it do that? Probably in more than one way. In rats, berberine produced “no significant changes in CYP3A activity” — CYP3A being the family of liver and gut enzymes that break down many drugs — but blocked intestinal P-glycoprotein, a pump in the gut wall whose job is to push absorbed drug molecules back out. Block the pump, more drug stays in: in those rats, exposure to the heart drug digoxin rose to as much as 170% of what it was without berberine. [9] In people, the enzymes did move. In a randomised crossover trial, 17 healthy men took berberine (300 mg three times a day) for two weeks and a placebo for two weeks, in random order. On berberine, their exposure to midazolam, a sedative used to measure the enzyme CYP3A4, rose by about 40%, and two other drug-clearing enzymes, CYP2D6 and CYP2C9, slowed as well. [21] The transplant study’s own authors put their result down to CYP3A4. [8]
It can drop blood sugar in people who are not diabetic. In 2025, an athletic man in his forties arrived at an emergency department after collapsing, with a blood glucose of about 16 mg/dL (0.9 mmol/L) — profoundly low. He was taking berberine as a performance supplement. His clinicians noted that berberine-induced hypoglycaemia had previously only been reported in people with diabetes, and believe this was the first reported case involving exercise. [10]
That is one case report. One. It is not evidence that this happens often, and it should not frighten anybody off. It is evidence that the compound is pharmacologically active enough to matter, which is the opposite of the thing being sold as gentle because it comes from a plant.
Europe’s food-safety authority has not found a safe intake. In January 2026 the European Food Safety Authority’s nutrition panel endorsed a draft opinion on supplements made from 13 berberine-containing plants, among them barberry root and bark and goldenseal. It found signs, in laboratory tests on cells, that berberine can damage genes — a concern it says still has to be checked in living animals — and concluded that “no safe intake can currently be established for any of these berberine-containing plant preparations”. [22] It is a draft, not a final opinion: the public consultation ran from March to May 2026, and the authority’s deadline for the final version is February 2027. [22]
France’s food-safety agency, ANSES, had already concluded in 2019 that the safety of these supplements “cannot currently be guaranteed”, and advised children and adolescents, pregnant and breastfeeding women, people with diabetes, and people with liver or heart disorders not to take them. Unable to set a proper safe limit, it set a provisional one: 0.1 mg a day for a 132 lb (60 kg) adult, a level it said a large number of supplements on sale in France probably exceed. Belgium, it noted, caps berberine in supplements at 10 mg a day. The trials on this page mostly tested 1,000 to 1,500 mg a day. [23] Neither agency’s view is a finding about weight, and neither changes this page’s rating.
And if it arrives as a patch, it is not legal
A 2026 paper in Annals of Pharmacotherapy went looking at the transdermal end of this market and found 24 “natural GLP-1” patch products plus one gel, carrying an average of seven ingredients each, with berberine among the most commonly listed. [11]
The finding is not subtle. Under the Dietary Supplement Health and Education Act, a dietary supplement has to be swallowed. A supplement you stick on your skin does not meet the definition, which means, in the authors’ words, “all these products are illegal.” [11] None posted a certificate of analysis. Many were missing the required FDA disclaimer. Many, the authors write, used deceptive advertising.
Set aside whether a patch could push through intact skin a compound that barely reaches the blood even when swallowed. The products are not lawful supplements in the first place.
The verdict
Berberine is not nature’s Ozempic, and the gap is not a matter of degree. In a double-blind trial of 1,961 adults, the 1,306 given semaglutide lost an average of 33.7 lb, 28 lb more than the placebo group. The supplement moves about 1.9 lb more than a comparison group across 15 trials, in pooled analyses that cannot agree with each other, off a literature where 45 of 54 reviews were rated very low quality and obesity had the smallest share of improved outcomes in the set. A six-month double-blind trial in adults with obesity found no difference at all. [15]
What berberine plausibly does is nudge blood glucose and blood lipids in people who have a metabolic problem to begin with. That is a genuine and unglamorous finding, and it is not what anybody is buying it for.
If you have type 2 diabetes, or take any regular prescription medicine — above all one where the dose has to be exact, such as cyclosporin — this is a conversation with your doctor before it is a purchase. Berberine demonstrably changes the amount of some other drugs in your bloodstream, and Europe’s food-safety authority, in its January 2026 draft, could not name any intake of berberine-containing plant preparations it considers safe. France’s food-safety agency advises pregnant and breastfeeding women, children and teenagers, and people with diabetes or liver or heart disorders not to take it at all.
And if what you actually want is the thing the nickname is borrowing from, the honest answer is that the nickname is borrowing from a prescription drug, and that is a conversation with a clinician too.
What would change this verdict: a large, properly blinded trial of a standardised, purity-tested berberine preparation, running longer than twelve weeks, in people whose weight is the primary endpoint. The 2026 reviewers asked for exactly that — they specifically flagged that trials are not reporting purity, potency, or gram amounts. [1] The nearest thing so far is the six-month trial above, which set out to measure the fat packed around the abdominal organs and the fat in the liver rather than weight; neither those nor weight moved more than on the placebo. [15] Until a trial like that says otherwise, the best estimate for this claim is about two pounds, and the range the true average probably sits in runs from just under one pound to three. [1]
Related: apple cider vinegar benefits · is creatine safe · does coffee help you lose weight · do detox teas work
An independent editorial review on 18 September 2026 found that this page’s central comparison did not compare like with like, and that the mechanism we said nobody had measured in a person had been measured. Berberine’s 1.9 lb is already a difference against a comparison group. We set it against semaglutide’s own loss of 33.7 lb, called the gap seventeen-fold, and wrote that measuring both against placebo would widen it. It narrows it: semaglutide beat placebo by 28 lb (12.7 kg), about fourteen times berberine’s figure, and the headline, chart, search description and verdict now use that number. The trial tested semaglutide at 2.4 mg, the dose sold as Wegovy; Ozempic is the same drug sold for type 2 diabetes. We also wrote that we had searched for a trial measuring GLP-1 in people given berberine and found none. A double-blind trial published in 2021 did, and berberine moved GLP-1 no more than placebo; GLP-1 is not mentioned in its PubMed abstract, which is how our search missed it. That makes the verdict stronger. And we called the usual CYP3A explanation for berberine’s drug interactions wrong, on the strength of a study we did not say was in rats; a trial in healthy men found berberine does slow CYP3A4, so the page now gives both.
Also corrected. The 1.9 lb pooled the 15 of the review’s 23 trials that reported weight, five of them testing barberry and one a berberine-based drug; Xiong 2020’s weight result pooled five trials, not ten; there are at least five pooled analyses, not three, and the table now shows five; GRADE rated 312 of 452 outcome results very low, not 110 of 140, and obesity had the smallest share of improved outcomes, not the weakest evidence; berberine has several small trials against diabetes drugs, not one; the 34.5% with gut side effects was 20 of 58 people across both parts of the 2008 study; the under-1% absorption figure comes from rodents; and the transplant comparison group was randomised, not matched. The funding row said nothing was stated: Novo Nordisk funded and designed the semaglutide trial, and drug companies supplied the tablets for two berberine trials now cited. We said berberine is not dangerous. Europe’s food-safety authority, in a January 2026 draft, found no intake of berberine-containing plant preparations it could call safe, and France’s agency advises pregnant and breastfeeding women, children and teenagers, and people with diabetes or liver or heart disorders not to take it; the safety section now says so, and the page adds a six-month trial published in January 2026 in which weight did not move. We removed an unsourced comparison with weight swings between a Tuesday and a Friday, and “the ceiling on this claim is two pounds”, which treated an average as a limit. The headline changed from “Ozempic Is 34” to “Semaglutide Is 28”. The rating is unchanged: Unsupported.
Corrected on 20 October 2026. When we added a 2026 integrity reappraisal of berberine trials in women with polycystic ovary syndrome to this page on 20 October 2026, we applied it to the cholesterol poolings and the HDL figure for women and stopped there. Its four trials sit behind more of the page than that. Two of the 15 trials behind the 1.9 lb weight figure are among them, a 2012 trial in China and a 2023 trial in Pakistan; the 2012 trial is in all five pooled analyses of weight in the table, and a 2022 trial in India is in one of them; the 2024 pooling’s figures for berberine alone, on LDL and on HDL, hold both the 2012 and the 2022 trial, where our rating had counted only the first for HDL and neither for LDL; and the 2012 trial is one of the two trials of berberine alone against a placebo behind a 2017 review’s 20-to-50 mg/dL range. The page now says so where each figure appears. We also wrote, from the reappraisal’s summary table, that the 2012 trial was not registered; its detailed table does not say so, and the trial’s paper prints a registration number without naming a registry, so the page now gives both.
Leaving those two out of the weight pooling, by our own re-run of the review’s numbers, still gives 1.9 lb, and leaving the flagged trials out of the other four weight poolings in the table moves none of them across the line between a significant and a non-significant result. In the 2024 pooling’s LDL figure for berberine alone, the trial from India, which set berberine against two other treatments, pulls the figure toward no change: without the two flagged trials, by our re-run, it is about 13 mg/dL rather than 9, and its range no longer includes no change. The table now also gives, from their charts, how many trials two of the reviews pooled for weight, and our entry for the 2017 review pointed to the wrong one of its tables. No rating changed: the claim this page rates is still Unsupported, and the cholesterol ratings stand as they were.