Is Palm Oil Bad for You? Against Liquid Oils It Raised LDL About 9 mg/dL in 26 Trials. The Cancer Worry Rests on Animal Studies.

“Palm oil is not an outright poison.” That is how Google’s AI answer opens when you ask whether palm oil is bad for you, and among the pages it cites are a palm-oil company’s blog, a chocolate maker that sells palm-oil-free chocolate and a cardiac centre’s video [1]. Plenty of people ask: “is palm oil bad for you” is searched about 22,200 times a month in the United States (from a paid keyword database, pulled 20 October 2026) [1].
For your cholesterol, it depends on what the palm oil replaces. In place of liquid vegetable oils, it raised LDL by about 9 mg/dL in a pooling of 26 trials; in place of butter, it comes out ahead in a network of trials, though the two trials in the 2015 pooling that set it directly against butter or lard found LDL about the same, and a third, against lard, found it lower on palm oil. [2] [3] [4] We found no randomised trial that gave people palm oil, or took it away, and counted heart attacks, strokes or deaths, and the cancer worry rests on animal studies of a contaminant that refining puts into the oil [5].
Two terms first. LDL is the cholesterol that guidelines and cholesterol drugs mainly target, the kind people call bad; HDL is the kind usually called good. Both are reported in mg/dL, milligrams per decilitre, the unit on an American lab report. The trials report millimoles per litre, and we give their figures in brackets.
Does palm oil increase cholesterol?
Against the oils it usually replaces, yes. The clearest pooling is a 2015 meta-analysis, a study that combines trials to get one estimate, from the National University of Singapore [2]. It gathered 27 trials, published from 1985 to 2011, that fed people palm oil or palm olein, its liquid part, for two to sixteen weeks against an oil low in saturated fat: sunflower, safflower, canola, olive, soybean, peanut and others. 807 people started them, and in 20 of the trials the researchers supplied every meal [2].
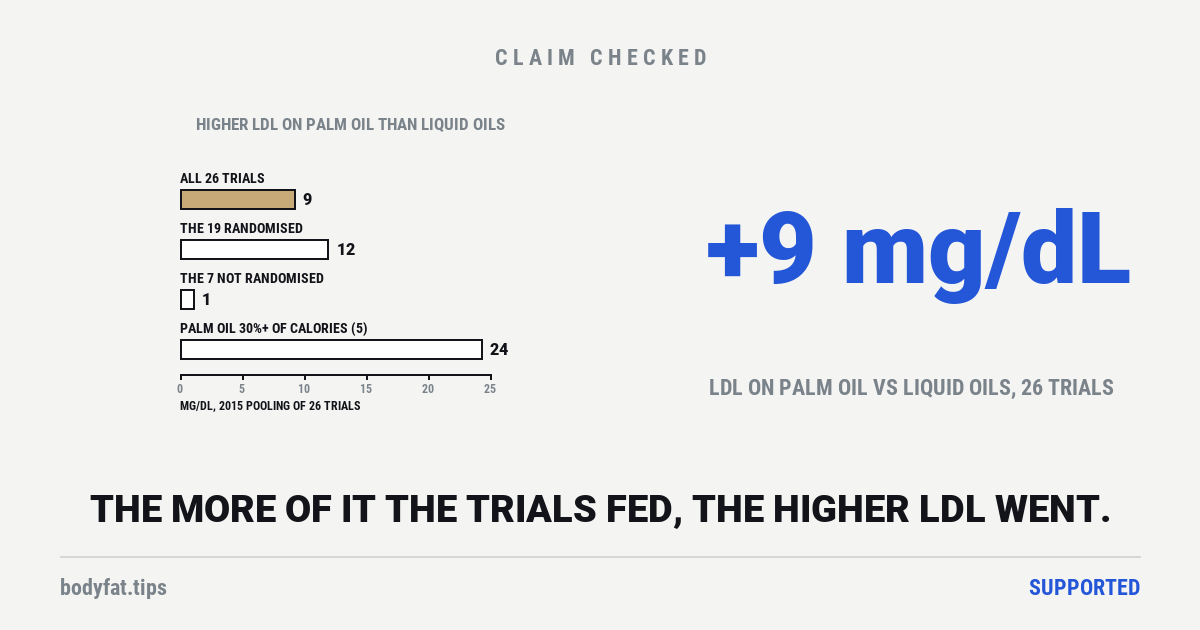
In the 26 that measured it, LDL ended about 9 mg/dL higher on palm oil (0.24 mmol/L) [2]. The confidence interval, the range the true average probably sits in, ran from about 5 to 13.5 mg/dL, by our conversion: a range for an average across trials, not a forecast for any one person [2]. HDL was a little higher on palm oil too, by about 0.8 mg/dL (0.02 mmol/L), and triglycerides, the other blood fat on the test, could not be told apart [2].
Who ran the trial, and how, mattered. In the 19 randomised trials, where chance decided who got which oil, or in which order, LDL was about 12 mg/dL higher on palm oil (0.31 mmol/L); in the 7 that were not randomised it was about 1 mg/dL, with a range that included no difference (0.03) [2]. The amount mattered too: about 24 mg/dL higher (0.63) in the five trials where palm oil supplied 30% or more of the day’s calories, about 9 (0.24) where it supplied 20% to under 30%, and about 2 (0.06), with a range that included no difference, below 20% [2]. Thirty percent of a 2,000-calorie day is about 67 grams of oil, a little under 5 tablespoons, by our arithmetic.
Before printing a pooled figure we look for the biggest study inside it. Here it is a Malaysian trial of 110 boys aged 16 and 17, not randomised, about one in seven of the people who started, by our arithmetic; it sits among the non-randomised trials, whose pooled result was close to zero, so it is not what produces the 9 mg/dL [2].
Three cautions, all from the paper itself. The trials varied a great deal: I-squared, the share of the spread between the trials’ results that is more than chance would produce, was 83%, and fell to 27.5% among the randomised trials once the amount of oil and the comparison oil were allowed for [2]. Small trials reporting bigger rises hinted that some less striking trials may never have been published, which the authors call possible publication bias, though they note the small trials also fed more oil and were more often randomised [2]. And in the randomised trials, palm oil raised LDL about 38% less than a standard formula based on its fatty acids predicts [2].
Most of these trials, 15 of the 27, were paid for partly or wholly by industry, and they found smaller rises than the government-funded ones: about 4.6 mg/dL against 21.7 (0.12 and 0.56 mmol/L) [2]. But they had also fed less palm oil, and once the amount was allowed for, the funding gap was no longer clear [2].
| Palm oil compared with | Trials | LDL on palm oil (mg/dL) |
|---|---|---|
| Safflower oil high in oleic acid [2] | 2 | About 22 higher (0.57 mmol/L) |
| Sunflower oil high in oleic acid | 6 | About 21 higher (0.54) |
| Sunflower oil high in linoleic acid | 2 | About 13 higher (0.33); range includes no difference |
| Soybean oil | 3 | About 13 higher (0.33); range includes no difference |
| Canola oil | 4 | About 8 higher (0.20) |
| Rice bran, corn, safflower and mixtures | 5 | About 8 higher (0.21); range includes no difference |
| Olive oil | 4 | About 4 higher (0.11); range includes no difference |
| Peanut (groundnut) oil | 3 | About 6 lower (−0.15); range includes no difference |
| Butter or lard | 2 | About the same (−0.01); range includes no difference |
A second team, drawing largely on the same trials with some newer ones, found the same direction. A 2020 review from the University of Malaya found LDL about 9 mg/dL higher on palm oil than on oils rich in monounsaturated fat (0.24 mmol/L) in 16 crossover studies of 365 people, where each person ate both diets in turn, and graded that evidence low; against oils rich in polyunsaturated fat, about 10 mg/dL higher (0.26) in five crossover studies of 114 people, graded moderate [6]. One study of 60 people that ran the two groups side by side found the reverse, LDL about 11 mg/dL lower on palm oil (−0.28 mmol/L) [6]. Counting that study, the review’s overall figure against monounsaturated oils was about 8 mg/dL (0.20 mmol/L) [6]. Against polyunsaturated oils, three side-by-side studies of 152 people varied widely, and counting them the overall figure was about 17 mg/dL (0.44 mmol/L), with a range from almost nothing to about 34 higher [6]. About half that review’s trials, it notes, were paid for by a palm-oil organisation or by a company supplying the comparison oil [6]. A 2021 umbrella review, a review of the reviews that drew on the earlier poolings, put the gaps at about 9.2 mg/dL against monounsaturated oils and 3.4 against polyunsaturated ones [7].
The largest pooling by count, 51 studies in 2014, found total cholesterol, LDL and HDL significantly higher on palm oil than on diets rich in stearic acid or in monounsaturated or polyunsaturated fat, and most of the same markers lower than on diets rich in two other saturated fats, lauric and myristic acids; the rise against the unsaturated fats was not significant in young people or in diets lower in fat [8]. We read it in full, in an archived copy of the journal’s page. It was paid for by a Milan university and an Italian chocolate and confectionery company, which the paper says has “a financial interest in products containing” palm oil; that company funded one author for this work and two others in the previous three years, and a fourth author had been funded by an Italian confectionery and pasta industry association that, the paper says, “might have an interest in the outcome of the study”. The paper says the funders had no role in the analysis [8].
Two poolings found no clear difference. What they are made of matters. One, in 2019, was paid for by Malaysia’s palm oil board, and three of its seven authors give the board’s nutrition unit as their affiliation [9]. It set palm olein against a mix of oils that included coconut oil and lard: LDL about 2 mg/dL lower on palm olein overall, with a range from about 11 lower to 6 higher (−0.06 mmol/L) [9]. That overall figure mixes two kinds of comparison. Against coconut oil and lard, in five comparisons, LDL was about 19 mg/dL lower on palm olein (−0.50 mmol/L). Against the liquid oils, the comparison this page rates, it came out higher, by ranges that included no difference: about 7 mg/dL higher than on oils rich in monounsaturated fat, in nine comparisons, from about 4 lower to 17 higher (0.17 mmol/L), and about 2 mg/dL higher than on soybean oil, in two (0.04 mmol/L) [9].
The other, also 2019, pooled 11 trials, and its own table lists the same board as the funder of 10 of them; LDL about 2 mg/dL lower, with a range reaching about 0.4 higher (−0.05 mmol/L) [10]. Its rule was to include only randomised trials, yet 42.6% of the weight behind that figure, by its own chart, is one study its own table calls a before-after study: the Malaysian study of 110 boys that is also the biggest in the 2015 pooling, where it sits among the non-randomised trials [10] [2]. The section below on why reviews disagree comes back to both.
Two appraisals have been published since. In February 2024 the WHO published a rapid overview of the systematic reviews comparing palm oil with other vegetable oils, prepared for it by an evidence centre at Stellenbosch University in South Africa, with searches to January 2022 [11]. It left the 2014 pooling and the 2019 palm-olein pooling out of its analysis, citing their funding, and used the other five reviews [11]. Judged on AMSTAR 2, a standard checklist of how well a review was done, the 2015 pooling, the other 2019 pooling and a 2018 review of heart outcomes came out “critically low quality”, meaning more than one critical flaw, and the 2020 review “low quality”; one flaw it named in the 2015 and 2019 poolings was mixing randomised and non-randomised trials [11]. It judged the network analysis’s credibility “sufficient”, on a separate checklist for network analyses, while noting that it had not accounted for things that could change the effect or explored why its trials differed [11]. Its conclusion on LDL: the average rise reported by the largest review in each comparison, against vegetable oils in general and against monounsaturated and polyunsaturated oils separately, was above 0.13 mmol/L, about 5 mg/dL by our conversion, the line it drew, for want of an agreed one, for a change that could matter to heart risk [11]. Its own sections are less sure. It called the effect on LDL in the polyunsaturated-oil crossover trials possibly “trivial”, read the 2019 pooling whose trials the palm oil board mostly funded as showing a “trivial” effect on LDL too, called the network’s comparisons of palm oil with each of nine liquid oils “mostly indicative of trivial increases”, and summed up the reviews’ LDL results as “variable” [11].
A 2024 umbrella review, searched to July 2023, graded the evidence that palm oil raises total and LDL cholesterol “low to very low certainty”, the bottom two of the four grades the standard scale uses, and said palm olein has “minimal impact on lipid parameters” against liquid oils [12]. Three of its eight authors give the palm oil board’s nutrition unit as their affiliation, it reports no funding and no conflicts, and its palm olein conclusion rests on one review: the board-funded 2019 pooling above [12].
Which oils are not healthy?
On LDL, the fats that came out worst in the largest comparison were not oils: butter and lard. A network meta-analysis, which ranks many options at once by linking up trials that each compared two of them, put 54 trials and 2,065 people together across 13 oils and fats [3]. For each 10% of calories swapped, about 200 calories on a 2,000-calorie day, palm oil left LDL about 9 mg/dL lower than butter (0.24 mmol/L), as did every other oil in it except hempseed oil [3]. Against lard, beef fat and coconut oil, palm oil could not be told apart [3].
Against the liquid oils, the network could separate only one: sunflower oil left LDL about 4 mg/dL lower than palm oil (0.10 mmol/L) [3]. Soybean, canola, corn, olive and safflower oil came out lower than palm oil or level with it, by ranges that included no difference, by our reading of its table [3]. The authors say the network’s estimates more often came from comparisons pieced together through other oils than from trials that set two fats side by side [3]. Our vegetable oil verdict reads the same table for soybean oil, and our canola verdict for canola.
The direct evidence on butter is thin. The one trial in the 2015 pooling that set palm oil against butter, 29 men, not randomised, and the one against lard, together found LDL about the same on palm oil (−0.01 mmol/L) [2]. A third direct trial, whose lard arm is not in that pooling, points the other way for lard: in China, 120 young men with normal cholesterol were randomly assigned to palm oil, soybean oil, peanut oil or lard for six weeks, and LDL ended significantly lower on palm oil than on lard, having fallen about 13% from the start on palm oil and risen about 31% on lard [4]. A Malaysian palm oil research institute paid for it [4]. One randomised trial set butter against palm stearin, the hard part of palm oil left when the liquid is drawn off: 24 adults with normal cholesterol ate each fat for three weeks under controlled feeding, and LDL ended 11% to 13% higher on butter, in both its low-carbohydrate and high-carbohydrate groups. Malaysia’s palm oil board paid for it [13]. So “better than butter” rests mostly on the network’s indirect comparisons and one small trial of palm oil’s hard fraction.
Which is healthier, groundnut oil or palm oil?
For LDL, the trials could not separate them. Groundnut oil is peanut oil, and in the 2015 pooling’s three peanut-oil trials LDL was about 6 mg/dL lower on palm oil, with a range from about 15 lower to 3 higher (−0.15 mmol/L) [2]. Olive oil was close too: about 4 mg/dL higher on palm oil in four trials, with a range from about 1 lower to 10 higher [2]. The clear gaps were against sunflower, safflower and canola oils, as the table above shows. Peanut oil is not one of the network’s 13 fats [3]. Olive oil has its own verdict.
Is palm oil bad for your heart?
That is a different question from cholesterol. We found no randomised trial that gave people palm oil, or took it away, and counted heart attacks, strokes or deaths [5].
A 2018 systematic review from Malaysia’s Institute for Medical Research looked for any study of palm oil and heart disease or stroke, trial or observational, up to mid-2017 [14]. It found three reports from one Costa Rican study and one study of whole countries, which it counted for both heart deaths and stroke deaths, graded all of it very low, and said it “could not establish strong evidence for or against” [14].
The Costa Rican study is the closest thing to a test in people. It compared 2,111 adults who had survived a first heart attack with 2,111 people from the same areas, matched by age and sex [15]. People who cooked with palm oil had 1.33 times the odds of a heart attack of people who cooked with soybean oil low in trans fat, with a range from 1.08 to 1.63, after allowing for smoking, alcohol, diabetes, blood pressure, waist, activity, income, calories and fibre; 1.00 would mean no difference [15]. Against other oils, mostly sunflower, the figure was 1.23, with a range from 0.99 to 1.52, so no difference was still possible; against soybean oil high in trans fat, 1.14, from 0.84 to 1.56 [15]. Palm-oil users were poorer and more often smokers, 29% against 14% of people using other oils, and a study that compares people after the fact can adjust for such things but cannot rule them out [15].
A second, smaller case-control study, published in 2021 after that review’s search, comes from three hospitals in southern Ethiopia. It compared 140 patients with ischaemic heart disease, the kind caused by narrowed heart arteries, with 417 patients at the same hospitals who had minor complaints unrelated to the heart, recruited from whoever was available rather than chosen at random [16]. Of the heart patients, 79.3% cooked with palm oil, against 56.1% of the others; after allowing for education, high blood pressure, exercise, fruit and vegetables and obesity, palm oil users had 2.12 times the odds of heart disease of people who cooked with sunflower oil, with a range from 1.23 to 3.63 [16]. Its authors note that a study like this cannot show which came first, and that people’s recall of their own habits may be biased [16].
The study of whole countries is looser still. Across 23 countries from 1980 to 1997, each extra kilogram of palm oil eaten per person per year went with 68 more heart deaths per 100,000 people aged 50 and over in ten developing countries, with a range from 21 to 115, and 17 more in thirteen high-income ones [17]. Studies like this follow countries, not people, and cannot tell who ate the oil. Our vegetable oil verdict sets the same study beside other country comparisons.
What has been tested in trials is cutting saturated fat in general, the fat that makes up about half of palm oil; our saturated fat verdict rates that Supported, for modestly fewer cardiovascular events, which is not the same as testing palm oil. The 2015 pooling’s authors estimate, from trials of cholesterol-lowering, that the 9 mg/dL rise might mean about 6% more coronary deaths and events; that is their extrapolation, not something a palm oil trial measured [2].
Is palm oil cancerous?
We found no study in people that measured palm oil eaten against cancer [5]. The worry comes from two kinds of animal study, and the first is about refining, not the oil.
When vegetable oils are refined, a step heats them above 200°C (392°F), and in it contaminants called glycidyl esters form; in the gut they are thought to release almost all their glycidol [18]. Europe’s food safety authority, EFSA, found the highest levels in palm oil: in samples from 2012 to 2015, an average of about 4,000 micrograms of glycidol per kilogram of palm oil (3,955 µg/kg), against 166 to 650 in rapeseed, soybean, sunflower, coconut and maize oils, and 421 in palm kernel oil [18]. A microgram is a millionth of a gram. Glycidol caused tumours in several organs of rats and mice given it for two years, probably by damaging DNA, and the WHO’s cancer agency classes it as probably carcinogenic to humans [18].
EFSA judges a contaminant like that by its margin of exposure, how far people’s intake sits below the dose that caused tumours in animals, and counts a margin of 25,000 or more as low concern [18]. For teenagers and adults, older people included, the margin ran from 102,000 at average intake down to 9,300 for the highest eaters; for babies, toddlers and older children, from 34,000 down to 4,900; for infants fed only formula it was about 5,500 on average and 2,100 at the high end; and EFSA concluded that margins below 25,000 “indicate a health concern” [18]. A second contaminant from the same step, 3-MCPD, damaged the kidneys of rats; EFSA’s 2018 update found adults’ intake under its safe daily limit and young children’s slightly over it at the high end [19].
Europe acted on the oil: EU law now caps glycidyl esters at 1,000 micrograms per kilogram in oils sold to shoppers or used in food, about a quarter of palm oil’s 2012 to 2015 average by our arithmetic, and at 50 in powdered infant formula [20]. In the United States, scientists at the Food and Drug Administration testing infant formulas bought from late 2017 to early 2019 found the levels had fallen since 2016 at three of four makers, and say two of them appear to use palm oil refined to cut these contaminants [21]. We read that paper as its abstract.
What those opinions settle is that refined palm oil carried more of these contaminants than other oils, and that at some intakes, young children’s and infants’ above all, the margin is too thin for EFSA’s comfort. What they do not settle is whether anyone has got cancer from palm oil: the tumour evidence is from animals, and EFSA’s measurements predate the EU caps [18] [20].
The second is a 2021 study in mice. Once oral tumours had appeared, mice were fed a diet rich in palm oil, rich in olive oil, or a standard one for ten days; tumour cells from the palm-oil mice spread more when they were transplanted into new mice [22]. It is about the spread of an existing cancer, in mice, not about whether the oil starts one.
One cancer-related hazard in palm oil really has been found on American shelves, and it is not the oil. In a survey published in 2016, FDA scientists tested red palm oils bought in Washington, DC-area shops selling African foods, and online; four of the 20 brands contained Sudan IV, a red dye banned from food in the US and the EU, while the red palm oil supplements they tested had none above the detection limit [23]. The paper calls the Sudan dyes toxic and carcinogenic, and also notes that the WHO’s cancer agency places them in its group 3, which that agency defines as “not classifiable as to its carcinogenicity to humans” [23].
Is refined palm oil good for health?
Not better than the liquid oils, on the trials: refined palm oil is the kind that raised LDL against them, and the kind that carried the most refining contaminants in EFSA’s data [2] [18]. Refined palm oil, red palm oil and palm kernel oil are three different products, and the evidence does not transfer between them. The trials in the 2015 pooling used the most typical palm oil or palm olein; the pooling left out red palm oil, palm kernel oil and palm stearin, the hard fraction [2].
Red palm oil is refined differently, to keep the carotenoids that colour it and that the body turns into vitamin A [24]. A 2017 pooling of nine randomised trials, mostly in children and pregnant or breastfeeding women in India and Africa, found it cut the share of people short of vitamin A by about 45% in three trials (a risk ratio of 0.55, with a range from 0.37 to 0.82) and raised blood vitamin A in seven trials of 1,127 people [24]. The review was part-funded by Malaysia’s palm oil board [24]. That is a finding for people short of vitamin A, not a reason for anyone else to eat it.
Which plant-based oils are high in saturated fat?
Coconut oil and palm kernel oil, at about four fifths saturated: USDA’s food data put them at 82.5 and 81.5 grams of saturated fat per 100 grams [25]. Palm oil is about half: the Costa Rican study’s analysis of the palm oil sold there found 49.7% saturated, 39.0% monounsaturated and 9.6% polyunsaturated fat, and the 2015 pooling gives 40% to 50% [15] [2]. For comparison, butter’s fat is about 63% saturated, by our arithmetic from USDA’s figures, and lard’s about 39% [25]. The liquid oils are far lower, and our canola and olive oil verdicts give their figures.
How is palm kernel oil different from palm oil?
It comes from the seed, not the fruit, and it is a different fat. Palm oil’s saturated fat is mostly palmitic acid; palm kernel oil’s is mostly lauric acid, 47.0 grams per 100, like coconut oil’s [2] [25]. How lauric acid behaves in feeding trials, and why its effect on heart disease is uncertain, is on our saturated fat verdict. Palm kernel oil was not among the 13 fats in the network analysis [3], and we rate nothing about it on this page.
Is palm oil a seed oil?
No. Palm oil is pressed from the flesh of the oil palm’s fruit; palm kernel oil comes from the seed inside it [2] [1]. The seed oils people argue about, soybean, canola, sunflower and the rest, have their own verdict, which also sets out two overfeeding trials that compared palm oil with sunflower oil for liver fat.
Who these trials were done on
The 2015 pooling’s trials were in adults and older teenagers, with normal or raised cholesterol, in the United States, Australia, Europe and Asia, with a few elsewhere; ages ran from teenagers to people in their sixties, and the trials lasted two to sixteen weeks [2]. The network’s trials ran three to 27 weeks in 2,065 people whose average ages ranged from 22 to 84 [3]. The heart studies were Costa Rican adults under 75 [15] and adult patients at three hospitals in southern Ethiopia [16]. The vitamin A trials were mostly in children and pregnant or breastfeeding women where deficiency is common [24].
So read yourself against them. The trials fed palm oil as 12% to 43% of the day’s calories [2]. A medical school’s consumer health letter notes that in the United States palm oil “accounts for a very small percentage of overall fat consumption” [1]. If yours comes in the odd cookie, you are far below the amounts the trials fed. If you cook with it daily, as in the soups and stews where red palm oil can be eaten “in large amounts (several cups) daily”, in the FDA scientists’ words, you may be in the range the trials tested [23]. If your LDL is high, what to eat is a question for a clinician or dietitian who knows your numbers; the foods that lower cholesterol have their own verdict.
If palm oil raises LDL, why do some reviews say it doesn’t?
This section is the desk’s own reasoning, and it is labelled as such. Several poolings looked at palm oil and blood fats, and two of them found no clear rise at all. Here are three ways to fit that together, each rated.
Answer one: it depends what the palm oil is set against. Within the 2015 pooling, the rise was clear against oleic sunflower and safflower oils and canola, and not clear against olive or peanut oil [2]. A pooling whose trials leaned on the second kind of comparison would find less, and one that mixed in solid fats would find less still. That is what happened inside the 2019 palm-olein pooling: its overall null splits into LDL about 19 mg/dL lower on palm olein than on coconut oil and lard, and about 7 mg/dL higher, by a range that included no difference, than on the monounsaturated oils [9]. That the rise depends on the comparison oil is measured, in the 2015 pooling and inside that one; that it explains the other 2019 pooling’s null is a surmise, and its trials used a mix of comparison oils [10].
Answer two: the dose. The rise was clear when palm oil supplied a fifth or more of the day’s calories and not below that [2], and the 2014 pooling found the rise not significant in diets lower in fat [8]. But this explains less of the disagreement than it seems: the 2019 pooling that found no clear rise drew on trials feeding palm oil at 17.5% to 24% of calories, where its table says, most of them at or above the fifth at which the 2015 pooling did find one [10]. Both tables are measured; the comparison is ours, and it cuts against this answer.
Answer three: who ran and paid for the trials. Non-randomised trials found close to no rise, and industry-funded trials found less than government-funded ones, though mostly because they fed less oil [2]. The 2014 pooling saw the same pattern: the rise was less evident in trials the palm oil board funded than in those others paid for, and its authors note that most Asian trials were board-funded, in young people with normal cholesterol, on lower-fat diets, so those things travel together [8]. The design point reaches one null pooling directly: 42.6% of its weight is the non-randomised Malaysian study of 110 boys [10]. That much is measured, in the reviews’ own tables and chart. One null pooling was written partly by the palm oil board’s staff, and the other’s trials were mostly paid for by the same board [9] [10]; WHO’s 2024 overview left the first of them, and the 2014 pooling, out of its analysis, citing their funding, and the newest review of reviews, written partly by the same board’s staff, rests its view of palm olein on that same pooling [11] [12]. That is an observation about who ran the research, not a measurement of bias, and we mark it as one.
Put the three together and here is what we think is true, stated plainly so you can disagree with it: palm oil behaves like the saturated fat it half is: the more of it that replaces a liquid oil, the higher LDL goes, and a little of it in place of olive or peanut oil barely registers.
What we could not find, and would like to: a trial that gave people palm oil or a liquid oil for years and counted heart attacks. We found no randomised trial that did [5]. Until one reports, the case against palm oil’s effect on the heart runs through LDL, the two case-control studies we found, in Costa Rica and Ethiopia, and a study of 23 countries. If you know of such a trial, the corrections line on this site is open.
Where “palm oil raises your cholesterol” came from
The research is old, and it did not set out to judge palm oil. In 1985 a US trial fed 20 patients liquid diets with 40% of their calories from fat, as palm oil, high-oleic safflower oil or high-linoleic safflower oil; in the 12 with normal triglycerides, both safflower oils lowered LDL, equally, compared with the palm oil diet [26]. Palm oil was simply the saturated fat. We read that trial as its abstract.
The framing came from the top. In 2003 a WHO and FAO expert report called the evidence “convincing” that myristic and palmitic acids raise the risk of cardiovascular disease, while noting that coconut and palm oil “may be an important source of energy for the poor” [27]. Palmitic acid is palm oil’s main saturated fat [2]. A palm oil promotion council questioned the report’s palm-oil concerns while it was being drafted, a 2019 paper in the WHO’s own journal reports [28]. Two decades on, WHO’s page for an expert group on tropical oils, which first met in May 2024, says WHO “is planning to develop” a guideline on them, and lists none among its publications [29]; its 2024 overview of the reviews is, its publication page says, evidence for interim policy talks while countries wait [11].
Then it spread in both directions. Google’s AI answer today says palm oil is high in saturated fat and that liquid oils are better for long-term heart health, and the related searches ask whether palm oil is bad for your heart, whether it raises cholesterol and whether it is cancerous [1]. A cardiac centre’s video in the same answer is titled “Could the Palm Oil You Use Every Day Be Harming Your Heart?” [1]. On the other side, a health publisher’s page ranking for the same search says palm oil “generally appears to have beneficial effects” on heart risk factors and quotes the 51-study pooling only for its comparisons with trans fats and with lauric and myristic acids, not for the one in which palm oil came out worse [1] [8].
And it sells, both ways. A chocolate maker’s page cited in the AI answer warns that palm oil’s saturated fat can lead to “increased levels of cholesterol and an increased risk of heart disease”, beside a link to its palm-oil-free chocolates [1]. A palm-oil company’s blog in the same answer lists “palm oil is bad for the heart” as a misconception and says there is no cholesterol in palm oil; a plantation company’s page says the same, and both quote a 2015 review’s line that palm oil “does not have incremental risk for cardiovascular disease” [1] [30]. That review is a narrative review, not a pooling of trials [30]. The same paragraph of the blog concedes that some studies found palm oil produced LDL “in slightly higher amounts than other vegetable oil” [1], and that is the finding that matters: the cholesterol line is true and beside the point, because what raises LDL in the blood is saturated fat, and the same blog puts palm oil at roughly half saturated fat [27] [1].
None of this is aimed at anyone who eats palm oil. By one count it is in around half of everyday packaged products [28], and nobody chose it fat by fat. It is the sellers on both sides, the ones warning you off it to sell you the alternative and the ones telling you it is cholesterol-free, who are selling a simpler answer than the trials gave.
What this is rated, and what the rating covers
Supported — for the claim that palm oil, eaten in place of liquid vegetable oils, raises LDL cholesterol.
It is rated Supported because the 2015 and 2020 poolings, drawing largely on overlapping trials, found the same rise, as did the 2014 pooling and a 2021 review of reviews; because the rise is larger in the randomised trials and at higher doses; because it is what palm oil’s fatty acids predict [2] [6] [8] [7]; and because WHO’s 2024 overview, which set aside the two poolings with funding conflicts, concluded that the largest remaining review in each comparison reported a rise above its line for one that could matter [11]. It is not Established because the trials were short, small and varied, and the poolings re-use many of the same ones, with signs that some went unpublished; because the network analysis could separate palm oil only from sunflower oil; because the rise was not clear against olive or peanut oil; because WHO’s appraisers rated the methods of the 2015 pooling critically low and the 2020 review low, and a 2024 review of reviews graded the evidence low to very low certainty; and because two poolings found no clear difference overall, though against the liquid oils alone one of them leaned toward higher LDL on palm olein, and the other rests 42.6% on one non-randomised study [2] [3] [11] [12] [9] [10].
Each part, rated alone, in words. That palm oil is better than butter for your LDL: Preliminary. The network analysis puts it ahead, mostly through indirect comparisons. Of the three direct trials of palm oil against animal fats we read, the two in the 2015 pooling, one against butter and one against lard, found LDL about the same, and a Chinese trial found it lower on palm oil than on lard; the one direct trial of palm oil itself against butter we read is small and was not randomised, and a randomised trial of palm stearin, palm oil’s hard fraction, found LDL 11% to 13% higher on butter, paid for by the palm oil board [3] [2] [4] [13].
That palm oil causes heart attacks: Preliminary. The evidence in its favour is the LDL rise, a case-control study in Costa Rica, a smaller hospital-based one in Ethiopia and a study of 23 countries; we found no randomised trial that counted heart attacks [15] [16] [17] [14] [5].
That palm oil causes cancer: Preliminary. The evidence in its favour is from animals: a contaminant that refining forms, most of all in palm oil, caused tumours in rats and mice, and a palm-oil diet made existing tumours spread in mice. We found no study in people that measured palm oil eaten against cancer [18] [22] [5].
That red palm oil raises vitamin A in people short of it: Supported, in nine small trials pooled by a review the palm oil board part-funded [24].
What is not rated here: palm oil’s effect on forests and wildlife, a real question and a different one; palm kernel oil on its own; palm vitamin E supplements; and the frame above, which is this desk’s reasoning from the evidence rather than a result the evidence delivered. It is marked as ours so that you can weigh it as ours.
This is journalism, not medical advice. If you are managing high cholesterol, what you eat, and whether you need a drug, belongs with a clinician or dietitian who knows your numbers. How we read a study, and what each tier means, is set out here.
- Does Caffeine Dehydrate You? Not at Ordinary Intakes: in Trials, Coffee and Tea Hydrated About as Well as Water. The Extra Urine Shows Up at Big Doses.
unsupported - Does Losing Weight Lower Cholesterol? Mostly the Triglycerides. LDL Fell About 0.6 mg/dL per Pound Lost, and Not on Every Diet.
supported - Foods That Lower Cholesterol Do Lower It, Mostly by Single Digits. The Diet Said to Match a Statin Fell Short of a Low Dose, With the Food Delivered.
established