Does Smoking Raise Blood Pressure? Each Cigarette Does, Briefly. Lasting High Blood Pressure Is Unsettled

“Smoking and nicotine use can immediately raise your blood pressure and may cause chronic hypertension,” runs the standfirst on a retirees’ association’s article that Google’s AI answer cites for this question [1]. Plenty of people ask: “can smoke cause high blood pressure” is searched about 4,400 times a month in the United States, and “does cigarettes cause high blood pressure” about 4,400 more (from a paid keyword database, pulled 20 October 2026) [1].
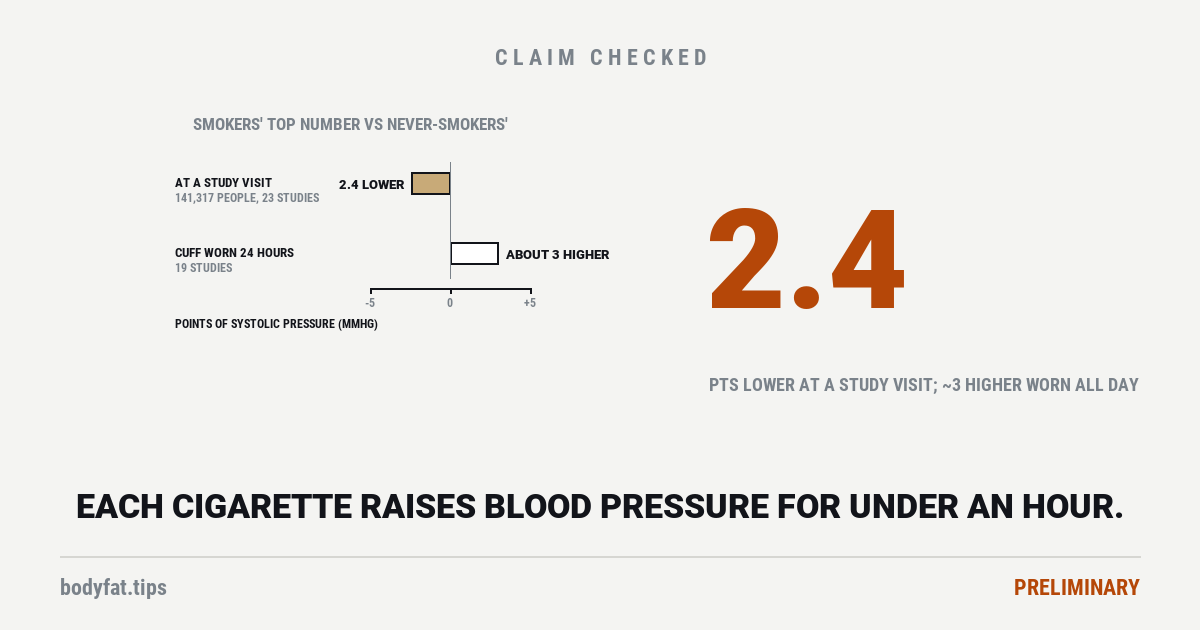
Each cigarette raises blood pressure, for under an hour, and nicotine taken fast, from a vape or a strong nicotine pouch, raises it too, for a short while. Whether smoking causes lasting high blood pressure is not settled. Smokers’ readings at the doctor’s are no higher than non-smokers’, and in a pooling of 23 studies they were lower; their readings through an ordinary day run a few points higher; and of two genetic tests of the question, one found no clear sign that smoking more raises blood pressure. Here is each piece, and why the doctor’s cuff can miss it.
Two words first, because every number below is in them. Systolic is the top number of a reading, the pressure while the heart is pushing; diastolic is the bottom one. Both are in mmHg, millimetres of mercury, the scale blood pressure has always been measured on; there is no American version, and a point on this page is one mmHg. A reading of 130 over 80 is systolic 130, diastolic 80. Our page on lowering blood pressure without a prescription puts the common remedies on the same scale.
Does smoking increase heart rate and blood pressure immediately?
Yes, within minutes, and the experiments that show it are old and clean. In 1976 ten people smoked a cigarette, pretended to smoke one, and smoked one after drugs that block adrenaline’s effects. Smoking raised their pulse and blood pressure; the blocking drugs prevented the rise [2]. In 1998 ten habitual smokers smoked a cigarette on one day and a sham one on another: the real cigarette raised blood pressure, and when a drug held the pressure down, the nerve traffic that tightens blood vessels rose up to threefold [3]. That is the mechanism in plain words: nicotine switches on the sympathetic nervous system, the body’s fight-or-flight wiring, which narrows blood vessels and speeds the heart.
How big a rise? The most careful recent measurement is a 2024 German study run by a federal risk-assessment institute [4]. Fifteen smokers, eight of them women, smoked their own cigarette on one day and held nicotine pouches of different strengths on others. After the cigarette, systolic pressure went from 114.7 to 127.0 within five minutes, about 12 points by our arithmetic, and heart rate from about 73 to about 95 beats a minute [4]. A pouch with no nicotine in it moved systolic pressure 3.6 points, a rise the study could not tell from chance. At the one-hour reading, no product left the top number significantly above where it started; the strongest pouch, 30 mg, still left the bottom number 5.7 points above its start, by our arithmetic from the study’s table, a difference the study counted as significant [4]. The authors call the blood-pressure effects “minor for all study arms” [4].
| What was used | Who | Top number (systolic) |
|---|---|---|
| A cigarette [4] | 15 smokers | Up about 12 points at 5 minutes, from 114.7 to 127.0 |
| A 30 mg nicotine pouch, held 20 minutes [4] | Same 15 | Up about 15 points at 20 minutes, from 115.4 to 130.3 |
| A 6 mg nicotine pouch [4] | Same 15 | Up about 10 points at 20 minutes, from 116.6 to 126.2 |
| A pouch with no nicotine [4] | Same 15 | Up 3.6 points at 5 minutes, a rise the study could not tell from chance |
| Nicotine pouches of 6 to 11.2 mg, a tobacco snus and a 4 mg nicotine gum, each held 30 minutes [5] | 30 Swedish snus users; the pouch maker’s study | Up 3.2% to 6.0% while in the mouth, near the start an hour after |
| A vape with nicotine, against the same vape without [6] | 5 small studies, combined | About 3 points higher just after; 0.16 points at an hour or more |
| A nicotine patch, for 5 days, against cigarettes and a dummy spray [7] | 12 smokers on a research ward | Not significantly different from cigarette days; the dummy-spray days came last and were left out of the tests |
How long does it last? Google’s answer says “about 15 to 30 minutes”, a figure a cardiologist gives in the retirees’ article [1], and the German readings fit that: the top number was high at 5 and 20 minutes and no longer significantly above its start at 40 minutes or at the hour [4]. The catch is the next cigarette. When ten smokers lit one every 15 minutes for an hour, their blood pressure stayed “persistently higher” than in the hour they did not smoke, and six who smoked two an hour through a working day stayed higher all day [8]. One cigarette is a spike. A pack a day is a run of spikes with little time between them.
Does nicotine raise blood pressure on its own?
Mostly, yes, and how fast it arrives seems to matter. In a 1988 experiment ten volunteers took snuff, chewing tobacco, cigarettes and nicotine gum on different occasions: every tobacco product raised heart rate and blood pressure, and the gum, which gave lower nicotine levels, raised them less [9]. A nicotine patch, which releases nicotine slowly through the skin, did not stand out: twelve smokers spent five days each on cigarettes, a patch, a nicotine nasal spray and a dummy spray, and their systolic pressure did not differ significantly between the cigarette, patch and nicotine-spray days, though the bottom number was slightly higher on cigarettes than on the patch; the dummy-spray days, always last, were left out of the study’s statistical tests [7]. A trial of 8,058 smokers who were trying to quit randomly gave them a patch, one of two quit-smoking drugs or dummy treatment, and blood pressure did not differ significantly between the groups [10]. Everyone in it was quitting, so it compares the patch with quitting on a dummy, not with smoking. That trial was paid for and largely run by the two companies that made the medicines [10].
Vapes deliver nicotine fast, and they behave more like cigarettes. Thirty-six people who both smoke and vape stayed on a research ward, smoking only for a spell, vaping only for another, and using neither for a third: over 24 hours, their blood pressure and heart rate were higher on cigarette days and on vape days than on days with neither [11]. A 2025 pooling of short experiments, which combines studies to get one estimate, put a nicotine vape’s effect on systolic pressure at about 3 points over the same vape without nicotine, mostly just after use and close to zero at an hour or more [6]. Before printing a pooled figure we look for the biggest study inside it: here the largest has 24 people per condition, one 15-person study carries over half the weight, and the same volunteers are counted at two or three time points [6]; three of its five studies were of non-smokers, by the review’s own table [6]. We read it as a direction more than a size.
How much do nicotine pouches raise blood pressure?
One of the questions people ask names a brand. The studies tested several brands, which we do not name; what matters is the nicotine. In the German study, pouches of 6, 20 and 30 mg were each held for 20 minutes [4]. Systolic pressure rose by about 10 points with the 6 mg pouch and about 15 with the 30 mg one at its highest reading, by our arithmetic from the study’s table; heart rate rose by about 25 beats a minute with the strongest, about as much as with the cigarette [4]. By the hour mark, none had the top number significantly above its starting reading, though the 30 mg pouch’s bottom number still was [4].
The makers’ own studies found smaller rises, or none they judged to matter. In a study funded by one tobacco company and run under contract, thirty Swedish snus users held its pouches for 30 minutes: systolic pressure rose 3.2% to 6.0%, about 4 to 7 points on a reading of 120 by our arithmetic, and was near the start half an hour after the pouch came out; a 4 mg nicotine gum, tested alongside, did much the same [5]. In another company’s study, 24 people who both smoked and used snus tried weaker pouches, of 5.8 and 10.1 mg, and its employee authors reported “no clinically significant changes” in blood pressure [12], which is a judgement about size, not a test of whether there was a change.
What about years of daily use? We found no study that has followed nicotine-pouch users for years to see whether they go on to develop high blood pressure [13], and a 2026 review of the Swedish evidence says pouches “lack long-term cardiovascular outcome data” [14]. The nearest evidence is tobacco snus, the older Swedish pouch, which delivers nicotine without smoke. Among 42,055 Swedish construction workers who had never smoked and had normal blood pressure at a first check-up, those who used snus were 1.39 times as likely to develop high blood pressure at later check-ups [15]; a later Swedish cohort found 1.33 times, while a pooling found no clear increase in Swedish users [14]. Norway’s public-health institute, in a 2019 assessment for its health ministry, judged that snus probably increases the risk of high blood pressure, as the 2026 review reports it [14].
And when daily users stop? A Swedish group followed 37 people who quit snus or nicotine pouches, 12 of them pouch-only users. After 12 weeks their home systolic pressure had gone up 3.7 points, and their weight up 4.0 lb (1.8 kg) [16]. It was one small group with nothing to compare it against, but it is the one study we found that measured home blood pressure before and after daily users quit [13]. An older US trial measured it at study visits: among 56 smokeless-tobacco users who stopped for eight weeks, given nicotine or dummy gum, blood pressure “did not improve over time” [17]. Meanwhile the web has a precise answer: a consumer health site published in May 2026 says daily pouch use leaves a sustained rise of “under 5 mmHg”. It cites no study for that, and the study that measured blood pressure on and off daily use found it higher off, in people who were also gaining weight [1] [16].
Do smokers have high blood pressure?
Here the story turns. If every cigarette raises blood pressure, smokers should have higher readings than non-smokers. At the doctor’s, they mostly do not. A 1986 study of a working population found higher blood pressure in non-smokers and ex-smokers than in smokers, and could not explain it by weight, drinking, coffee or sport [18].
The Health Survey for England measured 33,860 adults with a nurse’s cuff and left out anyone who had smoked in the half hour before [19]. After allowing for age, men who smoked averaged 140.7 systolic against 139.9 in men who never had; women who smoked lightly were a little lower than women who never had [19]. The one group that stood out was men of 45 and over who smoked: 2.4 to 2.8 points higher than never-smokers, depending on how many they smoked, by our arithmetic from the paper’s table. The authors’ summary: “any independent chronic effect of smoking on BP is small” [19].
A 2015 pooling of 23 population studies went further. Across their 141,317 people, current smokers’ systolic pressure was 2.4 points lower than never-smokers’, and they had high blood pressure less often [20]. The gap shrank once body weight was allowed for, and smokers’ resting heart rate was higher [20]. A 30-year American study of 4,786 Black and White young adults found the same at the clinic: the systolic pressure of people who smoked throughout did not differ significantly from that of people who never smoked [21].
Not every pooling points that way. A 2026 review of vaping and high blood pressure also pooled, as a side analysis, people who smoked only cigarettes, from surveys in the US, South Korea and Scotland and two US cohorts; it counted a diagnosis, a treatment or a reading over a set line, not average readings. People who smoked only cigarettes had high blood pressure more often than people who used neither, 1.25 times the odds, and in the two cohorts they developed it 1.20 times as often over a few years [22]. Its tables give a certainty grade, the authors’ rating of how far a result can be trusted, only for the review’s four main comparisons, of vaping alone and of vaping with smoking, all very low; its summary’s sentence calling the certainty very low follows these cigarette-only figures, but no grade for them appears in the tables [22]. The surveys behind the 1.25 differed from one another more than chance would produce, while the two cohorts agreed [22]. Another 2026 pooling reports long-term smokers’ systolic pressure 6.99 points higher than non-users’, but that figure rests on four small studies, 107 people against 111, one of them of vapers; for cigarettes alone its estimate could not be told from chance [23].
| Study | How blood pressure was read | What smokers showed |
|---|---|---|
| 33,860 adults in England [19] | A nurse’s reading; anyone who had smoked in the past 30 minutes left out | Men 140.7 against 139.9 in never-smokers; women who smoked a little, lower |
| 141,317 people, 23 studies [20] | Survey readings, most at a clinic visit | 2.4 points lower than never-smokers; less high blood pressure |
| Surveys in the US, South Korea and Scotland, and two US cohorts, pooled in 2026 [22] | A diagnosis, a treatment, or a reading over a set line | People who smoked only cigarettes: 1.25 times the odds of high blood pressure; in the cohorts, 1.20 times the rate of new cases. A side analysis; the review’s tables give no certainty grade for it |
| 4,786 young Americans, 30 years [21] | Clinic readings after 5 minutes’ rest | Systolic not significantly different from never-smokers’ |
| 59 smokers with untreated high blood pressure, against 118 non-smokers [24] | Clinic, then a cuff worn for 24 hours | Clinic 141 against 142; awake, 145 against 140 |
| 19 studies, pooled [25] | A cuff worn for 24 hours | About 3 points higher over 24 hours and in the daytime; no significant difference at night |
| 28,236 women, about 10 years [26] | New high blood pressure | 15 or more a day: 1.11 times the rate |
| 13,529 male doctors, 14.5 years [27] | New high blood pressure, from the doctors’ own reports | 1.15 times the rate |
| 3,296 Dutch adults, about 7 years [28] | New high blood pressure | 1.43 to 1.55 times the rate by their own report; 1.32 to 1.62 by a urine test |
What the doctor’s cuff can miss
Look at how those readings were taken. A clinic reading is taken after a rest, and the English survey left out anyone who had smoked in the past half hour [19]. US guidance tells everyone the same thing for a reading at home, as our page on measuring blood pressure at home explains. So the smoker’s reading is taken on a break from the thing being studied.
A cuff worn for 24 hours, which takes a reading every half hour or so through an ordinary day, does not wait. In 1991, 59 people with untreated high blood pressure who smoked were matched with 118 who did not. In the office their readings were nearly the same, 141 against 142 systolic; awake, out in their day, the smokers averaged 145 against 140, and in those over 50, 153 against 142 [24]. Asleep, the two groups did not differ [24]. A 2026 pooling of 19 studies found smokers’ 24-hour systolic pressure about 3 points higher than non-smokers’, with no significant difference at night [25]. We read that pooling only as its summary, because the full paper is behind a subscription, so we could not see which study in it is largest [25]. A reading that is normal at the clinic and high in daily life has a name, masked high blood pressure, and our page on white-coat hypertension covers its mirror image.
Does smoking cause high blood pressure over the years?
This is the claim as it circulates, and the evidence leans its way without settling it. Studies that follow people for years find modestly more new high blood pressure in smokers. They report it as a ratio: 1.11 means the smokers developed it about 11% more often than the comparison group over the same years. In 28,236 women followed for about ten years, smoking 15 or more a day went with 1.11 times the rate, and smoking fewer with no clear difference [26]. In 13,529 male doctors followed for 14.5 years, current smokers had 1.15 times the rate, though the doctors reported their own blood pressure readings [27]. In 3,296 Dutch adults followed for about seven years, the figure was 1.43 to 1.55 by what they said they smoked, and 1.32 to 1.62 by a urine test for nicotine’s breakdown product [28].
These are associations, which cannot by themselves prove that one thing causes another: smokers differ from non-smokers in drinking, diet, income and much else, and each study allowed for some of it. The smoking itself cannot be assigned at random for years. So researchers use a natural version: Mendelian randomisation, which compares people by inherited gene variants that change how much they smoke, variants handed out at conception regardless of anything else about their lives.
It gives two answers, depending on the variant. One variant makes smokers smoke more cigarettes a day. Among the 37,982 current smokers in the 141,317-person pooling, those carrying it had a higher resting heart rate, about 7 beats a minute for a 20-a-day smoker by the authors’ estimate, and no clear difference in blood pressure or high blood pressure [20]. The largest single study inside that pooling is Norway’s HUNT survey, by the authors’ account; on its own, in 56,625 people, the same variant went with lower body weight and higher heart rate, and the authors concluded that smoking “is not a major determinant of waist-hip ratio or adverse blood pressure”, among other things [29]. In the pooling’s own check, leaving HUNT out weakened even the heart-rate link until it could no longer be told from chance [20].
The other approach uses 361 variants linked to starting smoking at all. In UK Biobank, each step up in that inherited tendency went with 1.21 times the odds of high blood pressure [30], and a second analysis, which shares an author with the first and drew partly on the same UK Biobank data, called its similar finding “suggestive” [31]. But the first team’s own analysis of people who had never smoked found the link to high blood pressure there too, the one disease of the fourteen it studied where that happened [30]. A gene that raises blood pressure in people who never smoke is probably doing it some other way than through cigarettes. That reading is ours; the authors suggest secondhand smoke or people misreporting their smoking may explain weak links in never-smokers [30].
What happens if you stop smoking for 5 days?
The best answer is a 1999 Japanese trial, which ran a week. Forty-two healthy men who wanted to quit spent one week smoking as usual and one week not smoking, in random order; three went back to cigarettes, leaving 39 [32]. On the last day of each week they wore a 24-hour cuff. Without cigarettes, their 24-hour systolic pressure was 3.5 points lower and their daytime systolic 4.9 points lower; at night it did not differ significantly [32]. Their weight did not differ significantly between the two weeks [32]. A smaller British study of a week’s abstention found no significant fall [33].
A 2026 pooling of four studies that compared the same smokers’ 24-hour readings on and off cigarettes, 104 people in all, found the bottom number 2.67 points higher over 24 hours during smoking and heart rate about 6.5 beats higher; the top number was 2.41 points higher, which it could not tell from chance [34]. The largest study in it is the Japanese trial, and the pooling’s chart shows that trial’s systolic result as uncertain, where the trial’s own paper reports it as unlikely to be chance [34] [32]. The pooling worked out each study’s margin of error as if its smoking week and its non-smoking week came from different people, which widens it; that reading of the gap is ours [34]. Another study outside the pooling kept 24-hour records on days with and without nicotine, but it did not test that comparison. In the patch study above, the days on a dummy spray, with no nicotine, always came last, so the authors left them out of their statistical tests; by the study’s table, the 24-hour averages on those days were 113 over 62, against 117 over 65 on cigarette days [7]. What it did test was cigarettes against two nicotine medicines: in the 9 men with complete recordings, the top number did not differ significantly among the three, and the bottom number was slightly higher on cigarettes than on the patch [7].
How much can quitting smoking lower heart rate?
More reliably than blood pressure. In the week-long trial, heart rate over 24 hours was 7.3 beats a minute lower without cigarettes, 9.2 in the daytime [32]. In women past menopause who quit, the awake heart rate fell about 7 beats a minute in six weeks, against an average of zero in those waiting to start [35]. The genetic evidence agrees on this one: smoking more raised heart rate where it did not clearly raise blood pressure, though without the Norwegian survey the heart-rate link could no longer be told from chance [20].
Does quitting smoking lower blood pressure?
In the short run, through the day, it seems to. One trial randomly assigned 66 women past menopause to start a quit programme straight away or wait. After six weeks the 19 who had quit had awake systolic pressure 3.6 points lower, while the 15 still waiting were 1.7 points higher; their clinic readings did not differ significantly [35]. A 1985 controlled trial that used clinic readings found no significant rise in the 14 who quit for six weeks [36]. Among 19 heavy smokers who quit for six months and wore the 24-hour cuff, daytime readings went from 129 over 82 to 123 over 78 [37], and 72 people being treated for high blood pressure who quit during a trial of quit-smoking drugs went from 131 to 125 at the clinic in 12 weeks [38].
| Study | How long, and how it was read | What happened |
|---|---|---|
| 39 men, a week of each, in random order [32] | 1 week; a cuff worn for 24 hours | 3.5 points lower over 24 hours without cigarettes; 4.9 in the daytime |
| 66 women after menopause, randomised to a quit programme now or later [35] | 6 weeks; 24-hour cuff and clinic | Awake: down 3.6 in 19 quitters, up 1.7 in 15 controls. Clinic: no significant difference |
| 33 smokers in a programme, 33 matched controls [36] | 6 weeks; clinic | No significant rise in the 14 who quit |
| 19 quitters, 17 who kept smoking [37] | 6 months; 24-hour cuff | Quitters’ daytime readings 129/82 to 123/78 |
| 113 people treated for high blood pressure, in a quit-smoking drug trial [38] | 12 weeks; clinic | 72 quitters 131 to 125; no significant change in the 41 who did not quit |
| 37 daily users of snus or nicotine pouches who quit [16] | 12 weeks; home cuff | Up 3.7 points, with 4.0 lb (1.8 kg) gained |
| 255 people quitting, randomised to a weight-loss drug or a dummy injection; 218 analysed [39] | 1 year; clinic | Steady, with about 6.6 lb (3 kg) gained |
| 8,170 male steel workers [40] | 4 years; new high blood pressure | Quit 3 years or more: 3.5 times the risk of current smokers |
| 96,524 Korean adults [41] | About 7 to 9 years; new high blood pressure | Recent quitters 1.00 times current smokers’; long-term quitters 0.92 |
| 8 cohorts, 70,130 people, pooled [42] | 4 to 14.5 years; new high blood pressure | Quitters 1.08 times current smokers’, not significantly different |
Over years, the picture is mixed, and the bathroom scale is in it. Most people who quit put on weight. In a trial on our page on raising HDL cholesterol, quitters gained 10.1 lb over a year against 1.5 lb in those who kept smoking (4.6 kg against 0.7 kg); among 1,550 Swedish women who smoked, followed for about nine years, the 388 who quit gained 16.8 lb (7.6 kg) against 7.1 lb (3.2 kg) in those who kept smoking [43]. In a trial that randomly gave 255 people who were quitting either a weight-loss drug or a dummy injection, systolic pressure across the 218 with complete readings was, in the authors’ words, “stable over the period of 52 weeks after smoking cessation despite a weight gain of +3 kg”, about 6.6 lb [39].
Some long studies found more high blood pressure after quitting. Among 8,170 male steel workers followed by a Korean team, those who had quit for three years or more developed it at 3.5 times the rate of those still smoking, and the authors saw the same trend in men who kept their weight steady [40]. In a US heart-prevention trial of 3,470 men, 35% of quitters became hypertensive against 27% of those who kept smoking, and the authors put part of that down to weight, though quitting itself was not independently linked to a change in the bottom number [44]. The Swedish women who quit had 1.8 times the odds of high blood pressure of women who never smoked, against 1.3 for those who kept smoking [43]. Others found no rise: across 96,524 Korean adults, recent quitters developed it at the same rate as smokers and long-term quitters slightly less often [41], and a pooling of eight cohorts found no significant difference between quitters and smokers [42]. In 10,354 Japanese working men, quitters who gained 6.6 lb (3 kg) or more had 2.95 times the odds of developing high blood pressure of non-smokers who gained less, while quitters who gained less had about the same odds as those non-smokers [45].
So, for anyone wondering whether to expect a lower number after quitting: in daily-life readings, probably a few points lower within weeks; at the clinic, perhaps nothing the cuff can pick up; over years, it depends a good deal on what happens to your weight. None of these studies can tell you which of those will happen to you. A 1996 review that Google’s answer cites made the practical point: because blood pressure may rise after quitting, a quit attempt “should not postpone” treatment for someone who needs it [46].
If every cigarette raises blood pressure, why don’t smokers have high blood pressure?
This section is the desk’s own reasoning, and it is labelled as such. The experiments say each cigarette raises blood pressure. The surveys say smokers’ readings at the clinic are no higher, and in a 23-study pooling lower. Both can be true. Here are three reasons, each rated for how much evidence stands behind it.
Answer one: the cuff is read on a break. Clinic and survey readings are taken after rest, and in the English survey after at least half an hour without a cigarette [19]. The rise from one cigarette is largely gone within the hour [4]. When the cuff goes along for the day, smokers’ daytime readings run higher than non-smokers’ [24] [25], and the same men’s readings ran lower in a week without cigarettes [32]. That is measured, though the 19-study daily-life pooling we read only as its summary [25].
Answer two: smoking keeps weight off, and weight pushes the other way. The gene variant that makes people smoke more also went with lower body weight [29]; smokers’ lower readings in the big pooling shrank once weight was allowed for [20]; and quitters who gained 6.6 lb (3 kg) or more developed high blood pressure far more often than those who did not [45]. Each piece is measured. That the two pushes roughly cancel at the clinic is a surmise with those measurements on its side, not a result anyone has shown.
Answer three: the body may blunt the response with daily use. The 1988 experiment saw “evidence of development of some tolerance” with smokeless tobacco [9], and the 2026 review of snus says whether the blood-pressure response fades with daily use “remains unclear”, for lack of long studies of it [14]. This one is a surmise, with a hint in its favour and, by the review’s account, no long study that tested it in daily users.
Put the three together and here is what we think is true, stated plainly so you can disagree with it: smoking raises blood pressure while you are smoking and keeps your weight down while you are not, and the clinic sees the second and misses the first. Whether those daily spikes add up to lasting high blood pressure is the part nobody has settled.
What we could not find, and would like to: a study that follows people who quit with a 24-hour cuff for a year or more, weighing them as it goes. The longest in adults we found ran six months, with 19 quitters wearing the cuff [37] [13]. An Italian study put the cuff on 31 teenagers, aged 11 to 18, before a quit programme and after at least a year without cigarettes: their 24-hour systolic pressure went from 128 to 113, but it had no group that kept smoking to compare with, and it did not report their weight afterwards [47]. And a study that follows nicotine-pouch users for years. Two registered studies may answer part of that: a Swedish study of about 30,000 people that records whether they use tobacco snus or nicotine pouches and lists blood pressure at ten years among its outcomes, with no results yet, and a Swiss trial that offers smokers living with HIV a vape, nicotine pouches or patches and will measure blood pressure from six months to two years, still recruiting [13]. If you know of either, the corrections line on this site is open.
Where “smoking causes high blood pressure” came from
We could not trace who first said that smoking causes high blood pressure, as distinct from raising it for a while. The research behind the short-term rise is decades old [2]. The slide from one to the other is visible in a US heart association’s page, which says both “Smoking is a risk factor for high blood pressure” and “Blood pressure increases in the short term every time you smoke” [1]. A British blood-pressure charity sticks to the second: “Each cigarette you smoke causes a temporary rise in blood pressure” [1].
The retirees’ article Google cites carries the headline “Does Smoking Cause High Blood Pressure?” and the standfirst that it “may cause chronic hypertension”; further down, it allows that “even if smoking doesn’t chronically raise your blood pressure”, it can damage artery walls, in the view of a cardiologist it quotes [1]. A health insurer’s article says “More research is necessary to understand the full effects of smoking on blood pressure” [1]. The Dutch study above reached a medical news site under the headline “Link between smoking and high blood pressure confirmed” [48]; a link was what it measured, and a link is not a cause.
Then there are the sellers. A UK nicotine-replacement brand’s page answers “The short answer is, yes. The nicotine present when smoking is known to increase blood pressure”, says smoking raises it “in the short term and over a long period of time”, and carries buy buttons for its nicotine patch and lozenges [1]. A US brand’s page says “High blood pressure is a potential side effect of smoking. Nicotine in tobacco products causes your blood vessels to become narrower” and sells nicotine gum and patches [1]. Selling nicotine while blaming nicotine looks odd, but the trials are on the sellers’ side here: in one, a patch left the top number not significantly different from cigarettes and the bottom number lower [7]; in a trial of people quitting, blood pressure did not differ significantly between the patch and dummy treatment [10]; and gum raised it less than cigarettes [9]. Neither patch trial was free of company ties: a drug company supplied the first one’s patches and sprays, and one of its three authors was at that company; makers of quit-smoking medicines paid for the second [7] [10]. The fast nicotine of a strong pouch raised it [4].
None of this is aimed at anyone who smokes. If you smoke and have high blood pressure, the reading at the clinic may be the best number of your day.
Who these studies were done on
The experiments are small: 10 to 39 people each, healthy, and where ages are given, mostly in their 30s. The week-long Japanese trial was of men only; the German one was about half women [2] [32] [4]. The 24-hour studies that found the biggest daytime gaps included people with high blood pressure, and in the 1991 study the gap appeared in those over 50 and not in those under [24] [25]; that study’s summary says its finding applies among white patients [24]. The long studies are of women in one, male doctors in another, construction and steel workers, and Black and White young Americans [26] [27] [15] [40] [21]. The pouch studies on this page are of current smokers or Swedish snus users; none of them tested people who had never used nicotine [4] [5] [12].
What this is rated, and what the rating covers
Preliminary — for the claim that smoking causes high blood pressure, as it circulates.
It is rated Preliminary because the evidence in its favour is real but conflicting. Studies that follow people for years find modestly more new high blood pressure in smokers [26] [27] [28]; a 2026 pooling found more of it in people who smoked only cigarettes, in a side analysis its tables do not grade, where two cohorts agreed and the surveys differed from one another more than chance would produce [22]; and smokers’ readings through the day run a few points higher [25]. Against that, their clinic readings are no higher and in a 23-study pooling lower [20] [19]; the genetic test of smoking more did not support an effect on blood pressure [20]; and the genetic test of starting to smoke found its link in never-smokers too [30].
The narrower claims, rated in words. That each cigarette raises blood pressure for a while: Established, in sham-controlled and repeated experiments over five decades [2] [3] [8] [4]. That nicotine pouches raise blood pressure while one is in: Supported, in an independent study and a maker’s study, the rise largest with the strongest pouch in the independent one; a second maker’s study of pouches of 5.8 and 10.1 mg reported no clinically significant change [4] [5] [12]. That nicotine pouches cause lasting high blood pressure: Preliminary: we found no study that followed pouch users for that, and the nearest evidence, from tobacco snus, leans that way in two Swedish cohorts and in a Norwegian public-health assessment, while a pooling found no clear increase in Swedish users [15] [14]. That quitting lowers blood pressure: Preliminary: daytime readings fell within weeks in small studies, two of them randomised, while over years the weight most quitters gain pulls the other way and some cohorts found more high blood pressure after quitting [32] [35] [40] [43].
What is not rated here: whether smoking causes heart attacks, strokes or damaged arteries by routes other than blood pressure, which this page does not examine; secondhand smoke; cannabis; and the frame in the section above, which is this desk’s reasoning from the evidence rather than a result the evidence delivered. How we read a study, and what each tier means, is set out here.
This is journalism, not medical advice. If you smoke and have high blood pressure, talk to a clinician who knows your history; they can read your numbers in a way no page can. If you want help to stop, the US federal health agency’s free quitline is 1-800-QUIT-NOW (1-800-784-8669), as its own pages give it [49].
- Can High Blood Pressure Cause Headaches? At 180/120, Treat It as an Emergency. Below That, It Is a Poor Guide to Your Reading
preliminary - Vibration Plate Benefits: The Three Biggest Randomised Bone Trials We Found With Results, 1,086 People, Showed No Clear Gain. Stronger Legs Are Another Matter.
preliminary - Exercise for Osteoporosis: Lifting and Jumping Left Women About 1% Ahead on Bone Density, by Our Reading. Fewer Fractures Is Less Certain
supported