VO2 Max Test: The Cheap Estimates Sorted People Into Three Fitness Bands and Got It Right Half the Time

Somebody checked whether the cheap ways of working out your VO2 max actually work. They compared fifteen of them against the real thing, across 4,871 tests. [1]
The task was not even hard. Just sort each person into a fitness third — bottom, middle or top. Three buckets.
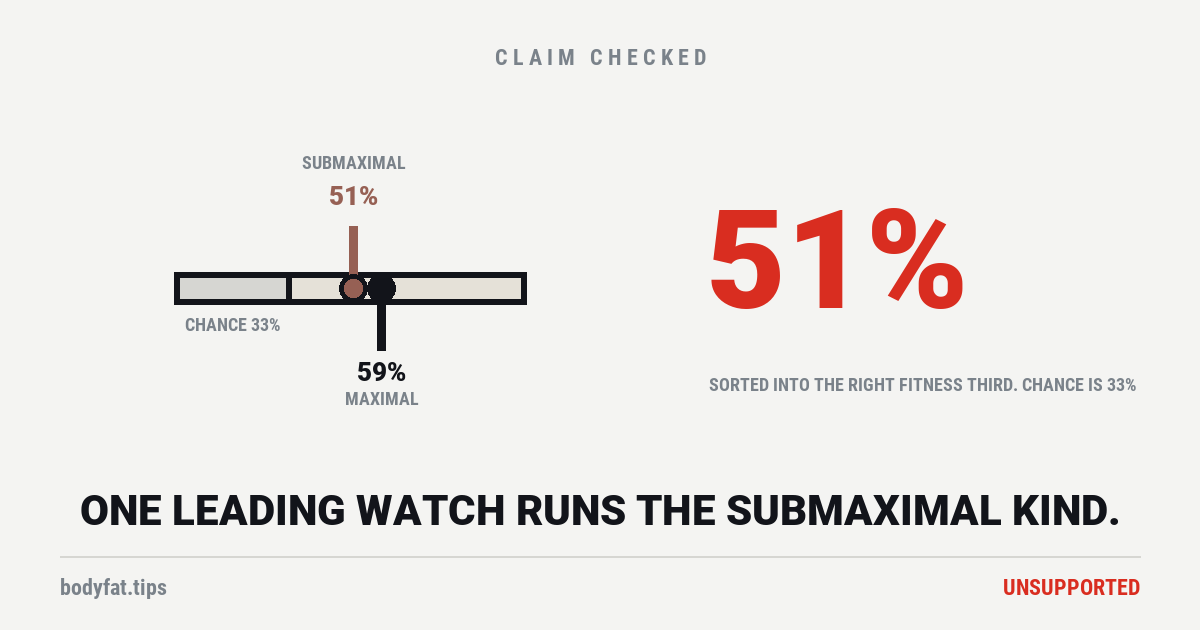
The submaximal equations got it right 51% of the time. The maximal ones managed 59%. [1]
Guessing gets you about 33%, because there are three buckets. So the cheap estimate is better than a coin toss and nowhere near a measurement, and the researchers say so in their own conclusion: “a low degree of accuracy in categorizing participants into fitness tertiles”. [1]
What a real VO2 max test actually is
A mask over your face, a treadmill or a bike, and a machine measuring the oxygen going in and the carbon dioxide coming out, breath by breath, while the effort is increased until you cannot continue.
VO2 max is the most oxygen your body can take in and use in a minute, per kilogram you weigh, flat out. The reason the test hurts is that the number is defined at your limit, so the only way to find it is to go there.
How does the lab know you actually got there? The standard check is the respiratory exchange ratio — the amount of carbon dioxide you breathe out divided by the oxygen you take in. At rest it sits near 0.8; once you are genuinely at your ceiling it goes above 1.0, and the large American reference database requires 1.0 or higher before it will accept a test as maximal. [3]
That criterion is the thing no estimate has. A formula cannot tell whether you truly emptied the tank. One built on an all-out test assumes you did; one built on an easier test assumes your maximum heart rate, usually predicted from your age [1].
The fifteen shortcuts, ranked
| Method | Sorted correctly | Range |
| Guessing (three bands) | ~33% | the floor |
| Submaximal exercise equations | 51% | 37–58% |
| No-exercise formulas (age, sex, weight for height; one adds activity and smoking) | 57% | two formulas |
| Maximal exercise equations | 59% | 43–76% |
| Directly measured, mask and gas analyser | — | this is the standard |
Notice the ranges. The best maximal equation got 76% and the worst got 43% — and unless you know which one your gym used, you do not know which of those you are holding. [1] Across all fifteen, the agreement statistic ran from 0.07 to 0.89, where 1.00 would be perfect. [1]
And the cheapest estimates of all held their own. The two formulas that need no exercise, only your age, sex and weight for height and, in one of them, how active you say you are and whether you smoke, sorted 57% of people correctly, between the two kinds of exercise equation. The researchers draw the conclusion themselves: in a clinical setting, exercise testing “does not provide enhanced accuracy compared with nonexercise equations” [1].
And the one on your wrist
Your watch runs its own formula. The maker of the watch in the checks below does not publish it [2], but describes the estimate as a submaximal prediction from your heart rate during outdoor walks and runs: it does not need you to go all out, but it does need an assumed maximum heart rate [11]. That is the same principle as the submaximal equations in the table.
When that watch was put against laboratory equipment in 19 people, it read 4.5 mL/kg/min low on average (the unit is millilitres of oxygen per kilogram of body weight per minute), with an average miss of 15.79% and a root-mean-square error, a measure that weighs big misses more heavily, of 8.85 mL/kg/min [2]. The authors read the result two ways: overall agreement “good”, and the reliability statistic, 0.47 where 1.00 would be perfect, “poor” [2]. They say their check cannot contradict the maker’s accuracy claim: each watch had only one outdoor walk and one run to go on, where the maker’s own validation followed people for more than a year. And their lab test, on a bike, stopped at exhaustion as each rider judged it, which they say may have read low [2]. Nineteen people is small, and the sibling page goes through that study properly, including the fair defence of it.
For scale: on the American reference table, a miss of 8.85 is enough to move a man in his forties from the middle of the pack (35.3) up to between the 70th and 80th percentiles, a bit more than half the way to the top tenth (50.8), or down to between the 10th and 20th [3].
Two larger checks since, of the same maker’s watches, mostly newer models, used a full treadmill test to exhaustion with the gas analyser. In 28 adults the watch read 6.1 low on average, and its average miss, high or low, was 6.9 [5]; in 35, it read 6.3 low and missed by 6.8 on average [6]. The second then asked this page’s question of the watch, against the same American reference table: it put 5 of the 35 people in their true percentile band, and 18 of them, about half, two bands or more out [6]. Those three checks were in young adults, with average ages of 23 to 32. A 2022 pooling of earlier checks of other makers’ devices found the ones that estimate from exercise right on average, but with 95 in 100 individual readings anywhere from about 10 below the lab’s to 10 above [7].
So do you need one?
Mostly no, and this is the part the answer turns on: what would you do differently?
The number is worth having when it changes a decision — a clinical assessment, a surgical risk workup, a serious training block built around measured thresholds. In clinical settings the researchers argue directly for the mask, because sorting people into risk categories on a formula that is right half the time is not good enough. [1]
Outside those settings, can an estimate at least show you a trend? That is the usual hope, and it has barely been tested. The idea is that a device wrong in the same direction every time still shows you a change. The four tests we found that followed people for weeks or longer and set a device’s change against the lab’s are small, and they do not agree. Over eight weeks of training in 20 college soccer players, an older heart-rate monitor’s estimate, taken from five minutes lying still [7], rose about as much as the lab result on average, but player by player the two changes barely matched [9]. Over twelve weeks of half-marathon training in 20 runners, another maker’s watch read high both times, and both averages rose by about 1 mL/kg/min (our arithmetic from the published averages); its published summary does not say whether individual changes matched [10]. The largest in healthy people, reported so far only as a conference abstract, followed 47 active-duty US Air Force personnel through 12 weeks of training: the laboratory measured an average gain of about 3.2 mL/kg/min, and neither of two other makers’ watches registered it, their average estimates moving by −0.13 and +0.19, even among the people whose laboratory value rose by 8% or more [12]. And in 48 adults with complex congenital heart disease, most of them wearing the watch in the checks above, the change on the wrist followed the change in the lab closely over a year or more, at about nine-tenths of it [8].
The authors of the newest check of that watch say its relationship with change over time “remains unclear” [6]. In two of the checks it read the fittest people further low than the rest, in subgroups too small to settle it [2] [6]. If that pattern is real, a genuine gain would show up smaller on the wrist than in the lab; that is our inference, not something the checks measured. What an estimate cannot do is tell you your percentile, and it cannot be compared against somebody else’s device.
And the thing that raises the number does not require knowing it. Training moves VO2 max, in trials of young adults, by about as much as one decade’s age group sits below the one before it in the US reference data, whether or not anyone measured you. Walking more is the version of this with the lowest barrier.
What the number is actually good for
The reason anyone cares is one of the largest associations in this field: an overview of 26 systematic reviews puts the risk of dying for high-fitness people at roughly half to three-fifths that of low-fitness people, across the eight reviews in it that looked at deaths (95 cohort studies between them) [4]. Those figures, hazard ratios of 0.47 to 0.59, compare how often people in the fitter and the less fit groups died over the years they were followed; they describe groups, not your own odds. The overview’s headline totals, 199 cohorts and 20.9 million observations, cover 21 outcomes, from deaths to new diagnoses. [4]
That evidence is observational, and its own reviewers grade the certainty from very low to moderate, mainly because most of the people studied were men. [4] In the data on deaths from any cause, about nine in ten of the people were men; the overview reports similar patterns in women, with a wider range of plausible answers because there were fewer of them [4]. Here is how we weigh that kind of evidence. It compares fitter people with less fit people; it does not promise that moving your own number buys you the difference.
Which is the useful way to end this. Fitness is a measurement you can change. Grip strength predicts a lot too; squeezing a gripper moves the reading, and we found no trial of grip training that set out to measure deaths or heart attacks. The measurement is optional. The training is the part that does anything.
Corrected on 30 September 2026. The closing paragraph said grip strength “does not respond to squeezing a gripper”. Our grip strength verdict, corrected today after an independent editorial review, says the opposite about the reading itself: squeezing does move it. What nobody has tested is whether moving it lowers the risk it predicts. The sentence now says that. Nothing else on this page changed.
Corrected again on 30 September 2026. Our earlier note today said nobody has tested whether moving grip strength lowers the risk it predicts. That was broader than the search behind it. Our grip strength verdict, corrected a second time today, found no trial of grip training that counted deaths or heart attacks (searched 30 September 2026), which is a narrower thing to say, and the closing sentence now says it. Nothing else on this page changed.
Corrected on 9 October 2026 after an independent editorial review. The wrist section called 8.85 mL/kg/min the watch’s “typical error” and said the authors classed its agreement as poor. In that study 8.85 is a root-mean-square error, which weighs big misses more heavily, and the watch read 4.5 low on average; the authors called overall agreement good and the reliability statistic, 0.47, poor, and said their one-session check could not contradict the maker’s accuracy claim. The page now says so and adds two larger checks since, in which the watch read about 6 low on average and put 5 of 35 people in their true fitness band. Our scale comparison was also wrong: on the reference table we link to, a miss of 8.85 moves a man in his forties a bit more than half the way from the middle to the top tenth, not all of it.
Also corrected: the mortality sentence and the evidence panel gave the overview’s totals for all 21 outcomes; the death figures come from eight of its reviews, 95 cohorts, and range from roughly half to three-fifths, in data that were about nine in ten men. The funding row said funding was not stated in the sources read; three of the four sources state it, one naming a company, and the row now describes each source by role. The equation table now includes the two formulas that need no exercise, which sorted 57% correctly. The advice that a consistently wrong device still shows you a change was our own reasoning and cited no test; the page now reports the four small tests of change we found, which disagree. The researchers’ call for the mask was for clinical settings only; the watch’s formula is now described as its maker describes it; the provenance chain now starts from the maker’s own white paper; and the closing grip sentence, which our second note of 30 September said had been narrowed and which had not been changed, now says less than that note did, because a 2026 trial of grip exercise in people with advanced kidney disease recorded a death, as our grip strength verdict, corrected on 7 October, explains. The closing paragraph also no longer calls fitness one of the few measurements you can change. The provenance chain’s search figure now says where it came from and when we pulled it. The rating is unchanged.