White Coat Hypertension: In Four Studies, High Blood Pressure or Pills for It Followed Roughly Twice as Often. The Death Risk Is Unsettled.

Your blood pressure is high at the doctor’s and normal at home. Is that nerves, or a warning? You can find both answers from respectable places. A hospital system’s patient page tells readers “you may just be nervous about being in the doctor’s office” [1]. A university medical centre announced in 2019 that people with untreated white-coat hypertension were “twice as likely to die from heart disease” [2].
Plenty of people are asking. The keyword database reports about 27,100 searches a month in the United States for “white coat hypertension”, the same figure for “white coat syndrome” and for “white coat effect”, because it counts the three phrases together as one search, so the figures are not added up here (from a paid keyword database, pulled 10 October 2026) [3].
Two words first, because everything below is measured in them. Blood pressure comes as two numbers: the top one, systolic, is the pressure while your heart pushes, and the bottom one, diastolic, is the pressure between beats. Both are in mmHg, millimetres of mercury, the unit on every monitor.
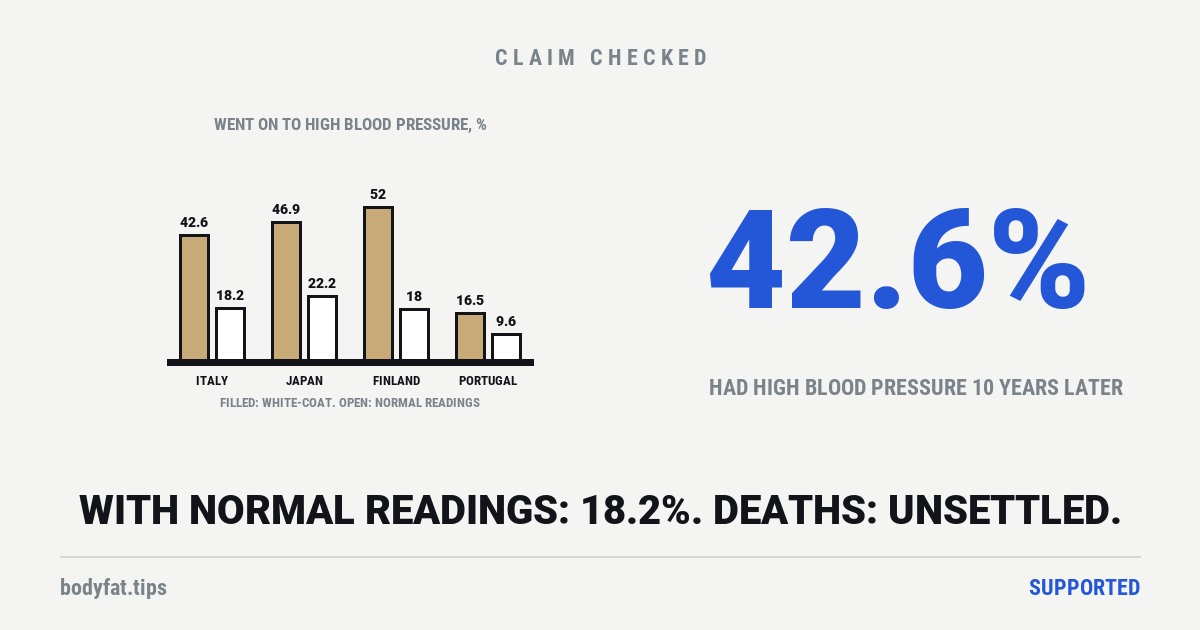
It is not just nerves, and it is not a disaster. In three population studies in Italy, Japan and Finland, 43% to 52% of people with white-coat hypertension had high blood pressure outside the clinic eight to eleven years later, or, in two of the three, had started pills for it, against 18% to 22% of people whose readings had been normal everywhere [4] [5] [6]. A fourth study, in a Portuguese clinic with a stricter definition, found the same tilt at lower rates. Across the four, it came 1.7 to 2.9 times as often, by our arithmetic on their shares [7].
The link to heart attacks and strokes is weaker, and the death risk is unsettled. Pooled across eight cohorts in 2019, untreated white-coat hypertension went with about a third more heart attacks, strokes and other cardiovascular events [8]. On deaths, the biggest study behind the scary headline was retracted by its own authors in 2020, for errors in its data and analyses [9]. The same registry’s 2023 analysis found no clear extra risk of death [10] [11], while the longest study on this page, of an Italian town followed for 29 years, found about twice the rate of deaths from cardiovascular disease in people with no sign of harm to the heart or kidneys [12].
No trial we found was designed to test whether blood-pressure pills for it prevent heart attacks, strokes or deaths. The nearest thing is a group of 167 people inside a placebo-controlled trial from 2000, which counted six cardiovascular events on placebo and two on the drugs, too few to tell from chance [13]. The one trial we found that set out to answer the question, in the UK, never randomised anyone [14] [15].
What is white coat hypertension?
A high reading at the clinic, with normal readings everywhere else, in someone who is not taking blood-pressure medicine. The European hypertension guidelines of 2023 define it that way, and add a second term: the white-coat effect, the gap between a high clinic reading and a lower one at home or over 24 hours [16]. Anyone can have the effect. In people already on medicine, the 2025 US guideline calls a high clinic reading with normal readings outside a white-coat effect, and keeps the word hypertension for the untreated [17].
Where the lines sit depends on the guideline. The 2024 European cardiology guidelines give 140/90 or more at the clinic with under 135/85 at home or by day, or under 130/80 averaged over 24 hours, as their example [18]. The 2025 US guideline counts readings outside the office as high from 130/80 by day, or 125/75 averaged over 24 hours [17].
“Outside the clinic” means one of two things. A home monitor, which you use yourself; or a 24-hour monitor, a cuff worn through the day and night that takes a reading by itself, typically every 20 to 30 minutes [19]. The reverse pattern, normal at the clinic and high outside it, is called masked hypertension, and it has its own section below.
How common is white coat hypertension?
Common, though the share depends on who is counted and where the lines are drawn. A 1988 study asked the question in its title, “How common is white coat hypertension?”: of 292 untreated people with borderline clinic readings, 21% had normal readings during the day on a 24-hour monitor; we read it as its summary [20].
Spain keeps a national registry of patients sent by their family doctors for 24-hour monitoring. Among the untreated patients with a high clinic reading, 41% had normal daytime readings, 35% a normal 24-hour average, and 26% normal readings by day, by night and over 24 hours, with similar shares in treated patients; we read that study as its summary [21]. The European guidelines put it at up to 30% to 40% of people with a high clinic reading, and over half in the very old [16]; in a trial of people over 80, half of those monitored met the criteria [22].
Across all adults the share is smaller, because most adults do not have a high clinic reading to begin with. The 2017 US guideline put the average at about 13%, and as high as 35% in some groups with high blood pressure [23]. The US Preventive Services Task Force, citing international cohorts, estimates 8% [19].
How high can blood pressure go with white coat syndrome?
Higher than most people would guess, for a few minutes. In 1983 an Italian team recorded blood pressure continuously through a fine tube in an artery while a doctor came to the bedside and took readings with a cuff. In 48 people, the doctor’s arrival pushed the top number up by 26.7 points on average at its peak, one to four minutes in, and by anything from 4 to 75 points depending on the person; it then eased off; we read it as its summary [24]. In a later study by the same group, the rise was 46.7% smaller when a nurse took the reading instead of a doctor; we read that as its summary too [25].
Across a whole visit the gap can still be large. In 112 people over 80 in a drug trial, the clinic top number averaged 36 points above the daytime average from a 24-hour monitor, and the gap ran from 13 points below to 73 points above across the group [22].
None of that makes a very high clinic reading safe to ignore. The 2025 US guideline says adults with a clinic reading of 160/100 or more should be treated promptly [17], and the European cardiology guidelines say a screening reading above 160/100 is almost always high blood pressure, while a small number of people have extreme white-coat effects that call for a prompt repeat reading [18].
How serious is white coat hypertension?
Through the 1990s and 2000s, the outcome studies mostly said: not very. A 1994 Italian study counted heart attacks, strokes and other cardiovascular events over an average of 3.2 years: 0.49 per 100 person-years in people with white-coat hypertension and 0.47 in people with normal readings; we read it as its summary [26]. Two poolings of studies agreed: seven studies gave a hazard ratio of 1.12 in 2007 [27], and eight studies of untreated people gave 0.96 in 2011 [28]; we read both as their summaries.
A hazard ratio compares how often something happens in two groups over the same time: 1.12 means 12% more often, 0.96 means 4% less often. Each came with a confidence interval, the range the true answer probably sits in, and both ranges included 1, so “no difference at all” was still on the table [27] [28].
Then the studies got bigger and longer. In 2019 a pooling of 27 studies, following people for 3 to 19 years, split them by whether they were already on blood-pressure medicine [8]. In untreated people, white-coat hypertension went with a hazard ratio of 1.36 for heart attacks, strokes and other cardiovascular events, with a range from 1.03 to 2.00: about a third more often [8]. Eight studies fed that number. The biggest by far was the Spanish registry’s 2018 analysis, since retracted (see below), and leaving it out still gave 1.29 [8] [29]. A 2017 pooling found much the same, 38% more cardiovascular disease in untreated people; we read it as its summary [30].
Deaths made the headline. The 2019 pooling put deaths from any cause 33% higher, and deaths from cardiovascular disease at 2.09 times the rate, which became the press release’s “twice as likely to die from heart disease” [8] [2]. But the death figure leaned on one study: of the five pooled for deaths from any cause, only the Spanish registry’s result was clear on its own; the other four leaned the same way, none of them clearly [8]. The 2.09 pooled three studies, and most of its weight, about 85% by our arithmetic from the pooling’s own chart, came from the registry’s analysis: the other two were small, an earlier report from the Monza study and a Taiwanese cohort of 1,257 people [8] [29]. The registry’s analysis is the one its authors later retracted.
All of these are cohort studies: they follow people over years and compare who falls ill. They show what goes with what. They cannot show that the clinic reading itself does the harm, because people with white-coat hypertension differ in other ways too, and the studies could adjust only for what they measured; the 2019 authors list that among their limits [8].
Does white coat hypertension shorten your life?
This is where the story turned, and the first turn did not stand. The Spanish registry behind the biggest number was analysed twice. Its 2018 analysis, in a leading medical journal, reported more deaths in untreated white-coat hypertension than in untreated people with normal readings, and called the condition not benign. In January 2020 its authors retracted it, writing that they had “identified inaccuracies in the analytic database and data analyses” [9]. Its figures are not used on this page.
In 2023 several of the same authors published a new analysis of the same registry, of patients recruited from 2004 to 2014, now 59,124 of them followed for a median of 9.7 years, and it gave a different answer. Untreated people with white-coat hypertension died at 0.88 times the rate of untreated people with normal readings, with a range from 0.75 to 1.03, which leaves no clear difference in either direction; for deaths from cardiovascular disease alone it was 0.98 [10]. Across all patients, treated or not, the ratio was 0.90; when the authors removed people in the normal group whose bottom number was under 70, which they suggest can be a sign of illness already present, it was 1.04 [10].
The 2023 paper does not cite the 2018 one or mention its retraction; we read its full text and reference list [10]. So the two answers cannot be read as a short look and a longer one: the first was withdrawn by its own authors for errors in its data and analyses [9], and the second is the registry’s analysis that stands.
In 2025 the team behind the 2019 pooling ran its death analysis again, with the 2023 registry figures in place of the 2018 ones. Deaths from any cause in untreated white-coat hypertension came to 1.08, a range from 0.91 to 1.36; cardiovascular deaths to 1.06, a range from 0.68 to 4.83; we read its first page and its chart, not its full text [11]. Leave the Spanish registry out and the other four studies came to 1.19, a range from 1.02 to 1.41 [11]. The team’s own account of the 2019 signal is that it was “likely driven by missed transition of patients with WCH to sustained hypertension over time”: people whose white-coat hypertension turned into high blood pressure everywhere, and was not caught [11].
The longest follow-up on this page points the other way. An Italian study drew a random sample of adults aged 25 to 74 in the town of Monza, the study behind the Monza row in the progression table below, and followed 1,423 of them for a median of 29 years [12]. Among people with no sign of organ damage, meaning no thickened heart muscle on an ultrasound scan and no reduced kidney filtration on a blood test, those with white-coat hypertension died of cardiovascular disease at 2.0 times the rate of people with normal readings, with a range from 1.1 to 3.6, after allowing for age, sex, obesity, cholesterol, diabetes, smoking and blood-pressure medicine. For deaths from any cause the figure was 1.2, with a range from 0.9 to 1.5, which leaves no clear difference; the study’s summary says the excess held for deaths from any cause as well, and the 1.2 is the figure in its own chart [12]. Three fences. It counted white-coat hypertension by the looser line, a 24-hour average under 130/80 or a home average under 135/85, and its group with no organ damage also left out anyone who had already had a heart attack, stroke or other cardiovascular event; the stricter line, as Answer one says, picks out people at less risk [12]. It is one town, with 276 people in that white-coat group, and about one in five of them were already on blood-pressure medicine at the start, so they were not all untreated; and that group averaged about ten years older than the normal-reading group, which the analysis adjusted for [12]. The 2025 update pooled this study’s earlier, shorter report, not this one [11].
Two honest readings of that, and the evidence does not choose between them. Either the 2019 death signal rested largely on an analysis that no longer stands, and the registry’s 2023 analysis, from a group far larger than the other cohorts pooled with it, is the better guide [9] [10]; or the smaller cohorts, drawn mostly from the general population and some followed for much longer, see a real excess that a registry of people sent for a test misses: leave the registry out of the 2025 update and deaths from any cause came to 1.19, and the Monza study found about double the deaths from cardiovascular disease [11] [12]. The 2023 authors note that their normal-reading group, being people sent for a test, was not necessarily healthy [10].
Does white coat hypertension turn into high blood pressure?
More often than normal readings do, and this is the most consistent finding on the page. Doctors call high blood pressure at the clinic and outside it sustained hypertension. Four studies have followed people with white-coat hypertension for years to see how many got there.
| Where, and how long | White-coat hypertension | Normal readings | Did starting medicine count as going on to it? |
|---|---|---|---|
| Monza, Italy, 10 years [4] | 42.6% of 225 | 18.2% | Not stated in the summary |
| Ohasama, Japan, 8 years [5] | 46.9% of 128 | 22.2% of 649 | Yes |
| Finland, a national sample, 11 years [6] | 52% of 142 | 18% of 528 | Yes |
| A Portuguese clinic, about 7 years; normal night readings also required [7] | 16.5% of 399 | 9.6% of 344 | No: treated people kept separate, judged on a 24-hour monitor |
In Monza, Italy, 225 people with white-coat hypertension were measured again ten years later: 42.6% had high blood pressure at the clinic and outside it, against 18.2% of people whose readings had been normal; we read this study and the three below as their summaries [4]. Whether that analysis left out people already on blood-pressure medicine, its summary does not say; in the same study’s 2022 report, about one in five of the white-coat group without organ damage were on it at the start [12]. In Ohasama, Japan, over eight years, 46.9% against 22.2% [5]; across Finland, over eleven years, 52% against 18% [6]. In a Portuguese clinic, where white-coat hypertension had to come with normal readings at night as well, 16.5% against 9.6% over about seven years [7]. We read all four as their summaries. A 2019 pooling of three cohorts of people untreated at the start, two of them the Japanese and Finnish ones above, put the risk at 2.85 times that of normal readings, with a range from 2.32 to 3.49; those two carry 97% of its weight by its own chart, so it adds little beyond them [31].
The guidelines act on it. The 2017 US guideline put the rate of conversion at 1% to 5% a year, and said periodic home or 24-hour monitoring is reasonable to catch it [23]. The 2025 US guideline says the same, and notes that the studies looked again only once, seven to eleven years later, so how often to check is unclear [17].
Is white coat syndrome dangerous for everyone?
“Is white coat syndrome dangerous” is searched about 210 times a month in the US (from a paid keyword database, pulled 10 October 2026) [3]. The answer depends on who is asking.
An international database matched 653 untreated people with white-coat hypertension to 653 people with normal readings, of the same age and from the same cohorts, and followed them for a median of 10.6 years. The extra risk of cardiovascular events showed only in people already at high risk, from several risk factors, diabetes or past heart disease: a hazard ratio of 2.06, and 2.19 in those aged 60 or more. In low-risk people it did not show; in older low-risk people the ratio was 0.88. The authors’ summary is that risk in “most persons” with white-coat hypertension is “comparable” to people with normal readings of the same age and risk; we read it as its summary [32].
The 2019 pooling saw the same tilt: in studies whose average age was under 55, the ratio was 1.21, at the edge of chance, a range from 1.00 to 1.51 [8]. The 2025 US guideline sums the field up as anything from “no risk to a moderately increased risk”, possibly raised only in “older adults who have high baseline CVD risk” [17].
And if you already take blood-pressure medicine? Then a high clinic reading with normal home readings is a white-coat effect, and in the poolings it carried no clear extra risk compared with people whose readings were normal or controlled: 1.12 for cardiovascular events in 2019, 0.93 for deaths in 2025 [8] [11]. A database of home readings found the same pattern: 1.42 for untreated white-coat hypertension against normal readings, and 1.16, within chance, for treated people against treated people whose readings were controlled; we read it as its summary [33].
That is not the same as no risk. In an international study of older people with high top numbers, treated people with a white-coat effect and treated people whose readings were normal everywhere both had about twice the risk of untreated people with normal readings; we read it as its summary [34].
Can white coat hypertension be cured?
Not in the sense of going away for good, and the label itself is unsteady. The European guidelines say the diagnosis reproduces poorly, so it should be confirmed by repeated readings at the clinic and outside it [16]. The reaction did not fade with familiarity in the 1987 study: over two days, three more visits by the same doctor raised blood pressure as much as the first [25]. In 1,096 Italians aged 18 to 45 with mildly raised clinic readings, white-coat hypertension found at the first check was still there three months later in only a third. Over 17.4 years it predicted high blood pressure needing treatment only when it had been found both times, a hazard ratio of 1.50 against people with normal readings; found once, it could not be told apart from chance, in a group of whom 80.5% went on to need treatment anyway [35]. What matters over the years is the reading outside the clinic, which is why the guidelines ask for it to be checked again [23] [17].
How do you fix white coat hypertension?
You change who measures, and where. A nurse’s reading raised blood pressure less than a doctor’s in the 1987 study [25]. In a 2011 Canadian trial, 67 family practices were assigned by chance either to keep measuring by hand or to switch to an automatic monitor that takes several readings while the patient sits alone in the room; 555 patients took part. Against each patient’s daytime average on a 24-hour monitor, the automatic readings ran 2.3 points high and the hand-taken ones 6.5 [36].
And you measure outside the clinic. The US Preventive Services Task Force recommends readings outside the clinical setting to confirm high blood pressure before treatment starts, at its top grade [19]. The European cardiology guidelines say a screening reading of 140 to 159 over 90 to 99 should be confirmed outside the office [18], and the 2025 US guideline says it is reasonable to rule out white-coat hypertension that way for adults with a clinic reading of 130/80 or more [17]. How to take home readings that are worth having, from cuff size to where your arm rests, is its own verdict on this site.
One more use for the distinction, when you judge a remedy: ask where its trials took their readings. Our beetroot juice verdict found resting readings about 3.5 points lower, while three reviews that pooled 24-hour readings reported no significant change. Our lifestyle verdict reports a kiwifruit trial in which the 24-hour pressure fell and the clinic readings did not differ. The same question is worth asking of the trials behind hibiscus tea.
White coat hypertension treatment: do pills help?
“White coat hypertension treatment” is searched about 210 times a month in the US (from a paid keyword database, pulled 10 October 2026) [3]. Whether pills help has not been tested in an outcome trial designed for it that we found, and the guidelines say so. The 2017 US guideline: “There are no data on the risks and benefits of treating white coat and masked hypertension” [23]. The 2025 one: “scarce data” on the risks of not treating it [17]. The European guidelines: “no specific outcome-based trial has been performed”, and drugs “may be considered” for people with organ damage, meaning harm to the heart, kidneys or arteries already showing on tests, and a high cardiovascular risk [16]. The US task force calls the question “a critical evidence gap”, and lists “Does treating white coat hypertension cause harms?” among its open questions [19].
Here is what the trials that looked at it show. In a placebo-controlled trial of people aged 60 or more with high top numbers, 695 wore a 24-hour monitor at the start, and 167 of them, about a quarter, had a daytime top number under 140. In those 167 the drugs brought the clinic reading down; their readings outside the clinic did not fall significantly within the treated group, and differed from placebo only on the daytime top number. The drugs cut strokes significantly only in the group whose daytime top number was 160 or more; cardiovascular events as a whole fell most in that group too, just short of the line researchers use for “probably not chance” [13]. The authors note that the events among the 167 were few: in their chart, cardiovascular events numbered six on placebo and two on treatment, and strokes two and none, differences that could be chance. The 167 were not randomised as a group of their own: the whole trial was randomised, and people were sorted afterwards by their 24-hour readings [13]. A 2021 review counts the same six and two, and says the small numbers make the trial’s negative conclusion weak [37].
In a trial of people over 80, half of the 112 monitored at the start met the criteria for white-coat hypertension. Across the substudy the drugs lowered the 24-hour average by 8/5 against placebo, and the main trial cut deaths and strokes, so its authors argue the condition “may benefit from treatment in the very elderly”, and call for a randomised trial to settle it [22].
In two trials that recorded both kinds of reading, the drugs did something odd in white-coat hypertension: they lowered the clinic reading about as much as in anyone, and not the 24-hour one. Over four years in 251 people with white-coat hypertension, the clinic top number fell 19.1 points while the 24-hour average edged up 1.6 [38]. In a second trial of 470 people, a quarter of them with white-coat hypertension, the clinic readings fell and the 24-hour readings did not [39]. The large US trial that pushed treated pressure lower, SPRINT, measured how common the white-coat effect was under treatment, about one in five of those still above their clinic target, but did not report outcomes by it [40].
And the trial that set out to answer the question never got going. A UK study registered in 2018 planned to assign 100 people over 75 with white-coat hypertension to two blood-pressure drugs or to no treatment. Its 2021 report: of 104 people approached, 10 consented, all failed screening, and “nobody was randomised” [14]. The team’s 2024 paper on why, which we read as its summary, lists among the reasons how family doctors already handle white-coat hypertension in older people, the study’s complexity, and the difficulty of finding eligible patients in practice records [41].
Whether to treat raised blood pressure, yours, belongs with a clinician who has your readings and your other risks in front of them.
What is masked hypertension?
The reverse: normal at the clinic, high outside it. It is searched about 720 times a month in the US (from a paid keyword database, pulled 10 October 2026) [3]. It is the more worrying of the two, because a clinic reading cannot find it. In the 2023 Spanish registry analysis, people with masked hypertension died at 1.24 times the rate of people with normal readings, and from cardiovascular disease at 1.37 times, about the same as people high in both places [10]. The 2017 US guideline put its risk at about twice that of people with normal readings, and its share at 10% to 26% in population surveys [23]. Screening that starts with a clinic reading misses it, the US task force notes [19].
If the clinic reading is the misleading one, why does it predict anything?
This section is the desk’s own reasoning, and it is labelled as such. The name says the high reading is a product of the clinic. Yet people with it went on to high blood pressure more often [4] [5] [6] [7], and in the poolings had more heart attacks and strokes [8]. Three answers of our own, each rated.
Answer one: the home number was not as normal as it looked. In the Italian study, people with white-coat hypertension averaged 119.4 on the top number over 24 hours against 112.3 for people with normal readings, and 127.2 at home against 110.5 [37]. In the Spanish registry’s 2023 analysis, across all patients, treated or not, the 24-hour averages were 119/70 against 116/70 [10]. And when the Spanish registry used its strictest definition, normal by day, by night and over 24 hours, those patients showed no significant difference from people with normal readings in their other risk factors and organ damage; we read that study as its summary [21]. And where the line is drawn matters: in an Italian study begun in 1986 and followed for 10.4 years, white-coat hypertension with a 24-hour average under 125/75 carried a hazard ratio of 0.94 for major cardiovascular events, and defined by the looser line of 130/80 it was 1.79, with a range from 1.07 to 2.99 [42]. This is measured: “normal” outside the clinic is a range, and white-coat hypertension tends to sit near its top.
Answer two: part of the “progression” may be the prescription pad. Two of the four progression studies counted starting blood-pressure medicine as progressing [5] [6], and a high clinic reading is what prompts a prescription; the 2011 pooling noted that people with white-coat hypertension were more often on medicine at follow-up [28]. But the Portuguese study, which kept treated people separate and judged progression on the 24-hour monitor, still found it, 16.5% against 9.6% [7]. That the designs inflate the figure is our reading of their methods; how much is a surmise; that it is not all of it has one study on its side.
Answer three: age changes what the label means. The gap between clinic and daytime readings grows by about 3.8 points a decade [32]; over 80, half of a trial’s patients met the criteria [22]; and the excess of events showed in older people at high risk [32]. A 40-year-old with a nervous reaction and an 80-year-old whose clinic reading runs 36 points above the day’s average may share a label and little else. The age gradient is measured; the conclusion that the label means different things at different ages is ours.
Put the three together and here is what we think is true, stated plainly so you can disagree with it: a white-coat reading is neither a diagnosis nor an all-clear; it is the first reading in a series that only measurements outside the clinic, repeated over the years, can finish.
What we could not find, and would like to: a trial that assigned people with white-coat hypertension, confirmed at home and on a 24-hour monitor, to blood-pressure pills or to monitoring alone, and counted heart attacks, strokes and deaths [15]. The only attempt we found, for people over 75 in the UK, randomised nobody [14]. If you know of that trial, the corrections line on this site is open.
Who these studies were done on
Mostly middle-aged and older adults in Europe and Asia. The 2019 pooling’s studies had average ages from 43 to 72; two of its 27 were in North America, and few reported race or ethnicity [8]. The Spanish registry is primary-care patients sent for a 24-hour monitor, average age 58.7, predominantly White by its authors’ account [10]. The progression studies were of townspeople aged 25 to 74 in Italy [37], a Japanese town’s population, a national Finnish sample and a Portuguese clinic [5] [6] [7]. The treatment evidence comes from people over 60 and over 80 [13] [22].
Two things change the answer for a reader. Age, as Answer three sets out: the excess of events showed in older people at high risk [32], and in people under 45 a single finding of white-coat hypertension did not clearly predict later high blood pressure [35]. And treatment: everything about white-coat hypertension on this page is about untreated people unless it says otherwise. White-coat hypertension in pregnancy and in children are separate questions, not covered here.
Where “just nerves” and “twice as likely to die” came from
The doctor’s effect was measured before most of the outcome studies existed. In 1983 the intra-arterial study above put a number on the doctor’s effect: 26.7 points on the top number, on average, at its peak within minutes [24]. In 1988 a New York team asked how common it was and found 21% [20].
Whether it mattered was argued from the start. A 1993 study of 67 older people’s hearts asked in its title “Is white coat hypertension innocent?” and concluded it “may not be innocent”; we read it as its summary [43]. The 1994 outcome study found event rates about the same as normal [26], and the poolings of 2007 and 2011 agreed [27] [28]. By 2013 the authors of the over-80s substudy could write that it “is considered to be a benign condition that does not require antihypertensive treatment” [22], and a 2021 review describes no-greater-risk as the opinion that prevailed “for several years” [37]. We could not find who first called it harmless in so many words; in the journals the word was “benign”, or “innocent” with a question mark [15].
Then the reversal, in words firmer than later evidence bore out. In 2018 the registry’s first analysis called white-coat hypertension not benign, in a paper its authors retracted in 2020 [9]; in 2019 a press release said “twice as likely to die from heart disease”, announcing a pooling that included that analysis [2]. The registry’s 2023 analysis and the 2025 update reached a different answer on deaths [10] [11], and the Monza study’s 29-year report found about double for deaths from cardiovascular disease and no clear difference for deaths from any cause [12].
Both versions are still in circulation. A prescription-savings company’s blog, last updated in June 2023, says “For many years, doctors shrugged off the in-office spike in blood pressure to nerves” and repeats the “twice as likely to die from heart disease” line [44]. A medical school’s health publication asks whether the spikes are “just harmless blips” or something more concerning [45]. Ask Google in October 2026 and its AI answer says people with it “have a higher relative risk of developing sustained, long-term high blood pressure” [3]. A UK family doctor’s video, “Don’t Fall For The White Coat Blood Pressure Trap”, posted in May 2026, had 363,531 views when we read its page [46].
And what is sold is the measurement. The video’s description carries an affiliate link to a home blood-pressure monitor on a large online retailer; we did not follow the link and do not know which model it is [46]. Every guideline on this page asks for readings outside the clinic; whether a given monitor is a validated one is a separate check, set out in our measuring verdict.
None of this is aimed at anyone whose numbers jump at the doctor’s. The jump is real, it can be measured, and it is not a failing. It is the confident versions, “just nerves” and “twice as likely to die”, that the evidence does not carry.
What this is rated, and what the rating covers
Supported — for the claim that untreated white-coat hypertension is a warning sign: people who have it develop high blood pressure outside the clinic more often than people whose readings are normal everywhere.
It is rated Supported because four cohorts in four countries, followed for seven to eleven years, all found it in the same direction: 43% to 52% against 18% to 22% in the three population studies, and 16.5% against 9.6% in the clinic study with the strictest definition [4] [5] [6] [7]; a 2019 pooling of three cohorts, two of them among these four, gave 2.85 times the risk [31]; and the US guidelines act on it [23] [17]. It is not Established because these are cohort studies, each measured people once at the start, two of the four counted starting medicine as progressing, and we read all four as their summaries [5] [6]. It has a fence, too: in adults aged 18 to 45 with mildly raised clinic readings, a single finding of white-coat hypertension did not clearly predict later high blood pressure; a finding confirmed three months later did [35]. And whether the Monza analysis included people already on medicine, its summary does not say [4] [12].
Rated alone, in words. That white-coat hypertension is harmless, just nerves: Unsupported, of the tested kind. It was tested in cohorts, and as a blanket claim it did not hold up: in four cohorts people with it went on to high blood pressure more often [4] [5] [6] [7], and in the Monza study, followed for 29 years, those without organ damage died of cardiovascular disease at about twice the rate of people with normal readings, and over ten years 34.1% of them, against 14.9% with normal readings, developed high blood pressure outside the clinic, whether or not their clinic readings were high too [12]. What survives is narrower: in a matched analysis, younger and lower-risk people showed no clear excess of events, and the 2025 pooling found no clear rise in deaths [32] [11].
That untreated white-coat hypertension raises the risk of heart attacks and strokes: Preliminary; eight pooled cohorts found about a third more, but in a matched analysis the excess was confined to older, higher-risk people, and cohorts cannot separate the clinic reading from the slightly higher readings outside it that come with it [8] [32] [37].
That people with untreated white-coat hypertension are twice as likely to die from heart disease: Preliminary. The 2.09 behind the headline pooled three studies, one of them the registry analysis its authors retracted [8] [9]. With the registry’s 2023 analysis in its place, the same team’s 2025 update put it at 1.06, with a range from 0.68 to 4.83, too wide to rule a doubling in or out [11]; the registry’s own 2023 figure was 0.98 [10]; and the Monza study found 2.0 after 29 years in people without organ damage, about a fifth of them on medicine [12]. Real studies, pointing different ways: not enough to settle it.
That white-coat hypertension is real and common: Established; it has been measured for four decades, at about a fifth to two-fifths of people with a high clinic reading in the registries, cohorts and guidelines we read, and at 13% in a four-year drug trial; the share moves with the definition, from 26% to 41% in one registry [20] [21] [16] [38].
That blood-pressure pills for white-coat hypertension prevent heart attacks and strokes: Preliminary; the European guidelines say no outcome trial has been done for it, and we found none designed for it [16] [15]. The evidence in its favour is indirect, from people over 80: about half of those monitored met the criteria in a trial that cut deaths and strokes, and across that substudy the pills lowered 24-hour readings by 8/5, a figure the paper does not give for the white-coat half [22]. The only count of events we found leans the same way and is too small to judge: in the group of 167 inside a placebo-controlled trial, six cardiovascular events on placebo and two on the drugs [13]. Against it, in that same group the 24-hour readings did not fall significantly on the drugs, and in two more trials the pills lowered clinic readings but not 24-hour ones [13] [38] [39].
What is not rated here: white-coat hypertension in pregnancy and in children; how to take a reading at home, which has its own verdict; and the frame above, which is this desk’s reasoning from the evidence rather than a result the evidence delivered. It is marked as ours so that you can weigh it as ours.
This is journalism, not medical advice. A diagnosis of high blood pressure, and any medicine for it, belong with a clinician, and so does a reading that worries you, urgently if it comes with symptoms. How we read a study, and what each tier means, is set out here.
- How to Measure Blood Pressure at Home: A Cuff Two Sizes Too Small Added 19.5 Points. Skipping the Five-Minute Rest Added Less.
supported - Are Squats Bad for Your Knees? The Warning’s Best-Known Source Is a 1961 Study of 128 Weightlifters. Squatters’ Knees Have Mostly Tested Fine Since. Hours of Squatting at Work Have Not.
unsupported - How to Lose Visceral Fat: Exercise Shrank It in Trial After Trial, Often by More Than the Scale Showed. The Green Tea Evidence Comes Mostly From Its Makers.
established